Related Experiment Video
Updated: May 25, 2026
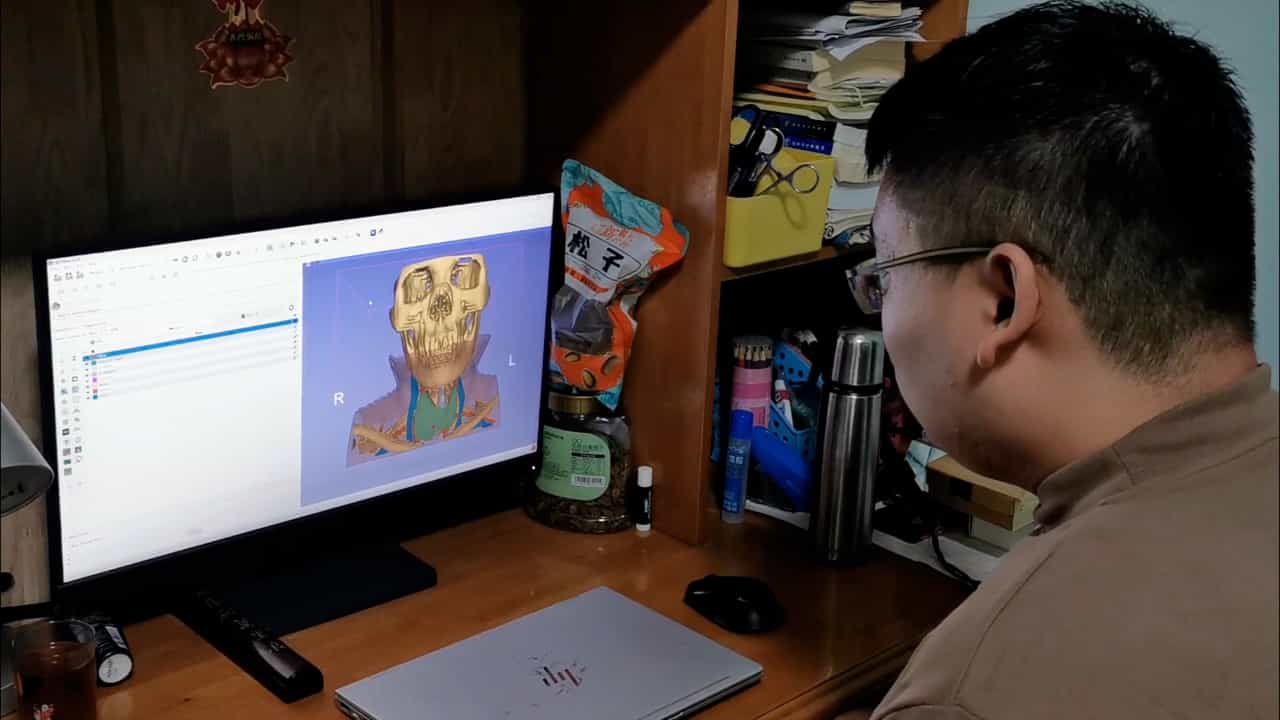

Mixed Reality Assisted Radical Endoscopic Thyroidectomy
Published on: January 31, 2025
Approach to the patient with postpartum thyroiditis
1George Washington University School of Medicine and Health Sciences, Washington, D.C. 20037, USA. msdasg@gwumc.edu

Postpartum thyroiditis (PPT) is the occurrence of de novo autoimmune thyroid disease, excluding Graves' disease, in the first year postpartum. The incidence of PPT is 5.4% in the general population, and it is increased in individuals with other autoimmune diseases such as type 1 diabetes mellitus. The classic presentation of PPT of hyperthyroidism followed by hypothyroidism is seen in 22% of cases. The majority of women with PPT experience an isolated hypothyroid phase (48%), with the remainder experiencing isolated thyrotoxicosis (30%). Up to 50% of women who are thyroid antibody positive (thyroid peroxidase antibody and/or thyroglobulin antibody) in the first trimester will develop PPT. Symptoms are more common in the hypothyroid phase of PPT and include fatigue, dry skin, and impaired memory. Despite multiple studies exploring the relationship between PPT and postpartum depression, or postpartum depression in thyroid antibody-positive euthyroid women, the data are conflicting, and no firm conclusions can be reached. Long-term follow-up of women who had an episode of PPT reveals a 20-40% incidence of permanent primary hypothyroidism. In a single study, selenium administration significantly decreased the incidence of PPT, but replication of the findings is needed before the recommendation can be made that all pregnant thyroid peroxidase antibody-positive women receive selenium. The indication for treating the hyperthyroid phase of PPT is control of symptoms, whereas treatment of the hypothyroid phase of PPT is indicated for symptomatic relief as well as in women who are either breastfeeding or attempting to conceive.
Postpartum thyroiditis (PPT) is the occurrence of de novo autoimmune thyroid disease, excluding Graves' disease, in the first year postpartum. The incidence of PPT is 5.4% in the general population, and it is increased in individuals with other autoimmune diseases such as type 1 diabetes mellitus. The classic presentation of PPT of hyperthyroidism followed by hypothyroidism is seen in 22% of cases. The majority of women with PPT experience an isolated hypothyroid phase (48%), with the remainder experiencing isolated thyrotoxicosis (30%). Up to 50% of women who are thyroid antibody positive (thyroid peroxidase antibody and/or thyroglobulin antibody) in the first trimester will develop PPT. Symptoms are more common in the hypothyroid phase of PPT and include fatigue, dry skin, and impaired memory. Despite multiple studies exploring the relationship between PPT and postpartum depression, or postpartum depression in thyroid antibody-positive euthyroid women, the data are conflicting, and no firm conclusions can be reached. Long-term follow-up of women who had an episode of PPT reveals a 20-40% incidence of permanent primary hypothyroidism. In a single study, selenium administration significantly decreased the incidence of PPT, but replication of the findings is needed before the recommendation can be made that all pregnant thyroid peroxidase antibody-positive women receive selenium. The indication for treating the hyperthyroid phase of PPT is control of symptoms, whereas treatment of the hypothyroid phase of PPT is indicated for symptomatic relief as well as in women who are either breastfeeding or attempting to conceive.
Related Concept Videos
 01:25
Hyperthyroidism I: Introduction
 01:28
Graves' Disease I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:27
Hyperthyroidism II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...