Related Experiment Video
Updated: May 25, 2026
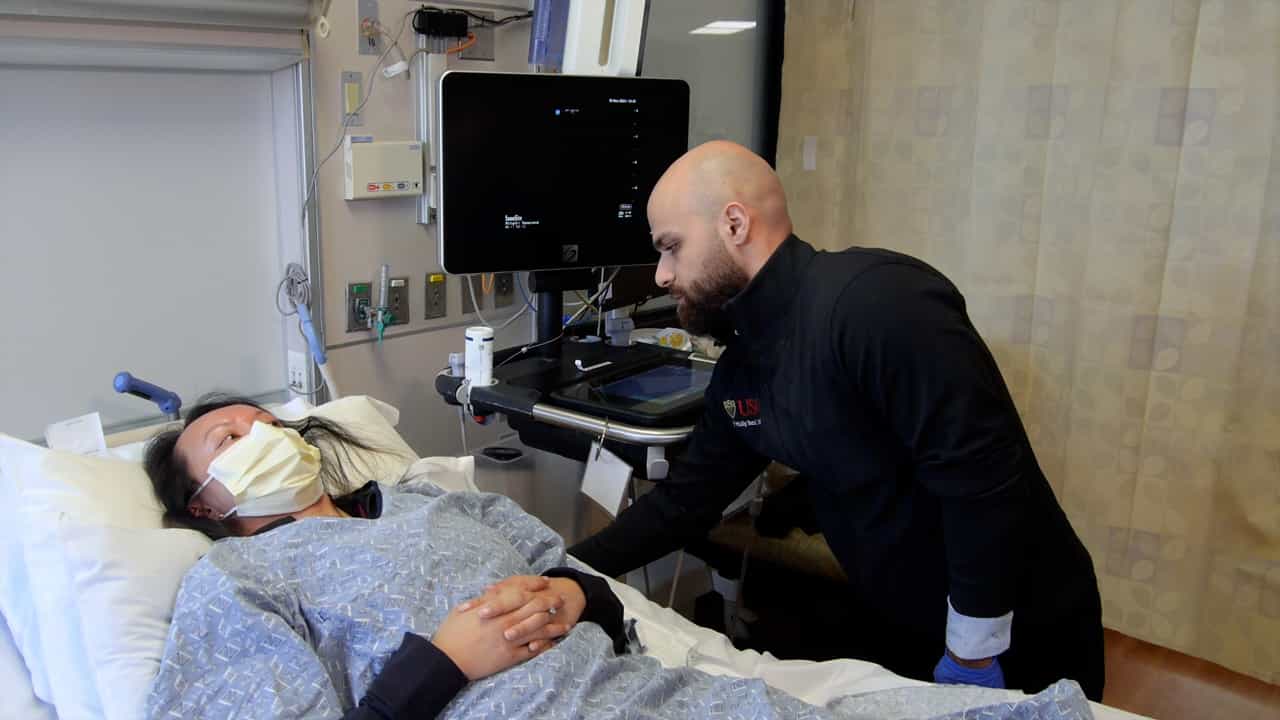

Point of Care Transcranial Color-Coded Duplex Ultrasound of the Middle Cerebral Artery
Published on: August 9, 2024
Effect of increased ICP and decreased CPP on DND and outcome in ASAH
1Department of Neurosurgery, Rangsit University, Bangkok, Thailand. patarapol@hotmail.com

Insights
Early clipping for aneurysmal subarachnoid hemorrhage (ASAH) can lead to increased intracranial pressure (ICP) and decreased cerebral perfusion pressure (CPP), potentially worsening neurological outcomes. While ICP elevation appears more detrimental, the study found no statistically significant relationships between these factors and patient outcomes.
Area of Science:
- Neurosurgery
- Neurology
- Critical Care Medicine
Background:
- Early clipping in aneurysmal subarachnoid hemorrhage (ASAH) can precipitate postoperative increases in intracranial pressure (ICP) and decreases in cerebral perfusion pressure (CPP).
- These hemodynamic changes may contribute to the development of delayed neurological deficit (DND), irreversible neurological deficit (IRND), and poor outcomes.
Purpose of the Study:
- To investigate the relationship between postoperative ICP and CPP and neurological outcomes in patients undergoing early clipping for ASAH.
- To evaluate the impact of ICP and CPP on DND, IRND, and poor outcomes.
Main Methods:
- A retrospective analysis of 30 patients with early clipping for ASAH.
- Inclusion of postoperative ICP monitoring, flow velocity measurement, triple H-nimodipine therapy, and an ICP-CPP-oriented strategy.
- Statistical analysis using the Chi-squared test to assess relationships between ICP, CPP, and neurological deficits.
Main Results:
- Mean ICP was 34.2 mmHg and mean CPP was 71.3 mmHg.
- Higher ICP levels (≥20, 30, 40 mmHg) correlated with increased incidence of DND (58.3%, 58.8%, 70%) and poor outcomes (37.5%, 41.1%, 40%).
- Lower CPP levels (≤80, 70, 60 mmHg) also correlated with increased DND (64.7%, 63.3%, 80%) and poor outcomes (41.1%, 27.2%, 40%).
- Statistical analysis did not reveal significant relationships between ICP, CPP, and neurological outcomes.
Conclusions:
- Postoperative increased ICP is common after early clipping, particularly in poor-grade ASAH patients.
- Decreased CPP was less frequent, potentially due to aggressive management strategies.
- Elevated ICP appears more detrimental than decreased CPP, acting as a secondary insult that may negatively impact neurological function.
Background:
When clipping is done early in aneurysmal SAH (ASAH), postoperative increased ICP and decreased CPP may present and influence development of delayed neurological deficit (DND), irreversible neurological deficit (IRND) and poor outcome.
Methods:
A retrospective study was performed in 30 early clipping ASAH with postoperative ICP monitoring, flow velocity measurement, triple H-nimodipine therapy, ICP-CPP orientated strategy and a 3-month follow-up period. Chi-squared test was performed on increased ICP, decreased CPP, combination of increased ICP+ decreased CPP and DND, IRND and poor outcome.
Results:
Two (7%), 19 (63%) and 9 (30%) patients were H&H 2, 3 and 4 respectively. Mean ICP and CPP were 34.2 and 71.3 mmHg. Mean ICP in H&H 2, 3 and 4 was 17.6, 34.3 and 50.2 mmHg respectively. 58.3%, 58.8% and 70% of patients with ICP ≥ 20, 30 and 40 mmHg had DND. 64.7%, 63.3% and 80% of patients with CPP ≤ 80, 70 and 60 mmHg had DND. 37.5%, 41.1% and 40% of patients with ICP ≥ 20, 30 and 40 mmHg had poor outcome. 41.1%, 27.2% and 40% of patients with CPP ≤ 80, 70 and 60 mmHg had poor outcome. Statistical analysis could not demonstrate a significant relationship among any of the parameters.
Conclusion:
Postoperative increased ICP is frequent in early clipping especially in poor-grade ASAH; decreased CPP is less frequent, possibly owing to triple H therapy and ICP-CPP orientated strategy. Increased ICP seems to be more detrimental than decreased CPP. Increased ICP and decreased CPP may affect deterioration of neurological function in terms of DND, IRND and poor outcome as secondary insult.
Related Concept Videos
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:21
Cytotoxic Edema: Pathophysiology
 01:22
Aneurysm IV: Nursing Management
 01:22
Cerebral Edema ll: Pathophysiology