Related Experiment Video
Updated: May 24, 2026

Comparative Proteomic Analysis of Whole Kidney, Medulla, and Cortical Tubules in Diabetic Pathogenesis of Kidney Injury in Mice
Published on: May 2, 2025
Pentoxifylline for diabetic kidney disease
Dan Shan1, Hong Mei Wu, Qi Yuan Yuan
1Department of Geriatrics, West China Hospital, Sichuan University, Chengdu, China.

Insights
Pentoxifylline may improve kidney function in diabetic kidney disease (DKD) by reducing albuminuria and proteinuria. However, evidence is limited due to study quality, necessitating further research for definitive recommendations.
Area of Science:
- Nephrology
- Pharmacology
- Diabetology
Background:
- Diabetic kidney disease (DKD) significantly increases morbidity and mortality, often due to cardiovascular complications.
- Inflammation plays a key role in DKD pathogenesis, with elevated inflammatory markers observed in affected individuals.
- Pentoxifylline, a phosphodiesterase inhibitor, exhibits anti-inflammatory and immunoregulatory properties, suggesting potential therapeutic benefits for DKD.
Purpose of the Study:
- To systematically evaluate the efficacy and safety of pentoxifylline in treating patients diagnosed with diabetic kidney disease (DKD).
- To assess the impact of pentoxifylline on renal function markers, proteinuria, and blood pressure in DKD patients.
Main Methods:
- Conducted a comprehensive literature search across multiple databases, including Cochrane Renal Group's specialized register, CENTRAL, MEDLINE, EMBASE, and Chinese biomedical databases.
- Included all randomized controlled trials (RCTs) and quasi-RCTs investigating pentoxifylline for DKD.
- Performed meta-analyses using random effects models to pool data on dichotomous and continuous outcomes, assessing risk ratios, mean differences, and standardized mean differences.
Main Results:
- In 17 studies with 991 participants, pentoxifylline significantly reduced serum creatinine and albuminuria compared to placebo.
- Pentoxifylline also significantly reduced albuminuria and proteinuria when compared to routine treatment alone.
- No significant differences in renal function or blood pressure were observed when compared to active comparators like captopril or clonidine/methyldopa; adverse events were mild.
Conclusions:
- Pentoxifylline demonstrates potential benefits in improving renal function and reducing proteinuria in DKD patients with a favorable safety profile.
- However, the current evidence is limited by the poor methodological quality, small sample sizes, and high risk of bias in the included studies.
- Further rigorously designed, large-scale, multicenter randomized controlled trials are essential to confirm the therapeutic efficacy of pentoxifylline for DKD.
Background:
Diabetic kidney disease (DKD) is associated with increased morbidity and mortality, mostly relating to cardiovascular complications. The relevance of inflammation in the pathogenesis of DKD has been investigated in recent years, and it has been shown that inflammatory markers are higher in people with DKD compared with the wider population. Pentoxifylline is a methylxanthine phosphodiesterase inhibitor with favourable anti-inflammatory effects and immunoregulatory properties. The anti-inflammatory effects conferred by pentoxifylline may be beneficial in the management of DKD.
Objectives:
To assess the benefits and harms of pentoxifylline for treating people with DKD.
Search Methods:
We searched the Cochrane Renal Group's specialised register (January 2012), CENTRAL (Issue 12, 2011), MEDLINE, EMBASE and four Chinese biomedical literature databases (CBM-disc, 1979 to July 2009), Chinese Science and Technique Journals Database (VIP, until July 2009), China National Knowledge Infrastructure (CNKI, until July 2009) and WanFang database (until July 2009).
Selection Criteria:
All randomised controlled trials (RCTs) and quasi-RCTs studying the benefits and harms of pentoxifylline for DKD.
Data Collection And Analysis:
Data were extracted independently by two authors. Meta-analyses were performed when more than one study provided data on a comparable outcome in sufficiently similar patients. Results of dichotomous outcomes were expressed as risk ratios (RR) with 95% confidence intervals (CI). Mean differences (MD) were calculated to assess the effects of treatment where outcomes were expressed on continuous scales, and standardised mean differences (SMD) calculated where different scales were used. Data was pooled using the random effects model. Adverse effects were assessed using descriptive techniques and where possible, risk differences (RD) with 95% CI.
Main Results:
We identified 17 studies that included a total of 991 participants with DKD which met our inclusion criteria. Overall, the methodological quality of included studies was low: 4/17 reported the method of randomisation, 13/17 did not; no study described the method of random allocation; 4/17 studies were considered to be at high risk of bias and 13/17 were considered to have unclear risk for incomplete outcome data reporting; 9/17 studies were at low risk bias and in 8/17 the risk of bias was unclear for selective outcome reporting.Compared with placebo, pentoxifylline significantly reduced serum creatinine (SCr) (MD -0.10 mg/dL, 95% CI -0.17 to -0.03), albuminuria (SMD -2.28, 95% CI -3.85 to -0.70) and overt proteinuria (MD -428.58 µg/min, 95% CI -661.65 to -195.50), but there was no difference in creatinine clearance (CrCl) (MD -5.18 mL/min, 95% CI -15.55 to 5.19). When compared with routine treatment alone, pentoxifylline did not significantly reduce SCr (MD 0.00 mg/dL, 95% CI -0.06 to 0.07) or blood pressure (systolic (SBP): MD -0.28 mm Hg, 95% CI -2.20 to 1.63; diastolic (DBP): MD -0.15 mm Hg, 95% CI -1.44 to 1.14), but did significantly reduce albuminuria (SMD 0.62, 95% CI 0.18 to 1.07) and proteinuria (MD 0.46 g/24 h, 95% CI 0.17 to 0.74). There was no significant difference in SCr (MD 0.00 mg/dL, 95% CI -0.08 to 0.07), albuminuria (MD -8.79 µg/min, 95% CI -27.18 to 9.59), proteinuria (MD -0.01 g/24 h, 95% CI -0.03 to 0.01) or blood pressure (SBP: MD 1.46 mm Hg, 95% CI -0.57 to 3.50; DBP: MD 1.37 mm Hg, 95% CI -0.23 to 2.98) between pentoxifylline and the active comparator (captopril or clonidine/methyldopa) for patients with type 1 and type 2 DKD. CrCl was significantly increased when pentoxifylline was compared to clonidine/methyldopa (MD 10.90 mL/min, 95% CI -1.40 to 20.40) but not with captopril (MD 3.26 mL/min, 95% CI -1.05 to 7.59). No data were available on the incidence of end-stage kidney disease (ESKD), time to ESKD, quality of life, or all-cause mortality. The adverse events of pentoxifylline were mild; no serious adverse events were reported in any of the included studies.
Authors' Conclusions:
From the available evidence, pentoxifylline seems to offer some beneficial effects in renal function improvement and reduction in albuminuria and proteinuria, with no obvious serious adverse effects for patients with DKD. However, most studies were poorly reported, small, and methodologically flawed. Evidence to support the use of pentoxifylline for DKD was insufficient to develop recommendations for its use in this patient population. Rigorously designed, randomised, multicentre, large scale studies of pentoxifylline for DKD are needed to further assess its therapeutic effects.
Related Concept Videos
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:28
Renal Drug Excretion: Tubular Secretion
 01:28
Diabetic Nephropathy
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:15
Renal Drug Excretion: Overview
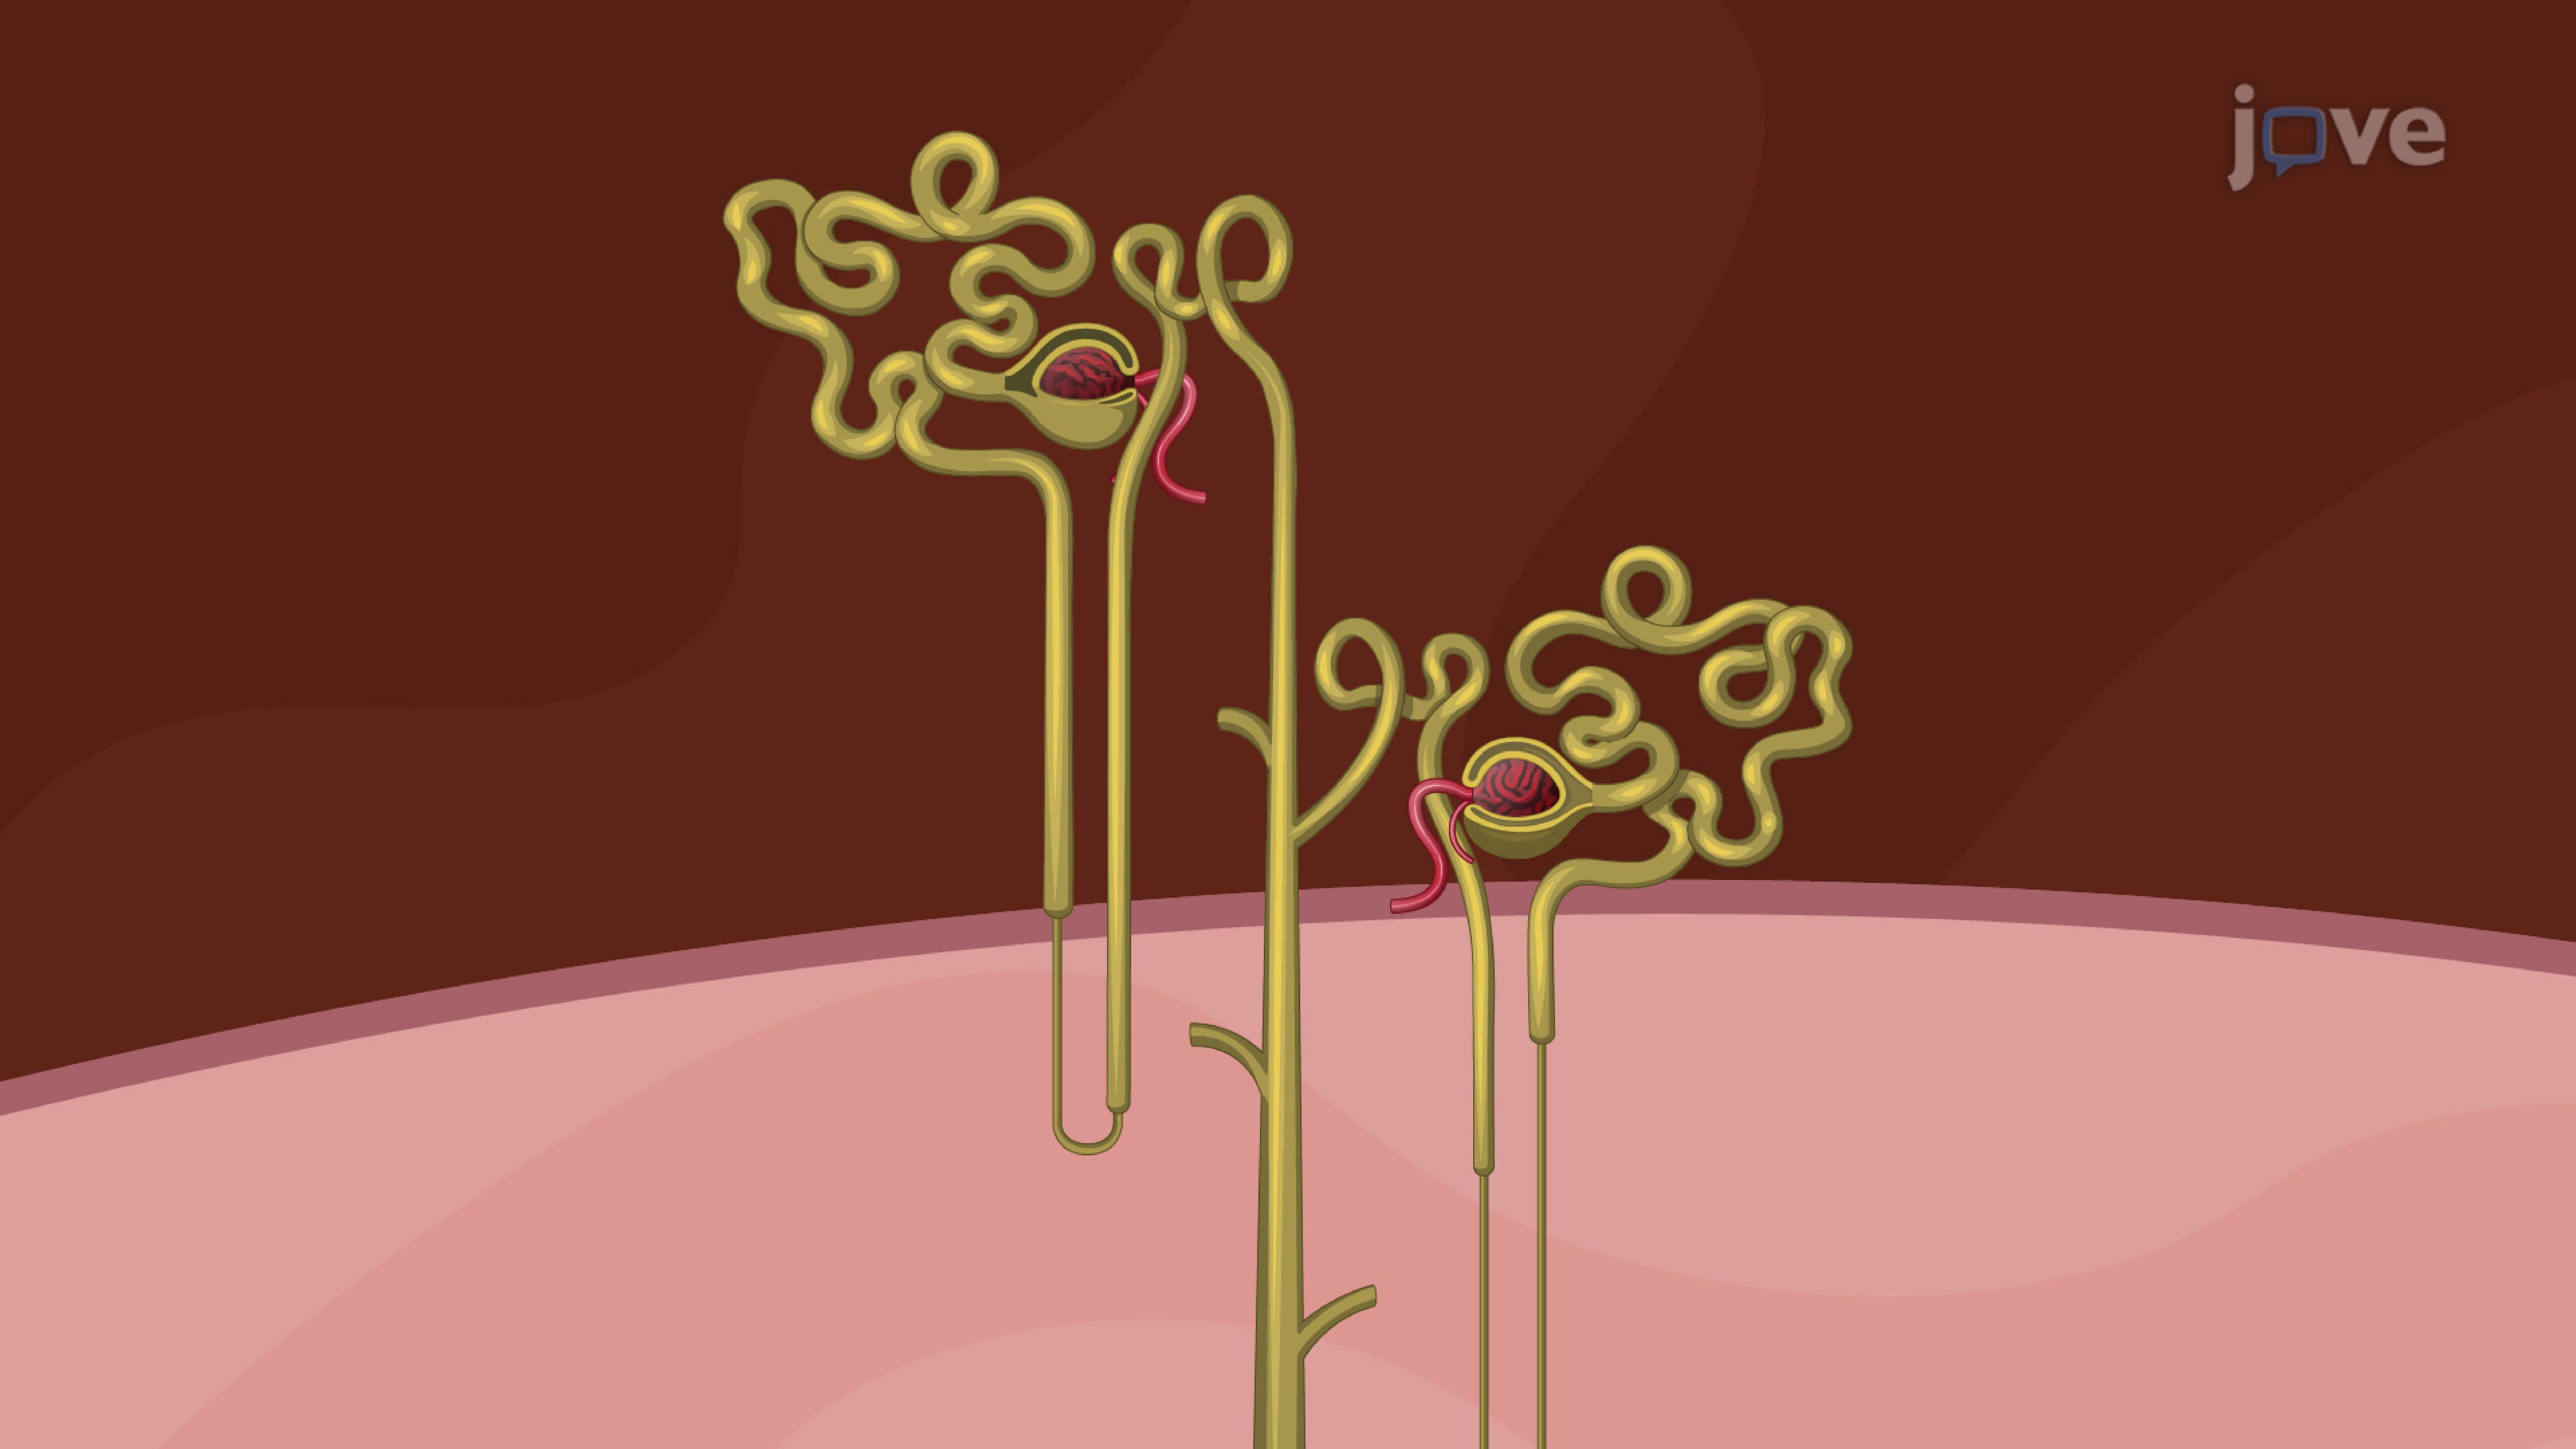
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules out...