Intraoperative incidence of hallux valgus interphalangeus following basilar first metatarsal osteotomy and distal soft tissue realignment
Related Experiment Video
Updated: May 24, 2026
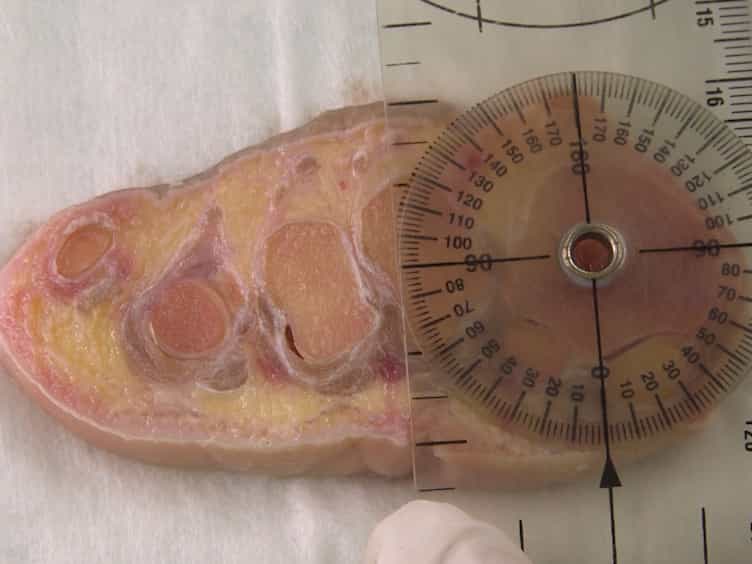
An Anatomical Study of Nerves at Risk During Minimally Invasive Hallux Valgus Surgery
Published on: February 17, 2018
Jae-Yong Park1, Hong-Geun Jung, Tae-Hoon Kim
1Department of Orthopaedic Surgery, Konkuk University School of Medicine, 4-12 Hwayang-dong, Gwangjin-gu, Seoul, Korea 143-729.

Background:
The premise of this study was that after the correction of hallux-metatarsophalangeal pronation, the intraoperative interphalangeal angle (HIA) increases significantly, and that an additional Akin osteotomy (AO) is often needed. Therefore, the purpose of this study was to evaluate whether HIAs in hallux valgus (HV) feet were underestimated, and to assess the need for AO during HV correction.
Method:
This study was conducted on 54 feet with moderate to severe HV treated from June 2007 to December 2008. HIAs and medial sesamoid subluxations (MSS) were measured initially and intraoperatively after a distal soft tissue procedure (DSTP) and proximal chevron metatarsal osteotomy (PCMO). An intraoperative technique was used to evaluate the incongruency of the metatarsophalangeal joint (MTPJ) to determine the need for additional Akin osteotomy.
Results:
After performing DSTP and PCMO, HIAs significantly increased from an average of 9 to 13.3 degrees and MSS reduced from average grade 2.5 to 0.5 (p < 0.05). Akin ostetomy was added in 44 (81%) feet. After an average followup of 13.2 months in Akin group, average VAS pain score decreased from 5.7 to 1.2 and average AOFAS score increased from 57.8 to 90.2 (p < 0.05). Final hallux MTPJ dorsiflexion in the Akin group was significantly larger than in the without-Akin group (p < 0.05).
Conclusion:
Average HIA significantly increased after DSTP and PCMO for moderate to severe HV necessitating additional Akin osteotomy, to achieve ideal HV correction and, to preserve MTPJ motion.