Related Experiment Video
Updated: May 24, 2026
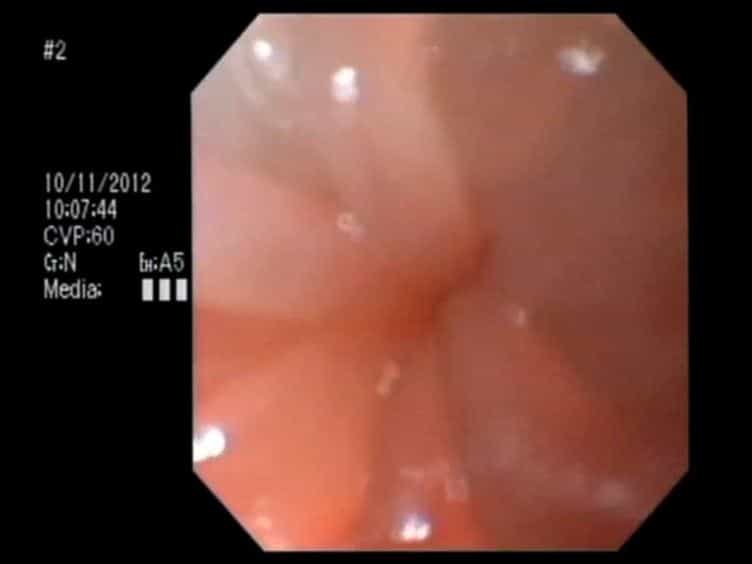

Flexible Colonoscopy in Mice to Evaluate the Severity of Colitis and Colorectal Tumors Using a Validated Endoscopic Scoring System
Published on: October 16, 2013
Fecal calprotectin is a surrogate marker for endoscopic lesions in inflammatory bowel disease
Geert D'Haens1, Marc Ferrante, Severine Vermeire
1Department of Gastroenterology, Academic Medical Centre, Amsterdam, The Netherlands. g.dhaens@amc.uva.nl

Background:
Fecal calprotectin is a marker of inflammation in inflammatory bowel disease (IBD). Since mucosal healing has become a goal of treatment in IBD we examined how reliably calprotectin levels reflect mucosal disease activity.
Methods:
In all, 126 IBD patients and 32 irritable bowel syndrome (IBS) patients needing colonoscopy delivered a sample of feces prior to the start of bowel cleansing. Besides collection of symptom scores and blood tests, experienced endoscopists recorded the Simple Endoscopic Score for Crohn's Disease (SES-CD) and the Crohn's Disease Endoscopic Index of Severity (CDEIS) in Crohn's disease (CD) patients and the Mayo endoscopic score in ulcerative colitis (UC) patients. Stool samples were shipped for central calprotectin PhiCal Assay (enzyme-linked immunosorbent assay [ELISA]). Correlation analysis was done with Pearson statistics.
Results:
The median (interquartile range [IQR]) fecal calprotectin levels were 175 (44-938) μg/g in CD, 465 (61-1128) μg/g in UC, and 54 (16-139) μg/g in IBS. Correlations were significant with endoscopic disease scores in both CD and in UC. Using ROC statistics, a cutoff value of 250 μg/g indicated the presence of large ulcers with a sensitivity of 60.4% and a specificity of 79.5% (positive predictive value [PPV] 78.4%, negative predictive value [NPV] 62.0%) in CD. Levels ≤ 250 μg/g predicted endoscopic remission (CDEIS ≤ 3) with 94.1% sensitivity and 62.2% specificity (PPV 48.5%, NPV 96.6%). In UC, a fecal calprotectin >250 μg/g gave a sensitivity of 71.0% and a specificity of 100.0% (PPV 100.0%, NPV 47.1%) for active mucosal disease activity (Mayo >0). Calprotectin levels significantly correlated with symptom scores in UC (r = 0.561, P < 0.001), but not in CD.
Conclusions:
Fecal calprotectin levels correlate significantly with endoscopic disease activity in IBD. The test appears useful in clinical practice for assessment of endoscopic activity and remission.
Related Concept Videos
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:20
Inflammatory Bowel Disease II: Ulcerative Colitis
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by transmural...
 01:30
Serum Laboratory Studies, Stool Test, Breath Test
 01:26
Inflammatory Bowel Disease I: Introduction
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...