Related Experiment Video
Updated: May 24, 2026


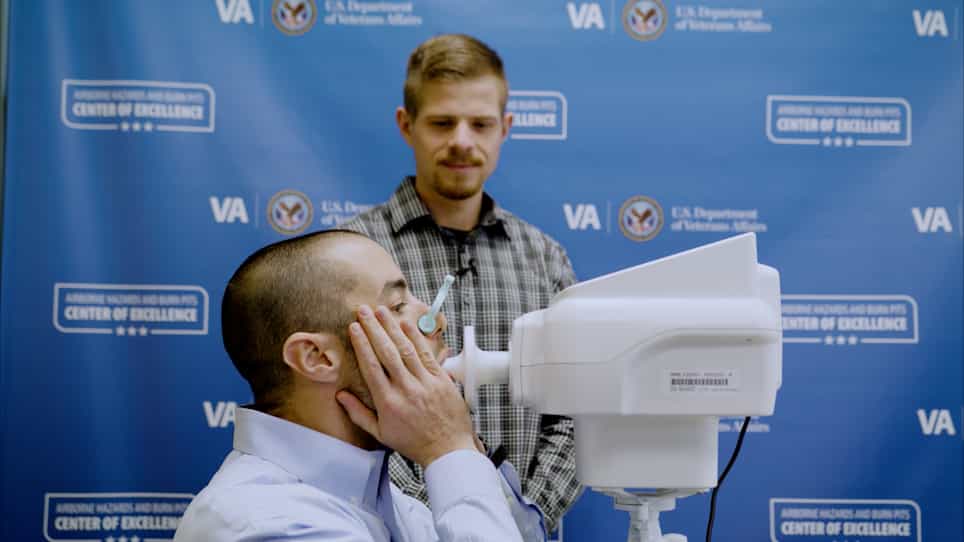
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Reflections on pediatric high-frequency oscillatory ventilation from a physiologic perspective
Martin C J Kneyber1, Marc van Heerde, Dick G Markhorst
1Department of Pediatrics, Division of Pediatric Intensive Care, Beatrix Children's Hospital, University Medical Center Groningen, Groningen, the Netherlands. m.c.j.kneyber@umcg.nl

Insights
High-frequency oscillatory ventilation (HFOV) offers lung protection with small tidal volumes. Optimizing HFOV use, including early application and specific settings, may improve patient outcomes in pediatric critical care.
Area of Science:
- Pediatric Critical Care Medicine
- Respiratory Physiology
- Mechanical Ventilation
Background:
- Low tidal volume mechanical ventilation is standard for preventing lung injury.
- High-frequency oscillatory ventilation (HFOV) uses minimal tidal volumes (1-2 mL/kg) to reduce atelectrauma.
- HFOV use in pediatric critical care is inconsistent (3-30%), possibly due to unproven outcomes or suboptimal application.
Purpose of the Study:
- To investigate the optimal application and settings of HFOV in pediatric critical care.
- To evaluate the impact of early HFOV initiation versus rescue therapy on patient survival.
- To explore refined HFOV settings for improved gas exchange and lung protection.
Main Methods:
- Review of existing literature and preliminary human data on HFOV.
- Analysis of a small randomized study comparing early vs. rescue HFOV.
- Physiological considerations for optimizing oscillator settings and lung volume recruitment.
Main Results:
- Early HFOV initiation, compared to rescue use, was linked to improved survival in one study.
- Experimental and preliminary human data suggest high-frequency, high-power settings may optimize gas exchange with minimal tidal volumes.
- An open-lung strategy using recruitment maneuvers and oscillation on the deflation limb of the P-V curve is proposed.
Conclusions:
- Optimal HFOV application, including timing and settings, requires further investigation.
- Refining HFOV strategies, such as early use and specific settings, may enhance patient outcomes.
- Future research should validate novel HFOV approaches for pediatric respiratory failure.
Abstract:
Mechanical ventilation using low tidal volumes has become universally accepted to prevent ventilator-induced lung injury. High-frequency oscillatory ventilation (HFOV) allows pulmonary gas exchange using very small tidal volume (1-2 mL/kg) with concomitant decreased risk of atelectrauma. However, its use in pediatric critical care varies between only 3% and 30% of all ventilated children. This might be explained by the fact that the beneficial effect of HFOV on patient outcome has not been ascertained. Alternatively, in contrast with present recommendations, one can ask if HFOV has been employed in its most optimal fashion related especially to the indications for and timing of HFOV, as well as to using the best oscillator settings. The first was addressed in one small randomized study showing that early use of HFOV, instead of rescue use, was associated with improved survival. From a physiologic perspective, the oscillator settings could be refined. Lung volume is the main determinant of oxygenation in diffuse alveolar disease, suggesting using an open-lung strategy by recruitment maneuvers, although this is in practice not custom. Using such an approach, the patient can be oscillated on the deflation limb of the pressure-volume (P-V) curve, allowing less pressure required to maintain a certain amount of lung volume. Gas exchange is determined by the frequency and the oscillatory power setting, controlling the magnitude of the membrane displacement. Experimental work as well as preliminary human data have shown that it is possible to achieve the smallest tidal volume with concomitant adequate gas exchange when oscillating at high frequency and high fixed power setting. Future studies are needed to validate these novel approaches and to evaluate their effect on patient outcome.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:29
Mechanical Ventilation I: Indication and Settings
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...