Related Experiment Video
Updated: May 24, 2026


Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
The effect of airway pressure and oscillation amplitude on ventilation in pre-term infants
Martijn Miedema1, Frans H de Jongh, Inez Frerichs
1Dept of Neonatology (H3-214), Emma Children's Hospital AMC, PO Box 22660, 1100 DD Amsterdam, The Netherlands. m.miedema@amc.uva.nl

Insights
In preterm infants with respiratory distress syndrome, high-frequency oscillatory ventilation (HFOV) shows that oscillation volume, not functional residual capacity (FRC), changes with pressure amplitude. This impacts CO2 levels during HFOV for neonates.
Area of Science:
- Neonatal Medicine
- Pediatric Critical Care
- Respiratory Physiology
Background:
- Respiratory distress syndrome (RDS) is common in preterm infants.
- High-frequency oscillatory ventilation (HFOV) is a key respiratory support strategy.
- Understanding HFOV mechanics is crucial for optimizing outcomes.
Purpose of the Study:
- To investigate the effects of lung recruitment and oscillation amplitude on regional oscillation volume and functional residual capacity (FRC).
- To determine the relationship between pressure amplitude, oscillation volume, and CO2 levels in preterm infants with RDS.
- To identify optimal ventilation pressures for maximal compliance and minimal CO2.
Main Methods:
- Studied 10 preterm infants with RDS undergoing HFOV.
- Utilized electrical impedance tomography (EIT) and transcutaneous monitoring.
- Recorded lung volume, oscillation volume, and CO2 levels during stepwise recruitment and pressure amplitude changes.
Main Results:
- Oscillation volume followed a parabolic pattern with increasing pressure, inversely related to CO2 levels.
- Pressures for maximal compliance, oscillation volume, and minimal CO2 were similar and correlated.
- Increased pressure amplitude raised oscillation volumes and lowered CO2, but FRC remained stable.
Conclusions:
- In preterm infants with RDS on HFOV, oscillation volume is linked to the pressure-volume envelope and amplitude.
- Changes in pressure amplitude influence CO2 elimination but not FRC.
- HFOV parameters require careful adjustment to optimize ventilation in neonates.
Abstract:
We determined the effect of lung recruitment and oscillation amplitude on regional oscillation volume and functional residual capacity (FRC) in high-frequency oscillatory ventilation (HFOV) used in pre-term infants with respiratory distress syndrome (RDS). Changes in lung volume, oscillation volume and carbon dioxide levels were recorded in 10 infants during a stepwise recruitment procedure, and an increase in pressure amplitude of 5 cmH(2)O was measured using electrical impedance tomography and transcutaneous monitoring. The pressures at maximal respiratory system compliance, maximal oscillation volume and minimal carbon dioxide levels were determined. Impedance data were analysed for the chest cross-section and predefined regions of interest. Despite the fixed pressure amplitude, the oscillation volume changed during the incremental pressure steps following a parabolic pattern, with an inverse relationship to the carbon dioxide pressures. The pressures corresponding with maximal compliance, maximal oscillation volume and minimal carbon dioxide were similar and highly correlated. Regional analysis showed similar findings. The increase in pressure amplitude resulted in increased oscillation volumes and decreased carbon dioxide levels, while FRC remained unchanged. In HFV pre-term infants with RDS, oscillation volumes are closely related to the position of ventilation in the pressure-volume envelope and the applied pressure amplitude. Changes in pressure amplitude do not seem to affect FRC.

Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
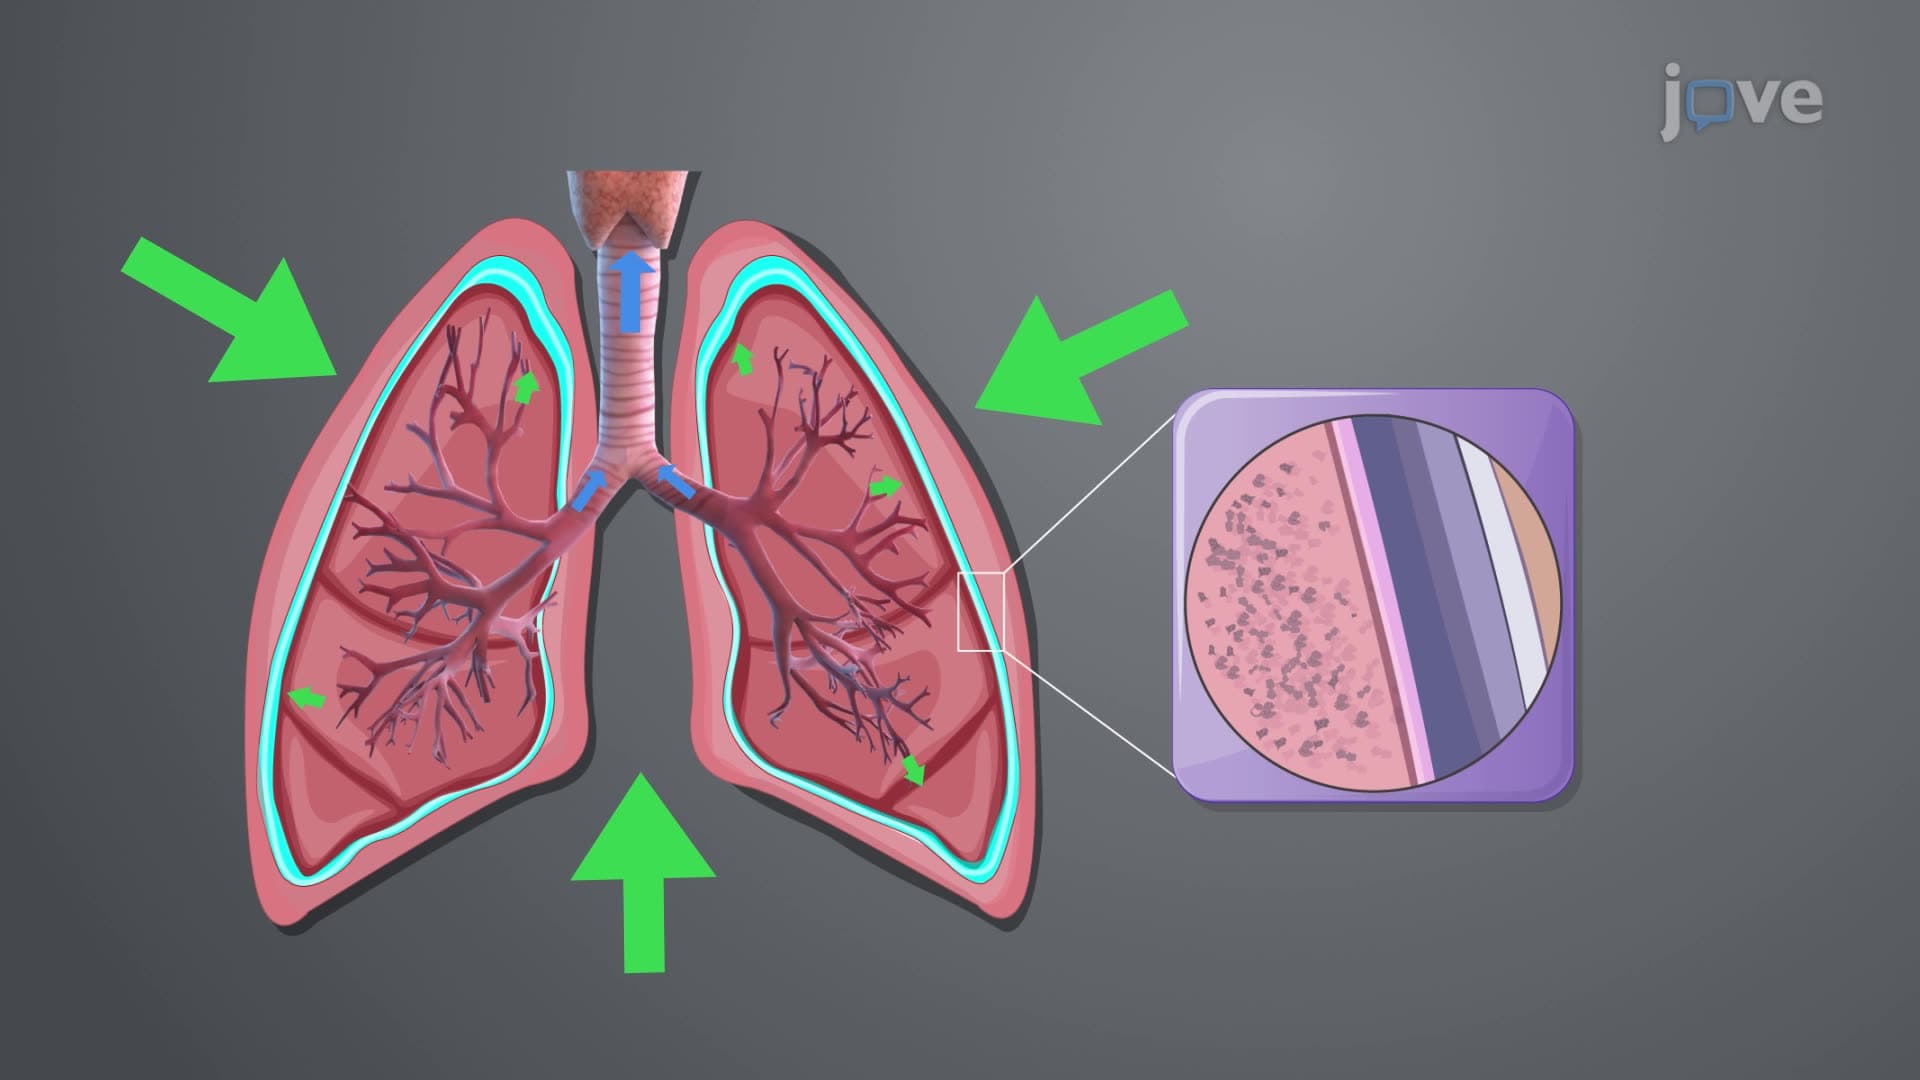
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: