Related Experiment Video
Updated: Aug 17, 2026

Programmed Electrical Stimulation in Mice
Published on: May 26, 2010
[Comparison between the unipolar and bipolar mode for estimation and detection of auricular and ventricular duration
G Rodrigo Trallero1, J Suárez Alzamora, J V Valle Montañés
1Servicios de Cardiología, Hospital Clínico Universitario, Zaragoza.

Unlabelled:
To add data on controversy between the advantages and inconveniences of using either unipolar or bipolar modes for permanent cardiac pacing, we have studied 15 patients. In all of them a CPI Delta-925 (DDD) pulse generator was implanted. Non invasive pacing threshold values in volts were measured at 0.05, 0.08 and 0.1 ms for each chamber programmed either to unipolar or bipolar mode, at 1, 2, 3, 4, 5, 6, 7, 8, 14, 21, 30, 60, 90, 120, 180 and 365 days after the implant. Sensing thresholds were measured at the same time. For any pulse width the mean pacing thresholds in atrium and ventricle increase uniformly, reaching its maximum values between the days 8 and 14 after the implant and decreases to a stable value between 90 and 120 days after the implant, without statistically significant differences for both: unipolar and bipolar modes. Pacing thresholds (V +/- SD) for 0.05 ms in the day 365th were in atrium: unipolar 2.85 +/- 0.79, bipolar 3.35 +/- 0.92 (p = 0.56) and ventricle: unipolar 3.92 +/- 1.01, bipolar 4.36 +/- 1.35 (p = 0.58). Sensing thresholds in atrium and ventricle decreases from the 1st day after the implant with the minimum mean value the day 8th, increasing eventually. No statistically significant differences were found between sensing unipolar/bipolar mode at each chamber. Sensing thresholds (mV +/- SD) in the 365th day were in atrium: unipolar 4.40 +/- 2.07, bipolar 4.10 +/- 2.10 (p = 0.82) and ventricle: unipolar 11.20 +/- 3.63, bipolar 10.10 +/- 5.13 (p = 0.71).
Conclusions:
for every single patient: 1) There are not statistically significant differences in the evolution of unipolar and bipolar pacing thresholds both in atrium and ventricle, regarding rate and time of increase, maximum value, rate of decrease and stable chronic values. 2) There are neither statistically significant differences regarding unipolar and bipolar sensing in atrium and ventricle respect to rate of decrease, time and value of the minimum and stable chronic values.


Related Concept Videos
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac muscle...
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:30
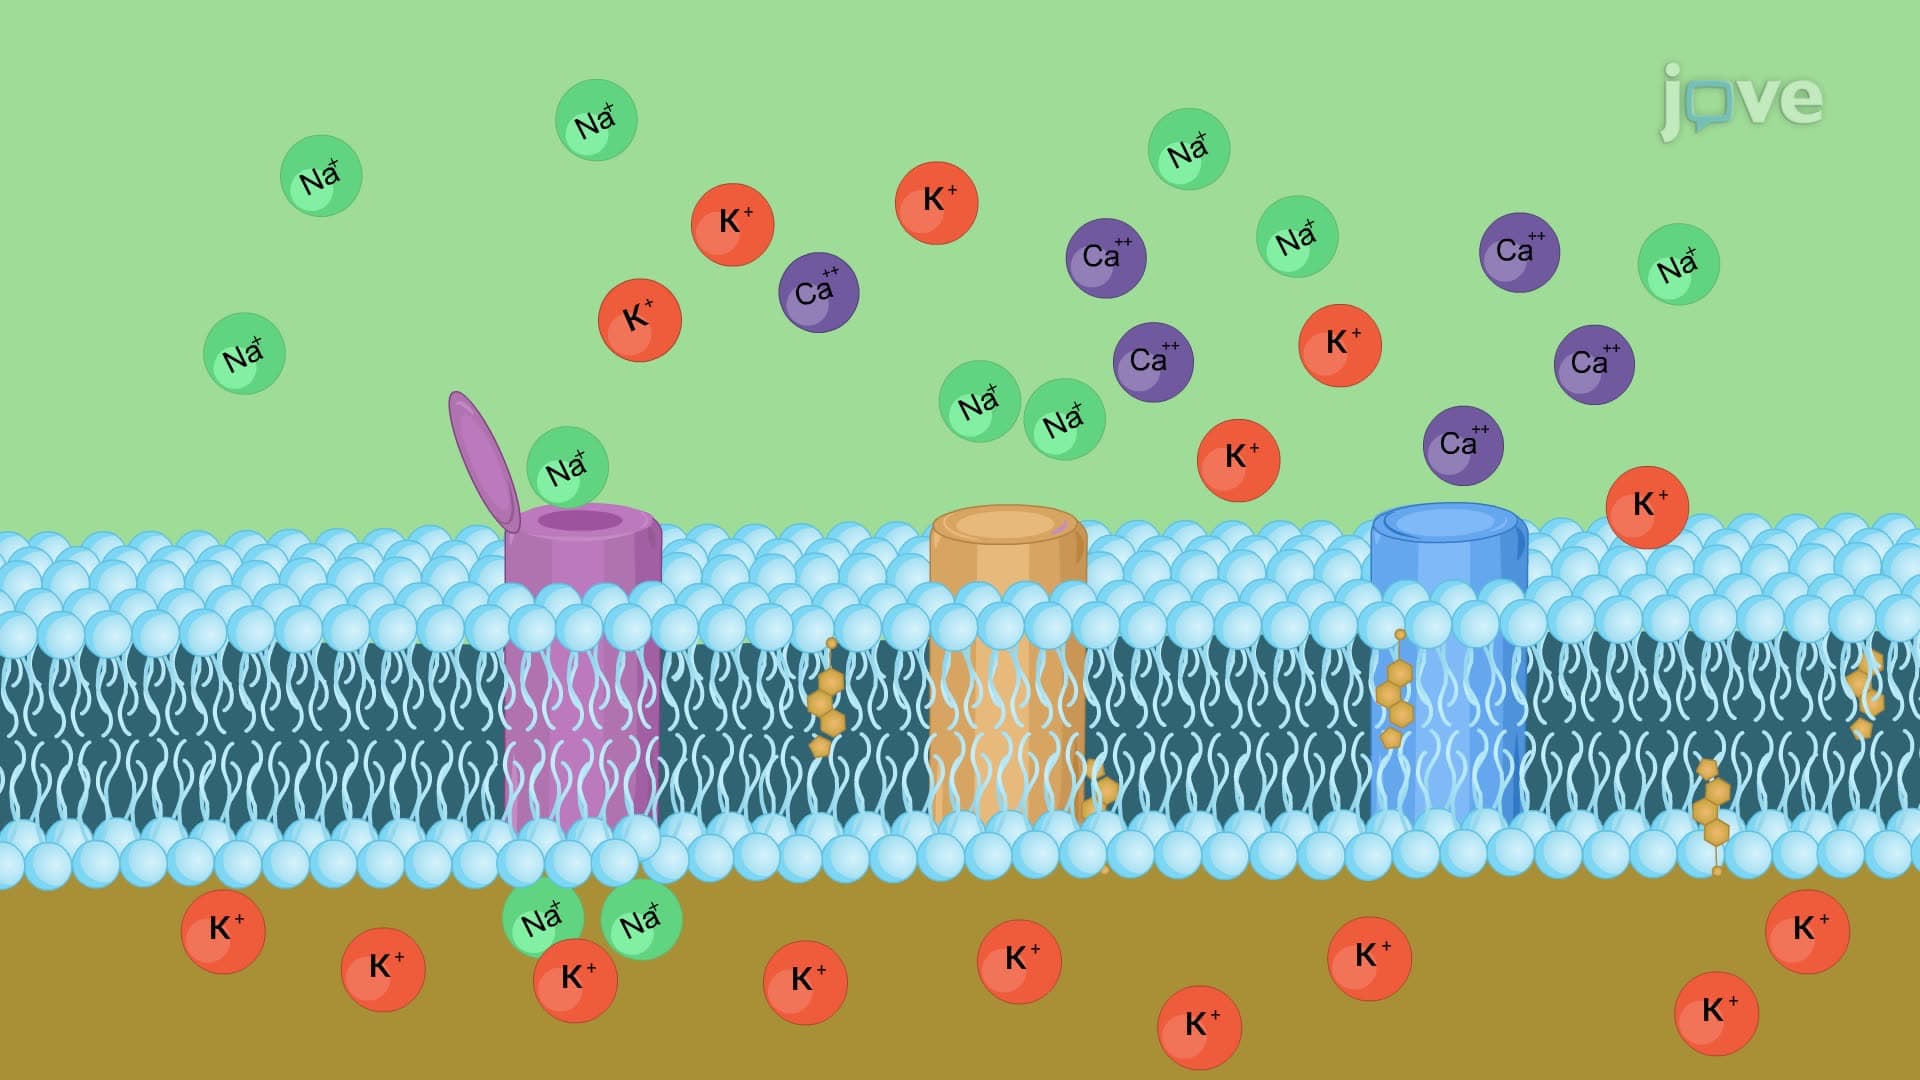
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:29
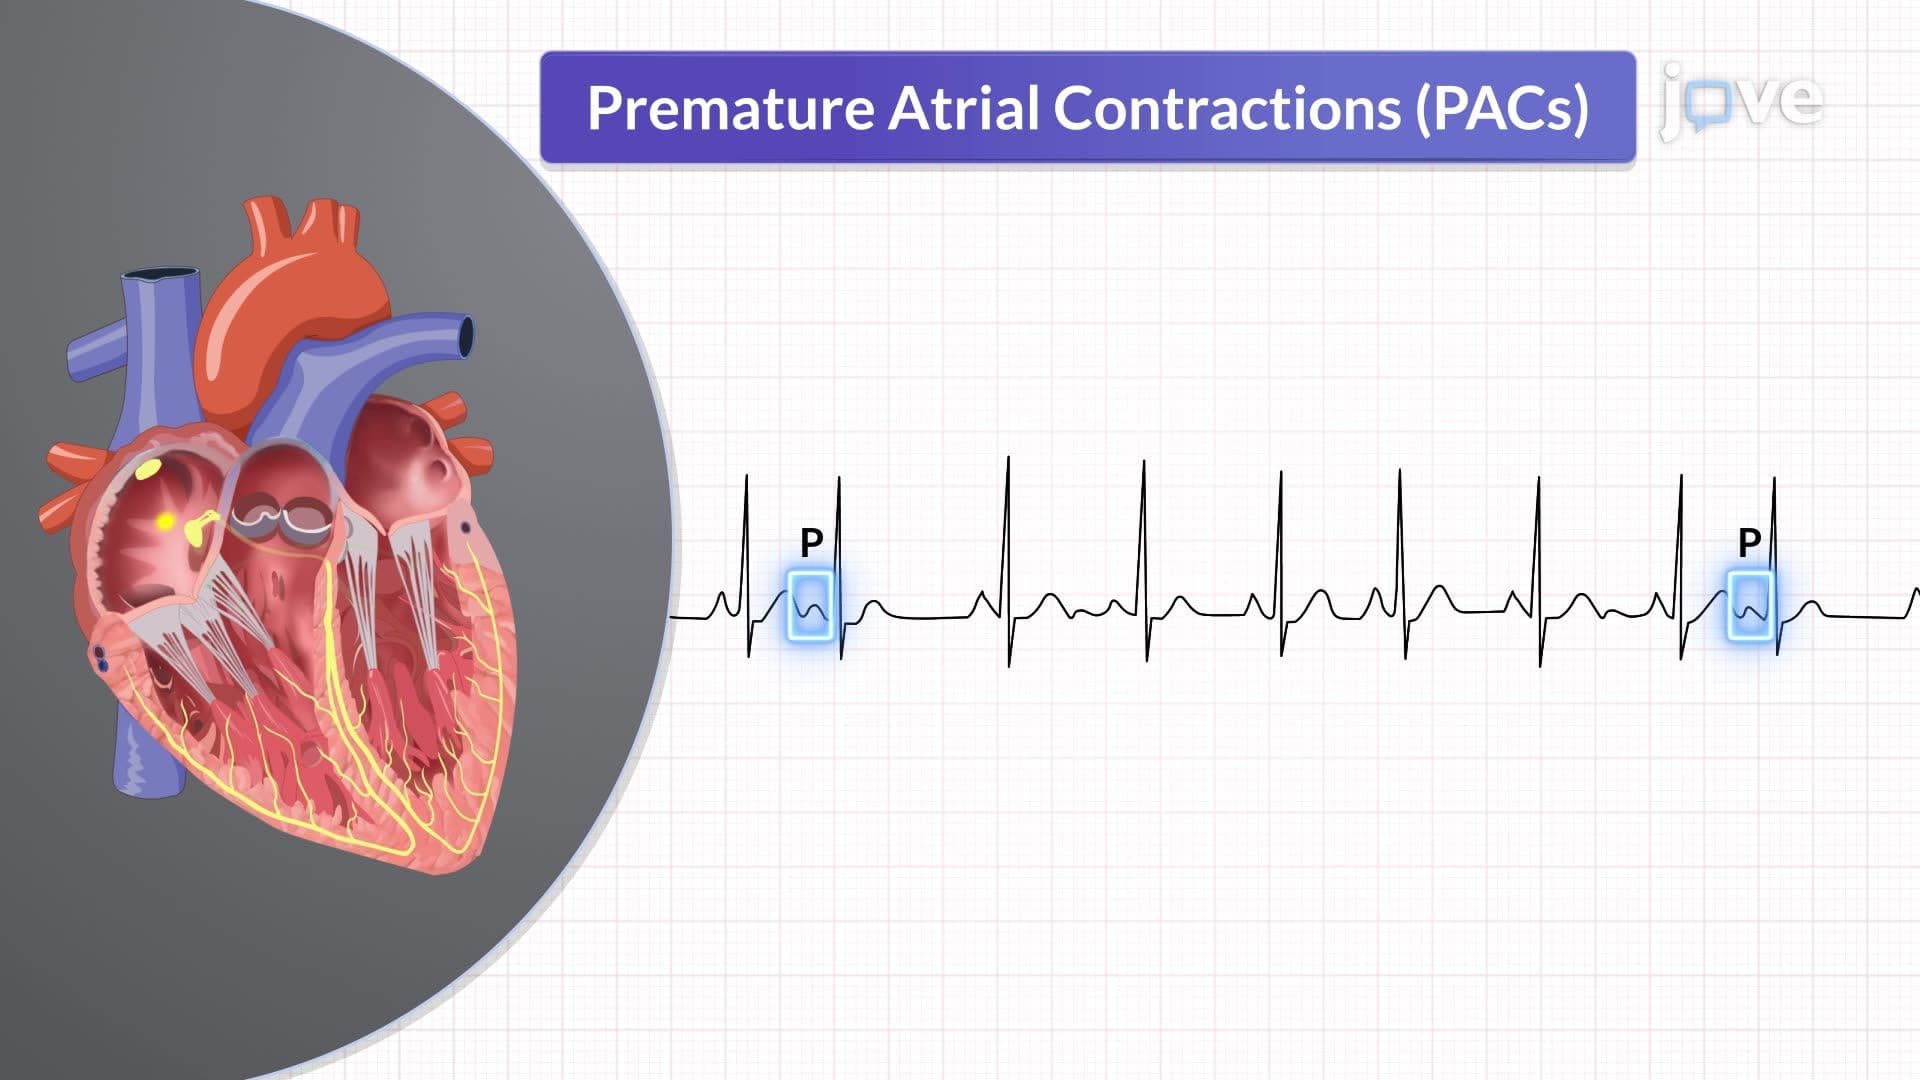
Dysrhythmias III: Characteristics of Dysrhythmias
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias