Related Experiment Video
Updated: May 24, 2026


Use of Ultra-high Field MRI in Small Rodent Models of Polycystic Kidney Disease for In Vivo Phenotyping and Drug Monitoring
Published on: June 23, 2015
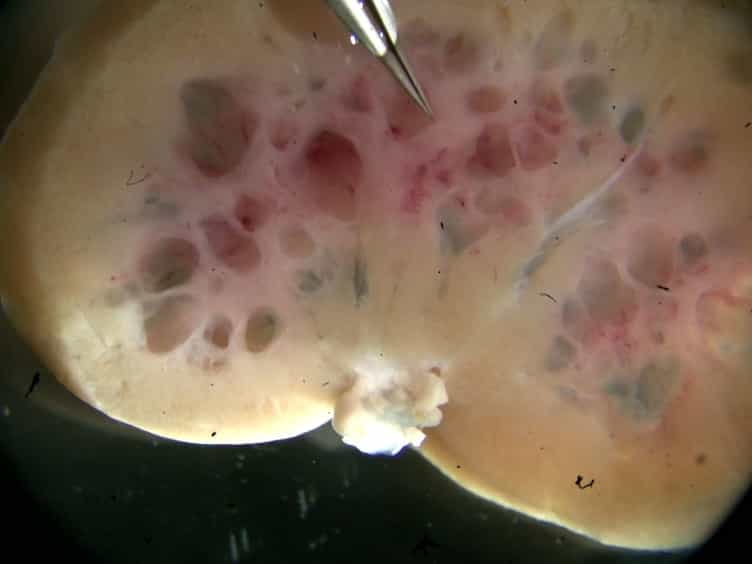
Disseminated kidney tuberculosis complicating autosomal dominant polycystic kidney disease: a case report
Hideki Takeshita1, Morimasa Amemiya, Koji Chiba
1Department of Urology, Saitama Red Cross Hospital, Saitama, Japan. take_uro@ybb.ne.jp

Abstract:
Mycobacterium tuberculosis infection in patients with autosomal dominant polycystic kidney disease (ADPKD) is rare, and its diagnosis and treatment are difficult because numerous cysts are exposed to infection and antibiotics do not easily penetrate infected cysts. Here, we report the case of a 43-year-old Japanese man with disseminated urogenital tuberculosis (TB) and ADPKD without human immunodeficiency virus (HIV) infection. Delayed diagnosis and ineffective anti-TB chemotherapy worsened his condition. Finally, he underwent bilateral nephrectomy but experienced postoperative complications. In conclusion, kidney TB should be recognized as a cause of renal infection in ADPKD, and surgical treatment should be instituted without delay. The importance of early diagnosis and treatment cannot be overemphasized to prevent kidney TB deterioration.
Insights
Tuberculosis (TB) in autosomal dominant polycystic kidney disease (ADPKD) patients is rare and challenging to treat due to cyst penetration issues. Early diagnosis and surgical intervention are crucial for better outcomes in kidney TB within ADPKD.
Area of Science:
- Nephrology
- Infectious Diseases
- Urology
Background:
- Autosomal dominant polycystic kidney disease (ADPKD) presents unique challenges for managing infections.
- Mycobacterium tuberculosis (TB) infections in ADPKD patients are uncommon and difficult to diagnose and treat.
- Antibiotic penetration into infected cysts in ADPKD is often limited, complicating treatment strategies.
Observation:
- A case report of a 43-year-old Japanese male with disseminated urogenital tuberculosis (TB) and ADPKD without HIV infection is presented.
- The patient experienced delayed diagnosis and ineffective anti-TB chemotherapy, leading to disease progression.
- The patient ultimately required bilateral nephrectomy, which resulted in postoperative complications.
Findings:
- Kidney tuberculosis (TB) should be considered a significant cause of renal infection in patients with ADPKD.
- Delayed diagnosis and suboptimal anti-TB chemotherapy exacerbated the patient's condition.
- Surgical intervention, such as bilateral nephrectomy, may be necessary but carries risks of complications.
Implications:
- Early recognition and diagnosis of kidney TB in ADPKD patients are critical.
- Prompt and appropriate treatment, including surgical options, is essential to prevent disease deterioration.
- This case highlights the need for increased awareness and tailored management approaches for TB in ADPKD patients.

Related Concept Videos
 01:25
Chronic Kidney Disease I: Introduction
 01:10
Nephrons
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:28
Diabetic Nephropathy