Related Experiment Video
Updated: May 24, 2026

Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Cyclophosphamide and 4-hydroxycyclophosphamide pharmacokinetics in patients with glomerulonephritis secondary to
Melanie S Joy1, Mary La, Jinzhao Wang
1Division of Nephrology and Hypertension, UNC Kidney Center, University of North Carolina School of Medicine, Chapel Hill, USA. melanie_joy@med.unc.edu

Aims:
Cyclophosphamide, the precursor to the active 4-hydroxycyclophosphamide, is used in active glomerulonephritis despite limited pharmacokinetics data. The pharmacokinetics of cyclophosphamide and 4-hydroxycyclophosphamide were evaluated. The influence of laboratory and pharmacogenomic covariates on pharmacokinetics was evaluated as a secondary aim.
Methods:
Glomerulonephritis patients (n = 23) participated in a pharmacokinetic evaluation. Blood was serially collected and assayed for cyclophosphamide and 4-hydroxycyclophosphamide by LC/MS methods. Kidney function, serum albumin and polymorphisms in drug metabolism or transport genes were evaluated. Analyses included non-compartmental pharmacokinetics and parametric and non-parametric statistics.
Results:
The mean area under the plasma concentration-time curve (AUC(0,∞)) data were 110,100 ± 42,900 ng ml(-1) h and 5388 ± 2841 ng ml(-1) h for cyclophosphamide and 4-hydroxycyclophosphamide, respectively. The mean metabolic ratio was 0.06 ± 0.04. A statistically significant relationship was found between increased serum albumin and increased half-life (0.584, P = 0.007, 95% CI 0.176, 0.820) and a borderline relationship with AUC(0,∞) (0.402, P = 0.079, 95% CI -0.064, 0.724) for 4-hydroxycyclophosphamide. Covariate relationships that trended toward significance for cyclophosphamide included decreased serum albumin and increased elimination rate constant (-0.427, P = 0.061, 95% CI 0.738, 0.034), increased urinary protein excretion and increased AUC(0,∞) (-0.392, P = 0.064, 95% CI -0.699 to 0.037), decreased C(max) (0.367, P = 0.085, 95% CI -0.067, 0.684) and decreased plasma clearance (-0.392, P = 0.064, 95% CI -0.699, 0.037). CYP2B6*9 variants vs. wildtype were found to have decreased elimination rate constant (P = 0.0005, 95% CI 0.033, 0.103), increased V(d) (P = 0.0271, 95% CI -57.5, -4.2) and decreased C(max) (P = 0.0176, 95% CI 0.696, 6179) for cyclophosphamide. ABCB1 C3435T variants had a borderline decrease in cyclophosphamide elimination rate constant (P = 0.0858; 95% CI -0.005, 0.102).
Conclusions:
Pharmacokinetics of cyclophosphamide and 4-hydroxycyclophosphamide in patients with lupus nephritis and small vessel vasculitis are similar. Clinical and pharmacogenetic covariates alter disposition of cyclophosphamide and 4-hydroxycyclophosphamide. Clinical findings of worsened glomerulonephritis lead to increased exposure to cyclophosphamide vs. the active 4-hydroxycyclophosphamide, which could have relevance in terms of clinical efficacy. The CYP2B6*9 and ABCB1 C3435T polymorphisms alter the pharmacokinetics of cyclophosphamide and 4-hydroxycyclophosphamide in glomerulonephritis.

Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:20
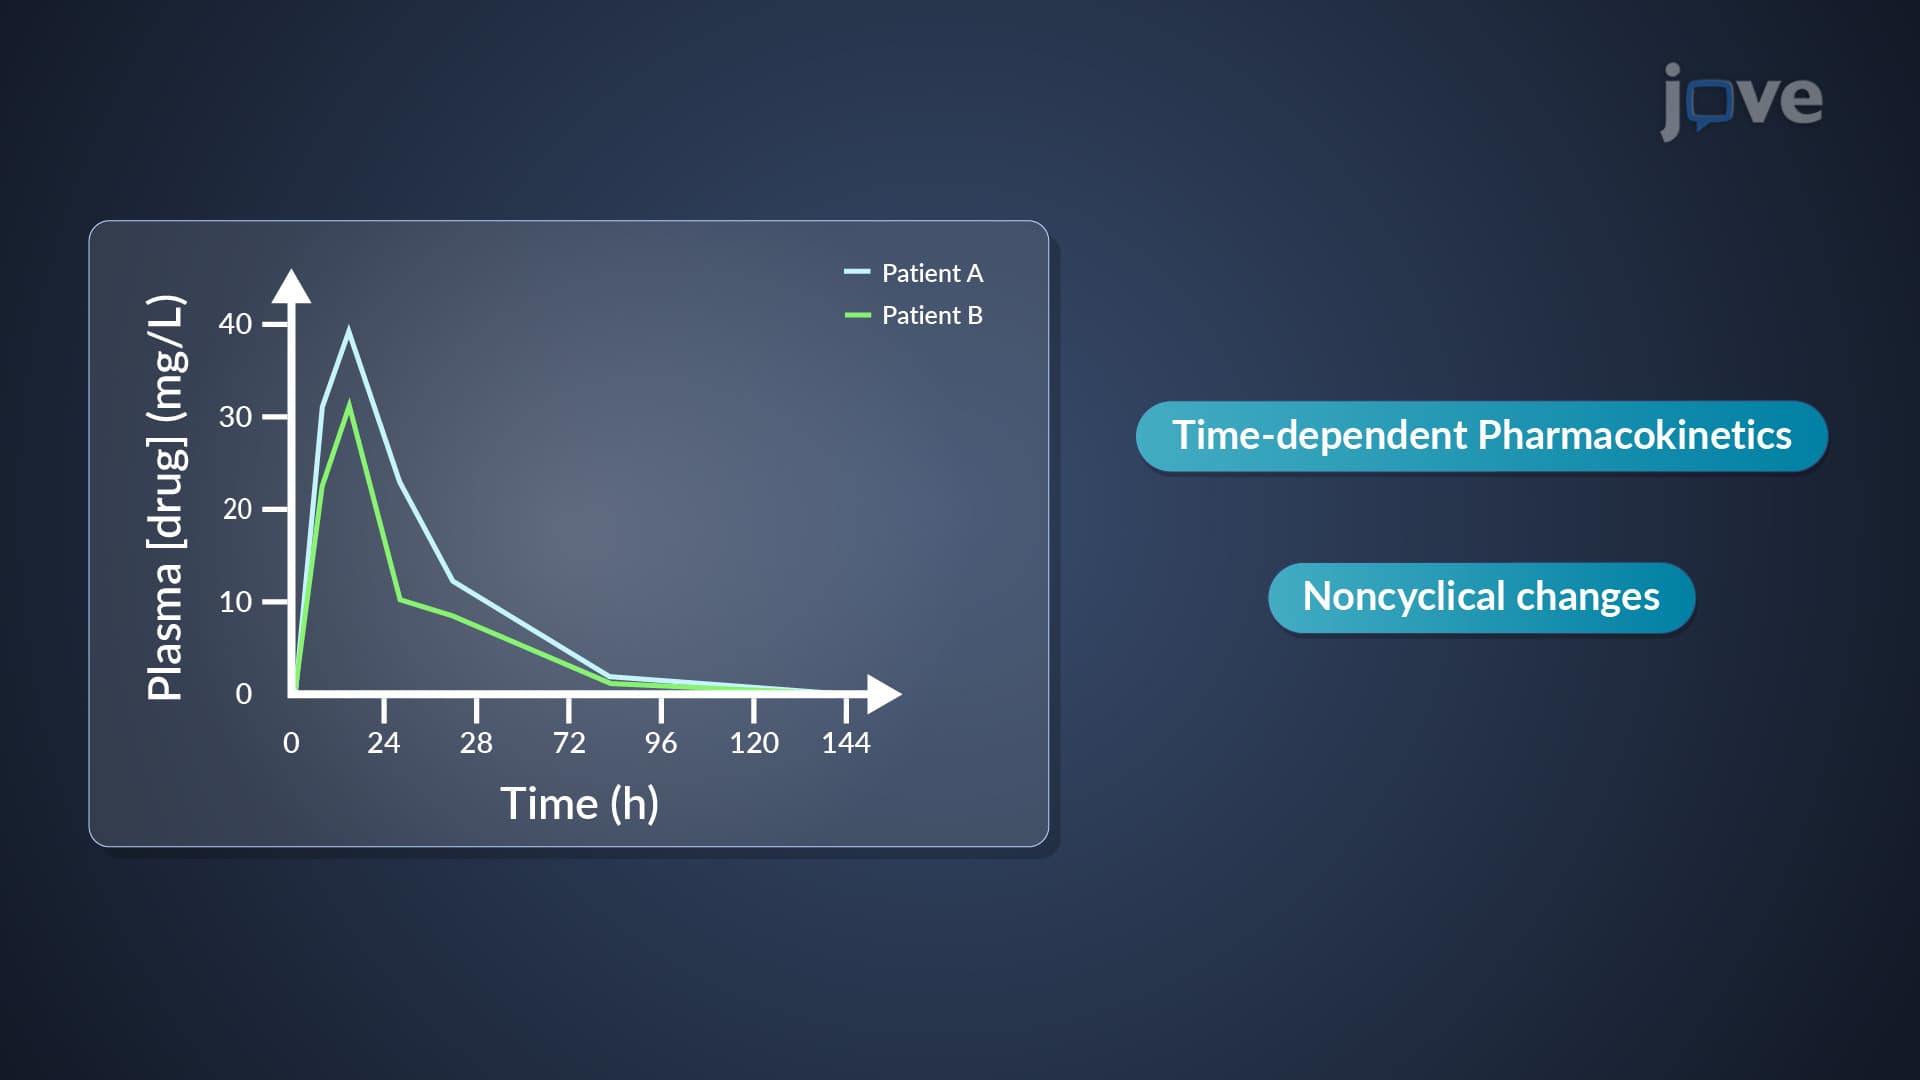
Chronopharmacokinetics: Time-Dependent Pharmacokinetics
Time-dependent pharmacokinetics refers to non-cyclical changes in drug rate processes over a period of time. It can lead to nonlinear pharmacokinetics, where the relationship between drug concentration and time is not proportional. Non-cyclical...
 01:09
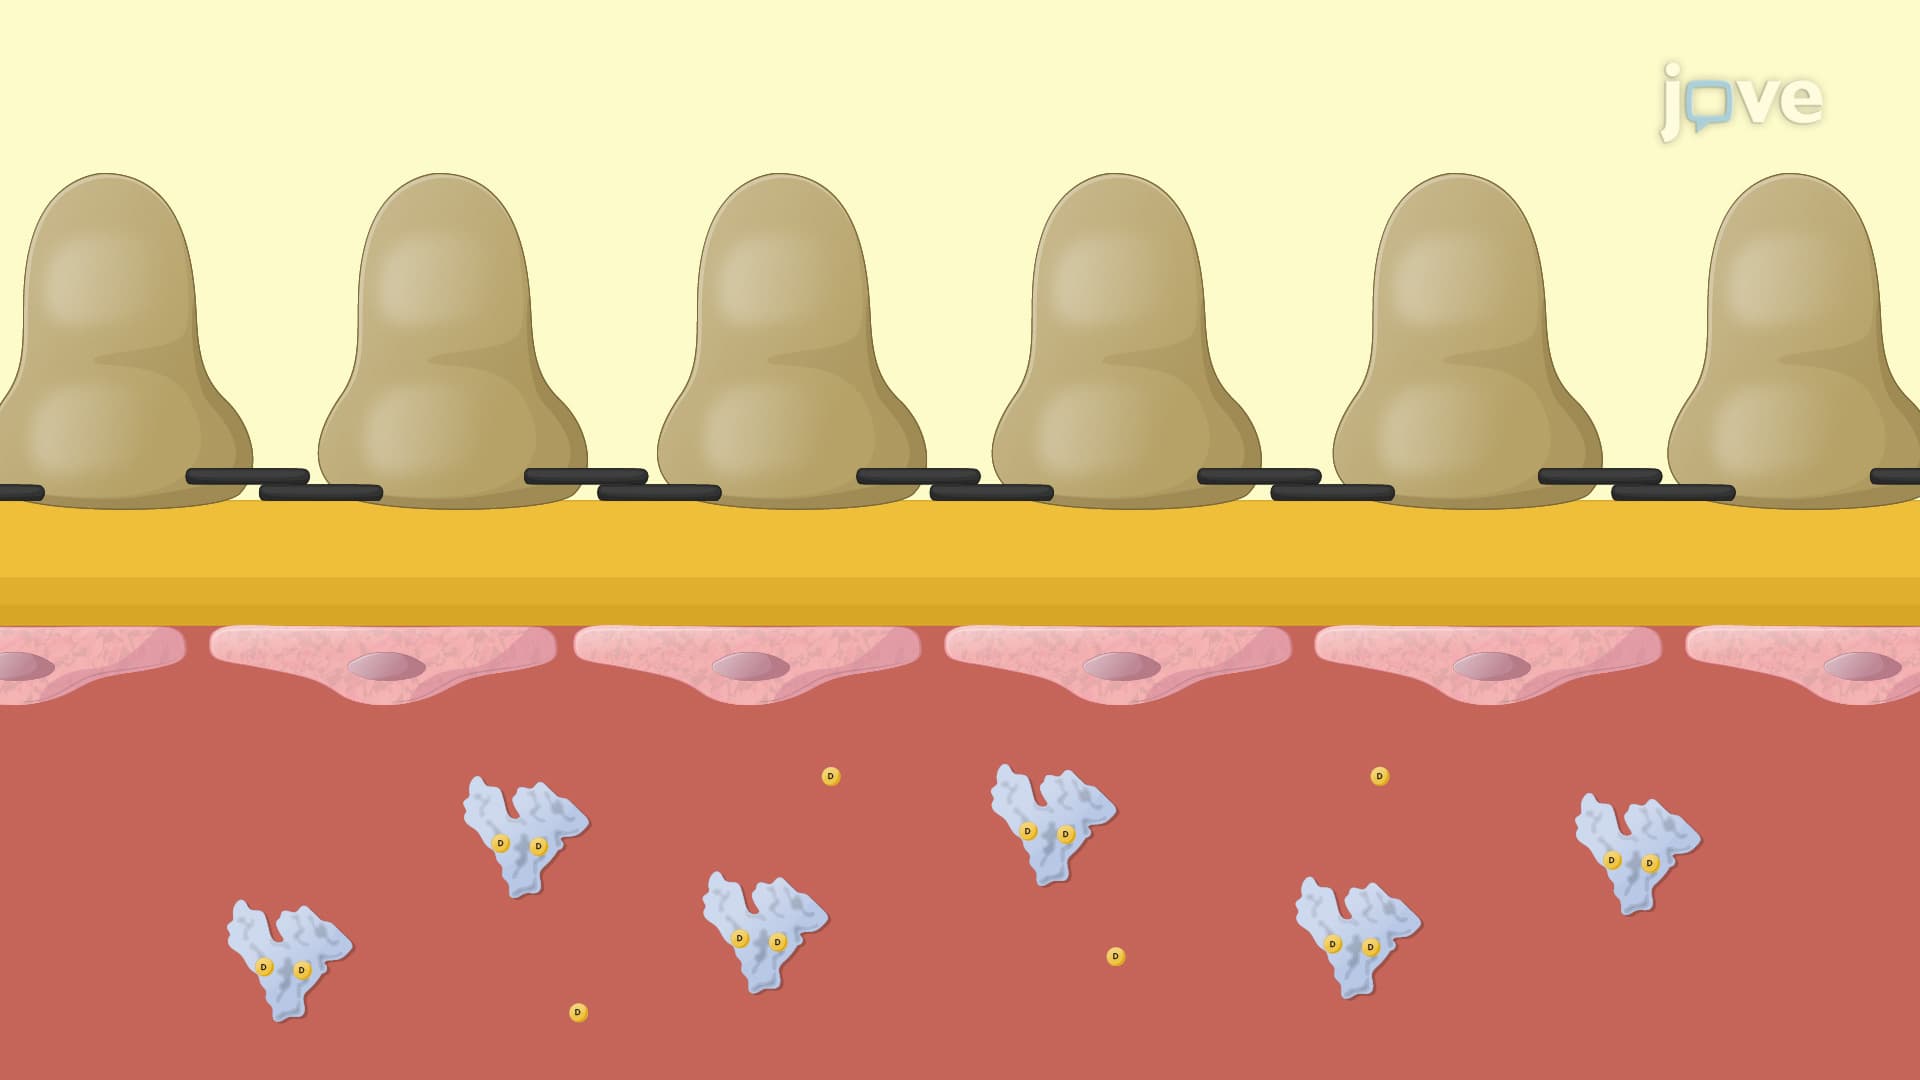
Factors Affecting Renal Clearance: Drug Distribution and Drug Interactions
One important factor is the relationship between renal clearance and the apparent volume of distribution. Renal clearance tends to be inversely proportional to the apparent volume of distribution. Drugs with an extensive distribution volume or those...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:31
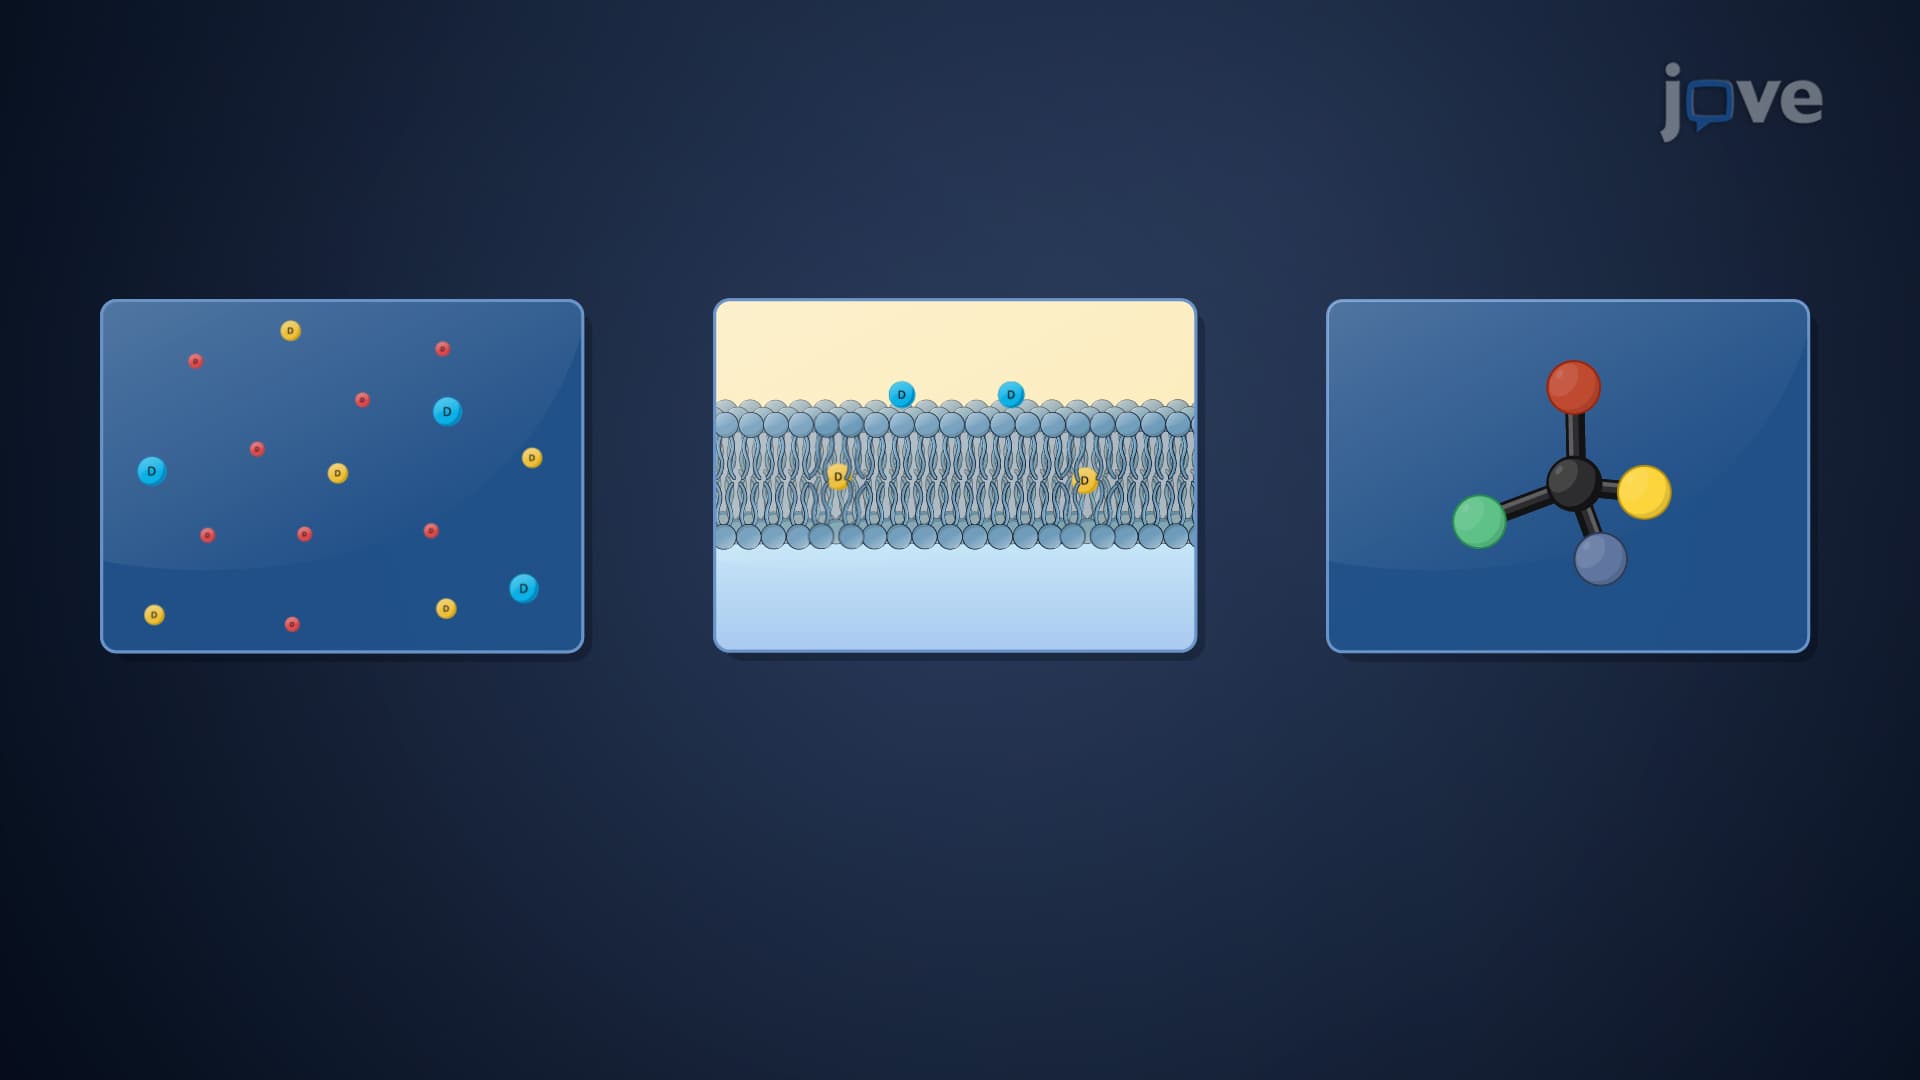
Factors Affecting Renal Clearance: Drug's Physicochemical Properties and Plasma Levels
One important factor is the drug's molecular size. The kidneys readily excrete smaller molecules below 300 Daltons (Da). On the other hand, molecules weighing between 300 and 500 Da are excreted through both urine and bile. Larger molecules above 500 Da tend to be excreted less...