Related Experiment Video
Updated: May 24, 2026

A Novel Rescue Technique for Difficult Intubation and Difficult Ventilation
Published on: January 17, 2011
Clinical outcomes of ventilation tube placement in children with cleft palate
Hitome Kobayashi1, Takaaki Sakuma, Naohiro Yamada
1Department of Otorhinolaryngology, Showa University School of Medicine, 1-5-8 Hatanodai, Shinagawa-ku, Tokyo 142-8666, Japan. hitomek@med.showa-u.ac.jp

Insights
Early ventilation tube (VT) placement in children with cleft palate (CP) and small mastoid air cells may prevent long-term otitis media with effusion (OME) complications. Measuring mastoid air cell area at 1 year aids in planning CP treatment.
Area of Science:
- Pediatric Otolaryngology
- Craniofacial Anomalies
- Clinical Outcomes Research
Background:
- Cleft palate (CP) is associated with an increased risk of middle ear disease.
- Chronic otitis media with effusion (OME) is a common complication in children with CP.
- Long-term clinical outcomes in CP patients require further investigation.
Purpose of the Study:
- To investigate the long-term clinical outcomes in children with cleft palate (CP).
- To evaluate the efficacy of ventilation tube (VT) placement in managing OME in CP patients.
- To identify predictors for OME prognosis in CP.
Main Methods:
- A cohort of 108 CP patients was studied with periodic microscopic ear examination.
- Ventilation tube (VT) placement was performed for chronic OME diagnosed at or after 1 year of age.
- Mastoid air cell area was measured via X-ray at 1 and 5 years; statistical analysis used bootstrap and Wilcoxon's rank-sum tests.
Main Results:
- VT placement occurred in 38% of CP patients by age 5; 30% required re-intervention after age 6.
- CP patients with VT placement by age 5 had significantly smaller mastoid air cell areas at 1 and 5 years.
- No significant difference in language development was observed between CP patients with or without VT placement.
Conclusions:
- VT placement is recommended for CP children with small mastoid air cell areas at 1 year, predicting unfavorable OME prognosis.
- CP patients treated with VT placement by age 5 require continued OME monitoring beyond age 6.
- Mastoid air cell area measurement at 1 year is a valuable tool for guiding therapeutic decisions in CP management.
Objective:
The purpose of this study was to investigate the long-term clinical outcomes in children with cleft palate.
Methods:
One hundred eight patients with cleft palate (CP) were investigated. Microscopic observation of the middle ears was performed periodically. If chronic otitis media with effusion (OME) was diagnosed at 1 year of age or later, ventilation tube (VT) placement was performed. The air-filled area of the mastoid air cells was checked on X-rays obtained at 1 and 5 years. The data from each measurement were tested statistically by the bootstrap method and Wilcoxon's rank-sum test. The clinical course from age 6 to the final examination (average 9.42 years) and the language development at 5 years were analyzed using data from the medical records of individual patients.
Results:
VT placements were performed at 5 years of age or younger in 41 CP patients (82 ears, 38%). About 30% of patients treated by VT placement at 5 years of age or younger required myringotomy and/or VT re-placement at 6 years of age or over. Ninety-five percent of patients who had not been treated by VT insertion at 5 years of age or younger showed a favorable subsequent clinical course. Patients treated by VT insertion at 5 years of age or younger had significantly smaller mastoid air cell areas as measured at 5 years of age and also at 1 year of age. No significant difference in language development was observed between the CP patients that underwent /did not undergo VT placement.
Conclusions:
VT placement should be positively undertaken in CP children who have small mastoid air cell areas as measured at 1 year of age, because an unfavorable prognosis of OME is expected in such patients. It is considered that patients treated by VT placement at 5 years of age or younger should be carefully followed up for the development of OME even after 6 years of age. Thus, measurement of the mastoid air cell area at the age of 1 year is useful for determining the therapeutic program.
Related Concept Videos
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
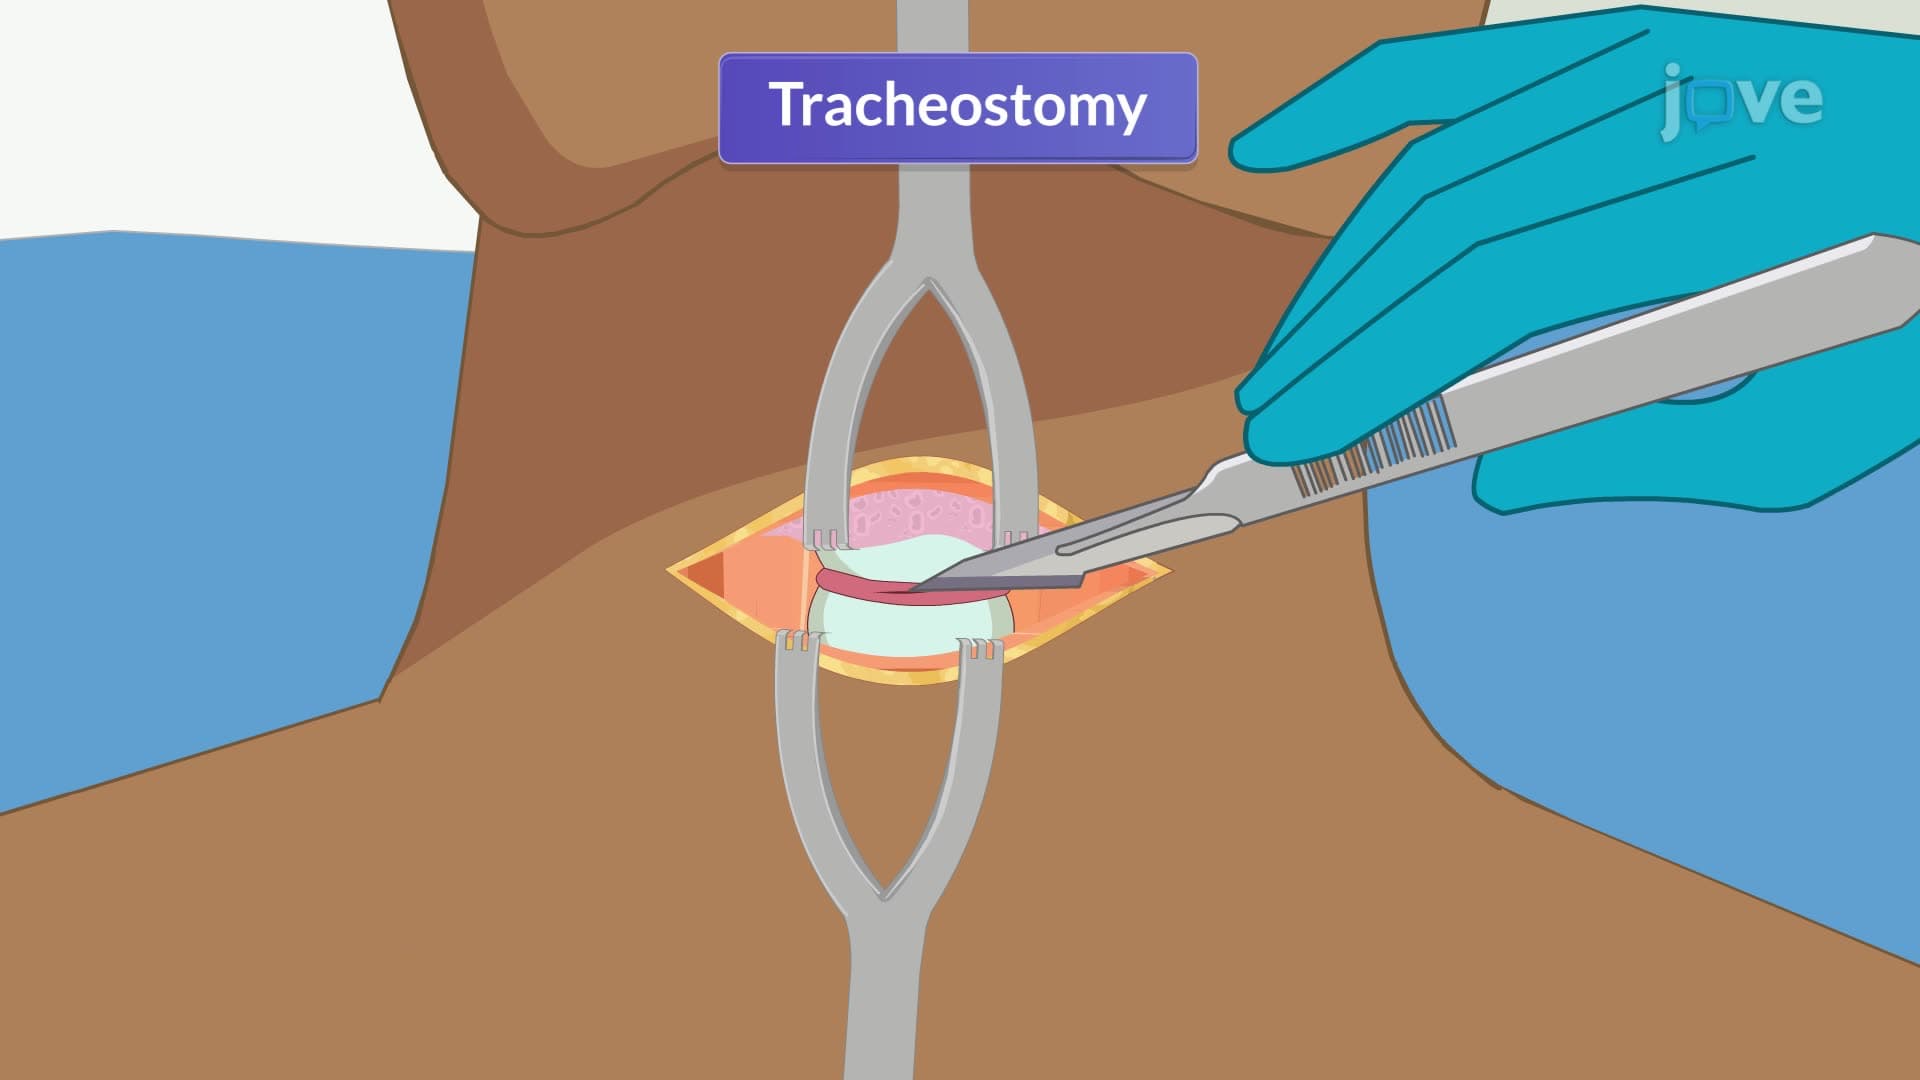
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management