Related Experiment Video
Updated: May 24, 2026
Multi-modal Pulmonary Imaging: Using Complementary Information from CT and Hyperpolarized 129Xe MRI to Evaluate Lung Structure-Function
Published on: April 12, 2024
Respiratory variation of the extrahepatic bile duct: evaluation with deep inspiratory and expiratory MRCP
Katsuyoshi Ito1, Ayame Shimizu, Masahiro Tanabe
1Department of Radiology, Yamaguchi University School of Medicine, Ube, Yamaguchi 755-8505, Japan. itokatsu@med.kawasaki-m.ac.jp

Purpose:
The purpose of the study was to evaluate the respiratory variation of the extrahepatic bile duct in morphology including shape, length and duct diameter on the breath-hold magnetic resonance cholangiopancreatography (MRCP) obtained during deep inspiration and deep expiration in patients with or without biliary diseases.
Materials And Methods:
This study included 102 patients with or without biliary diseases. Breath-hold MRCP was obtained twice during the end-inspiration and the end-expiration. MRCP images were evaluated for the length, maximal diameter and "bowing" of the extrahepatic bile duct.
Results:
In the normal group, the mean maximal diameter of the extrahepatic bile duct was significantly larger on the end-inspiratory MRCP (8.0 ± 2.0 mm) than on the end-expiratory MRCP (7.3 ± 1.8 mm) (P<.0001), while it was not significantly different in the dilated group. In the normal group, 25 (39%) of 65 patients had an increase in the mean maximal diameter of more than 1 mm at the end-inspiration, whereas 4 (11%) of 37 patients in the dilated group had it. The bowing of the extrahepatic bile duct on the end-inspiratory MRCP was observed in 60 (92%) of 65 normal patients, while it was seen in 22 (60%) of 37 patients with biliary dilatation (P<.0001).
Conclusion:
Deep inspiratory and expiratory MRCP demonstrated the respiratory variations of the extrahepatic bile duct in the shape (bowing), length and maximal duct diameter in patients with nondilated bile ducts. Awareness of this normal phenomenon will be important for the correct interpretation of MRCP in patients with or without biliary diseases.
More Related Videos
Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:15
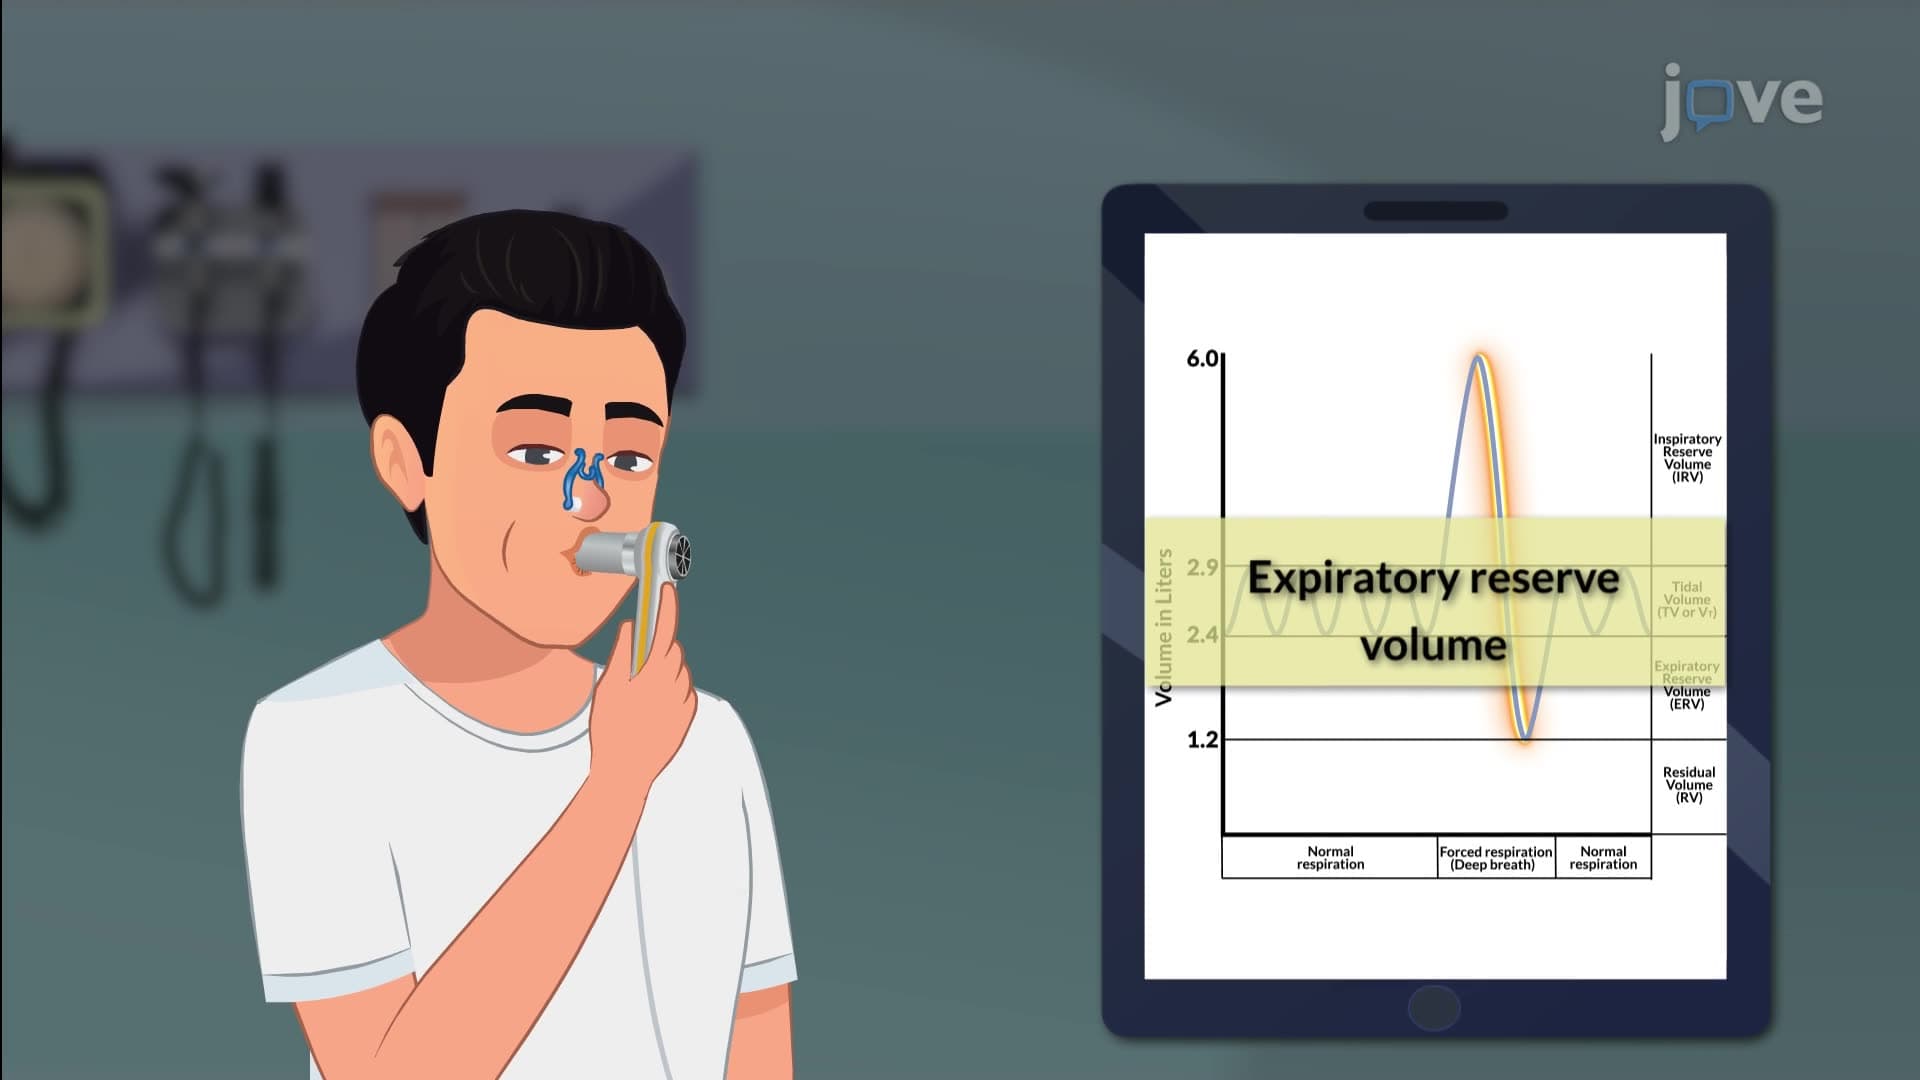
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:29
Physical Assessment of the Respiratory Tract III: Percussion
Percussion in Respiratory Assessment
Percussion evaluates underlying tissue composition with audible and tactile vibrations,...