Related Experiment Video
Updated: May 24, 2026


Isokinetic Robotic Device to Improve Test-Retest and Inter-Rater Reliability for Stretch Reflex Measurements in Stroke Patients with Spasticity
Published on: June 12, 2019
Interrater reliability of clinical findings in children with possible appendicitis
Anupam B Kharbanda1, Michelle D Stevenson, Charles G Macias
1Department of Pediatrics, Columbia University College of Physicians and Surgeons, New York, New York, USA. ak493@columbia.edu

Objective:
Our objective was to determine the interrater reliability of clinical history and physical examination findings in children undergoing evaluation for possible appendicitis in a large, multicenter cohort.
Methods:
We conducted a prospective, multicenter, cross-sectional study of children aged 3-18 years with possible appendicitis. Two clinicians independently evaluated patients and completed structured case report forms within 60 minutes of each other and without knowing the results of diagnostic imaging. We calculated raw agreement and assessed reliability by using the unweighted Cohen κ statistic with 2-sided 95% confidence intervals.
Results:
A total of 811 patients had 2 assessments completed, and 599 (74%) had 2 assessments completed within 60 minutes. Seventy-five percent of paired assessments were completed by pediatric emergency physicians. Raw agreement ranged from 64.9% to 92.3% for history variables and 4 of 6 variables had moderate interrater reliability (κ > .4). The highest κ values were noted for duration of pain (κ = .56 [95% confidence intervals .51-.61]) and history of emesis (.84 [.80-.89]). For physical examination variables, raw agreement ranged from 60.9% to 98.7%, with 4 of 8 variables exhibiting moderate reliability. Among physical examination variables, the highest κ values were noted for abdominal pain with walking, jumping, or coughing (.54 [.45-.63]) and presence of any abdominal tenderness on examination (.49 [.19-.80]).
Conclusions:
Interrater reliability of patient history and physical examination variables was generally fair to moderate. Those variables with higher interrater reliability are more appropriate for inclusion in clinical prediction rules in children with possible appendicitis.

Related Concept Videos
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:19
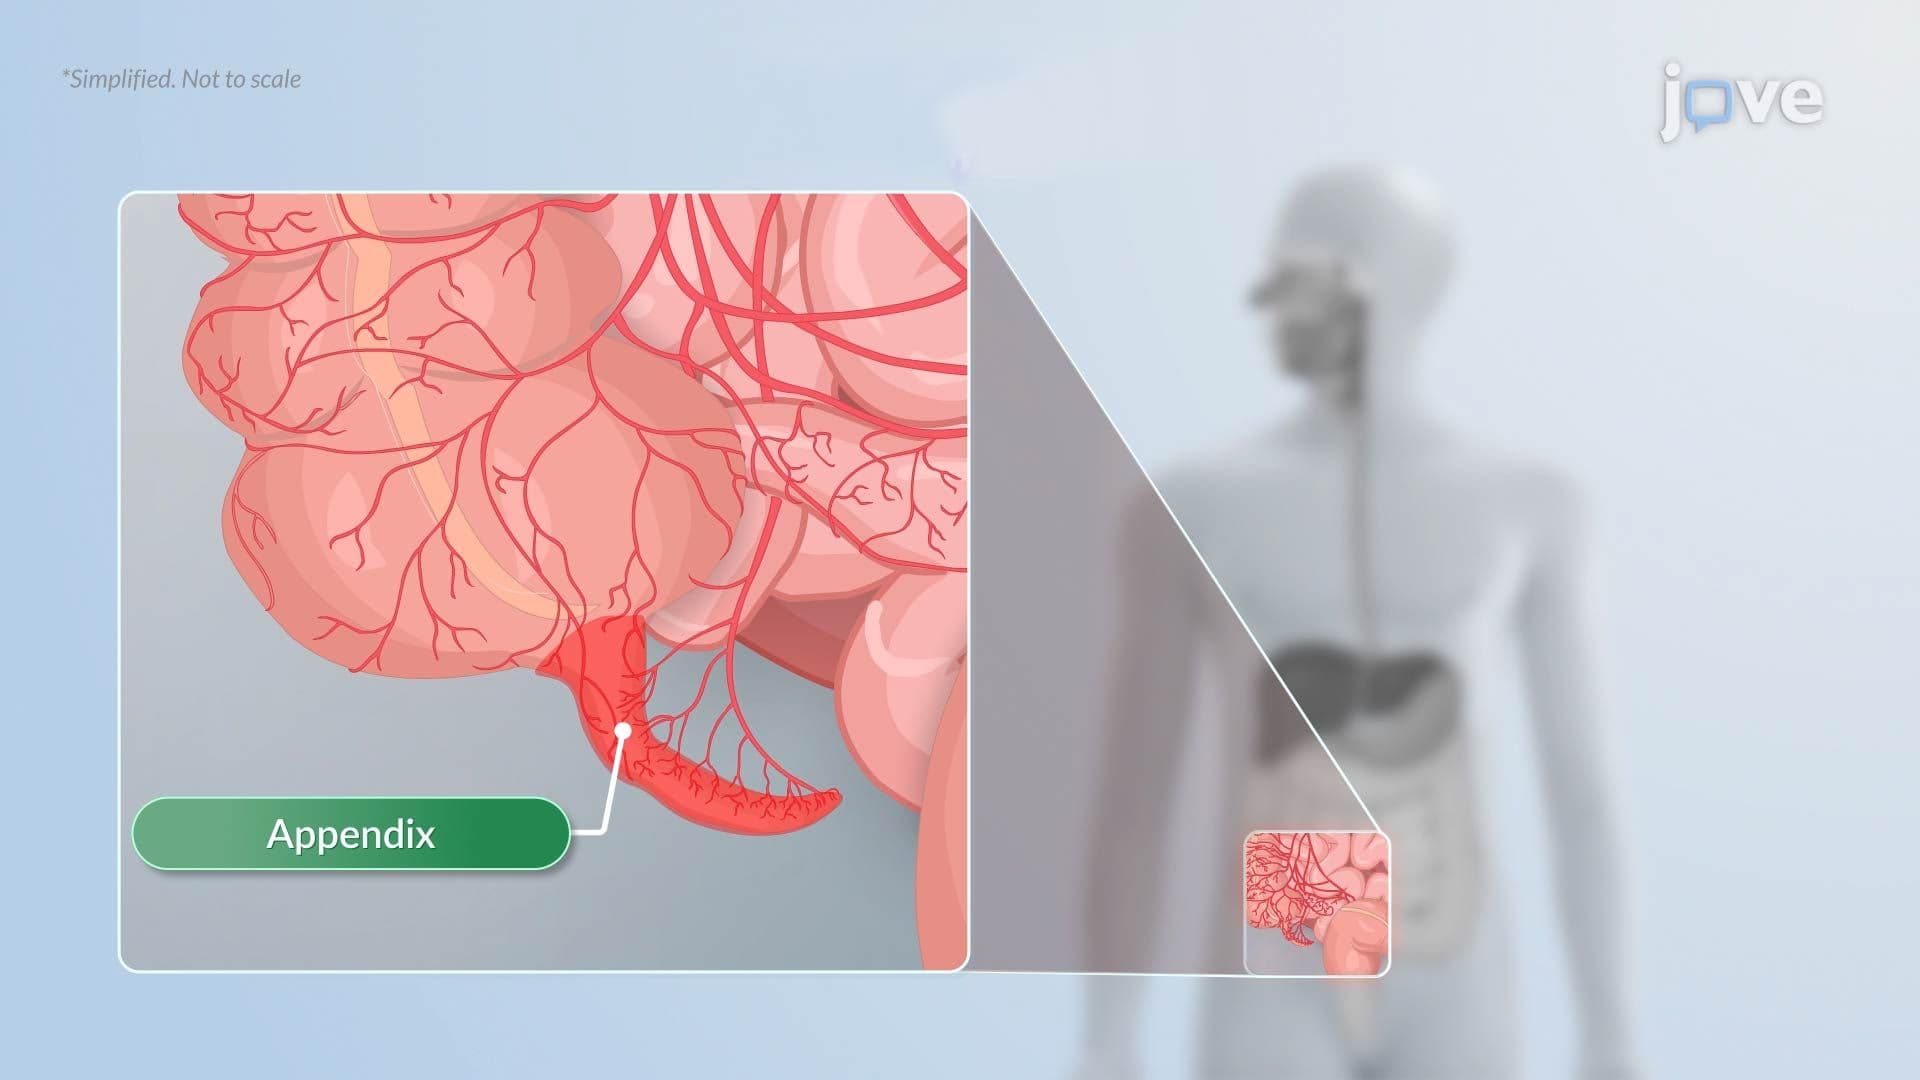
Appendicitis
 01:18
Assessment of the Abdomen II: Percussion
Percussion
Percussion is an essential...
 01:25
Assessment of the Abdomen I: Inspection and Auscultation
The abdominal examination is a cornerstone of clinical medicine, serving as a critical tool in diagnosing various gastrointestinal (GI) diseases. It involves a systematic approach that includes inspection and auscultation, each with distinct yet complementary roles in assessing the abdomen. This article will delve into these two primary methods healthcare professionals use to examine the abdomen.
Inspection of the Abdomen
The first step in any abdominal examination is inspection.
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.