The WATCHMAN left atrial appendage closure device for atrial fibrillation
Related Experiment Video
Updated: May 24, 2026

The WATCHMAN Left Atrial Appendage Closure Device for Atrial Fibrillation
Published on: February 28, 2012
Sven Möbius-Winkler1, Marcus Sandri, Norman Mangner
1University of Leipzig Heart Center, Leipzig, Germany. moes@medizin.uni-leipzig.de

Insights
Atrial fibrillation (AF) patients at risk for stroke can benefit from the WATCHMAN device, which closes the left atrial appendage (LAA) to prevent clot formation and embolism.
Area of Science:
- Cardiology
- Medical Devices
- Interventional Cardiology
Background:
- Atrial fibrillation (AF) is a common arrhythmia, increasing stroke risk.
- Current treatments like anticoagulants have limitations, including bleeding risks and monitoring needs.
- The left atrial appendage (LAA) is a primary source of AF-related emboli.
Purpose of the Study:
- To demonstrate the procedure for implanting the WATCHMAN Left Atrial Appendage Closure Device.
- To provide an alternative stroke prevention strategy for AF patients.
- To highlight a minimally invasive approach for LAA exclusion.
Main Methods:
- Transseptal puncture via femoral vein access under fluoroscopic guidance.
- Guidewire and sheath placement into the left atrium and LAA.
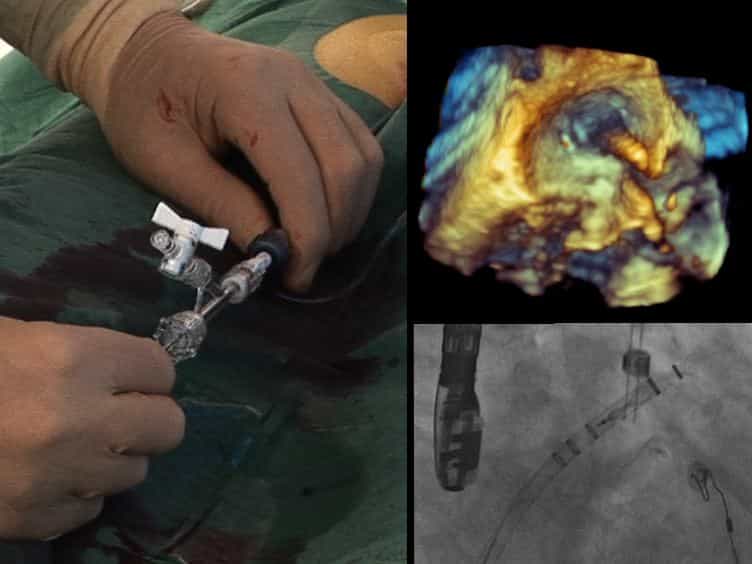
- Deployment and confirmation of the WATCHMAN device within the LAA using fluoroscopy and TEE.
Main Results:
- Successful implantation of the WATCHMAN device in the LAA.
- Confirmation of device placement and sealing via imaging.
- Demonstration of a feasible procedural technique for LAA closure.
Conclusions:
- The WATCHMAN device offers a percutaneous LAA closure option for AF patients.
- This procedure provides an alternative to long-term anticoagulation for stroke prevention.
- LAA closure may reduce the risk of thromboembolic events in AF.
Abstract:
Atrial fibrillation (AF) is the most common cardiac arrhythmia, affecting an estimated 6 million people in the United States (1). Since AF affects primarily elderly people, its prevalence increases parallel with age. As such, it is expected that 15.9 million Americans will be affected by the year 2050 (2). Ischemic stroke occurs in 5% of non-anticoagulated AF patients each year. Current treatments for AF include rate control, rhythm control and prevention of stroke (3). The American College of Cardiology, American Heart Association, and European Society of Cardiology currently recommended rate control as the first course of therapy for AF (3). Rate control is achieved by administration of pharmacological agents, such as β-blockers, that lower the heart rate until it reaches a less symptomatic state (3). Rhythm control aims to return the heart to its normal sinus rhythm and is typically achieved through administration of antiarrhythmic drugs such as amiodarone, electrical cardioversion or ablation therapy. Rhythm control methods, however, have not been demonstrated to be superior to rate-control methods (4-6). In fact, certain antiarrhythmic drugs have been shown to be associated with higher hospitalization rates, serious adverse effects (3), or even increases in mortality in patients with structural heart defects (7). Thus, treatment with antiarrhythmics is more often used when rate-control drugs are ineffective or contraindicated. Rate-control and antiarrhythmic agents relieve the symptoms of AF, including palpitations, shortness of breath, and fatigue (8), but don't reliably prevent thromboembolic events (6). Treatment with the anticoagulant drug warfarin significantly reduces the rate of stroke or embolism (9,10). However, because of problems associated with its use, fewer than 50% of patients are treated with it. The therapeutic dose is affected by drug, dietary, and metabolic interactions, and thus requires detailed monitoring. In addition, warfarin has the potential to cause severe, sometimes lethal, bleeding (2). As an alternative, aspirin is commonly prescribed. While aspirin is typically well tolerated, it is far less effective at preventing stroke (10). Other alternatives to warfarin, such as dabigatran (11) or rivaroxaban (12) demonstrate non-inferiority to warfarin with respect to thromboembolic events (in fact, dabigatran given as a high dose of 150 mg twice a day has shown superiority). While these drugs have the advantage of eliminating dietary concerns and eliminating the need for regular blood monitoring, major bleeding and associated complications, while somewhat less so than with warfarin, remain an issue (13-15). Since 90% of AF-associated strokes result from emboli that arise from the left atrial appendage (LAA) (2), one alternative approach to warfarin therapy has been to exclude the LAA using an implanted device to trap blood clots before they exit. Here, we demonstrate a procedure for implanting the WATCHMAN Left Atrial Appendage Closure Device. A transseptal cannula is inserted through the femoral vein, and under fluoroscopic guidance, inter-atrial septum is crossed. Once access to the left atrium has been achieved, a guidewire is placed in the upper pulmonary vein and the WATCHMAN Access Sheath and dilator are advanced over the wire into the left atrium. The guidewire is removed, and the access sheath is carefully advanced into the distal portion of the LAA over a pigtail catheter. The WATCHMAN Delivery System is prepped, inserted into the access sheath, and slowly advanced. The WATCHMAN device is then deployed into the LAA. The device release criteria are confirmed via fluoroscopy and transesophageal echocardiography (TEE) and the device is released.