Related Experiment Video
Updated: May 24, 2026


Local Anesthetic Thoracoscopy for Undiagnosed Pleural Effusion
Published on: November 10, 2023
Indwelling pleural catheters reduce inpatient days over pleurodesis for malignant pleural effusion
Edward T H Fysh1, Grant W Waterer2, Peter A Kendall3
1Department of Respiratory Medicine, Sir Charles Gairdner Hospital, Perth; Centre for Asthma, Allergy, and Respiratory Research, University of Western Australia, Perth; School of Medicine and Pharmacology, University of Western Australia, Perth.

Background:
Patients with malignant pleural effusion (MPE) have limited prognoses. They require long-lasting symptom relief with minimal hospitalization. Indwelling pleural catheters (IPCs) and talc pleurodesis are approved treatments for MPE. Establishing the implications of IPC and talc pleurodesis on subsequent hospital stay will influence patient choice of treatment. Therefore, our objective was to compare patients with MPE treated with IPC vs pleurodesis in terms of hospital bed days (from procedure to death or end of follow-up) and safety.
Methods:
In this prospective, 12-month, multicenter study, patients with MPE were treated with IPC or talc pleurodesis, based on patient choice. Key end points were hospital bed days from procedure to death (total and effusion-related). Complications, including infection and protein depletion, were monitored longitudinally.
Results:
One hundred sixty patients with MPE were recruited, and 65 required definitive fluid control; 34 chose IPCs and 31 pleurodesis. Total hospital bed days (from any causes) were significantly fewer in patients with IPCs (median, 6.5 days; interquartile range [IQR] = 3.75-13.0 vs pleurodesis, mean, 18.0; IQR, 8.0-26.0; P = .002). Effusion-related hospital bed days were significantly fewer with IPCs (median, 3.0 days; IQR, 1.8-8.3 vs pleurodesis, median, 10.0 days; IQR, 6.0-18.0; P < .001). Patients with IPCs spent significantly fewer of their remaining days of life in hospital (8.0% vs 11.2%, P < .001, χ(2) = 28.25). Fewer patients with IPCs required further pleural procedures (13.5% vs 32.3% in pleurodesis group). There was no difference in rates of pleural infection (P = .68) and protein (P = .65) or albumin loss (P = .22). More patients treated with IPC reported immediate (within 7 days) improvements in quality of life and dyspnea.
Conclusions:
Patients treated with IPCs required significantly fewer days in hospital and fewer additional pleural procedures than those who received pleurodesis. Safety profiles and symptom control were comparable.
Insights
Indwelling pleural catheters (IPCs) significantly reduce hospital days for malignant pleural effusion patients compared to talc pleurodesis. Both treatments offer comparable safety and symptom relief, but IPCs lead to fewer subsequent procedures.
Area of Science:
- Pulmonology
- Thoracic Surgery
- Oncology
Background:
- Malignant pleural effusion (MPE) presents a poor prognosis, necessitating treatments that minimize hospital stays and maximize symptom relief.
- Indwelling pleural catheters (IPCs) and talc pleurodesis are established interventions for MPE management.
- Understanding the long-term impact of these treatments on hospital utilization is crucial for patient decision-making.
Purpose of the Study:
- To compare hospital bed days and safety outcomes between IPCs and talc pleurodesis in patients with MPE.
- To evaluate the impact of each treatment on subsequent hospitalizations and the need for further pleural interventions.
- To assess the influence of treatment choice on patient quality of life and symptom burden.
Main Methods:
- A prospective, 12-month, multicenter study involving patients with MPE who opted for either IPC or talc pleurodesis.
- Primary endpoints included total and effusion-related hospital bed days from the procedure until death or study end.
- Secondary endpoints monitored complications such as infection and protein depletion, alongside quality of life indicators.
Main Results:
- Patients receiving IPCs experienced significantly fewer total hospital bed days (median 6.5 vs. 18.0) and effusion-related bed days (median 3.0 vs. 10.0) compared to talc pleurodesis.
- IPCs were associated with a lower requirement for additional pleural procedures (13.5% vs. 32.3%) and a greater proportion of remaining life spent out of hospital (8.0% vs. 11.2%).
- No significant differences were observed in rates of pleural infection or protein/albumin loss between the groups; however, IPCs showed quicker improvements in quality of life and dyspnea.
Conclusions:
- IPCs offer a significant advantage over talc pleurodesis by substantially reducing hospital bed days and the need for re-intervention in MPE management.
- Both IPCs and talc pleurodesis demonstrate comparable safety profiles regarding infection and nutritional depletion.
- IPCs provide comparable symptom control and potentially faster relief of dyspnea, making them a favorable option for patients with MPE.

Related Concept Videos
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:30
Pleural Disorders: Types and Brief Description
 01:13
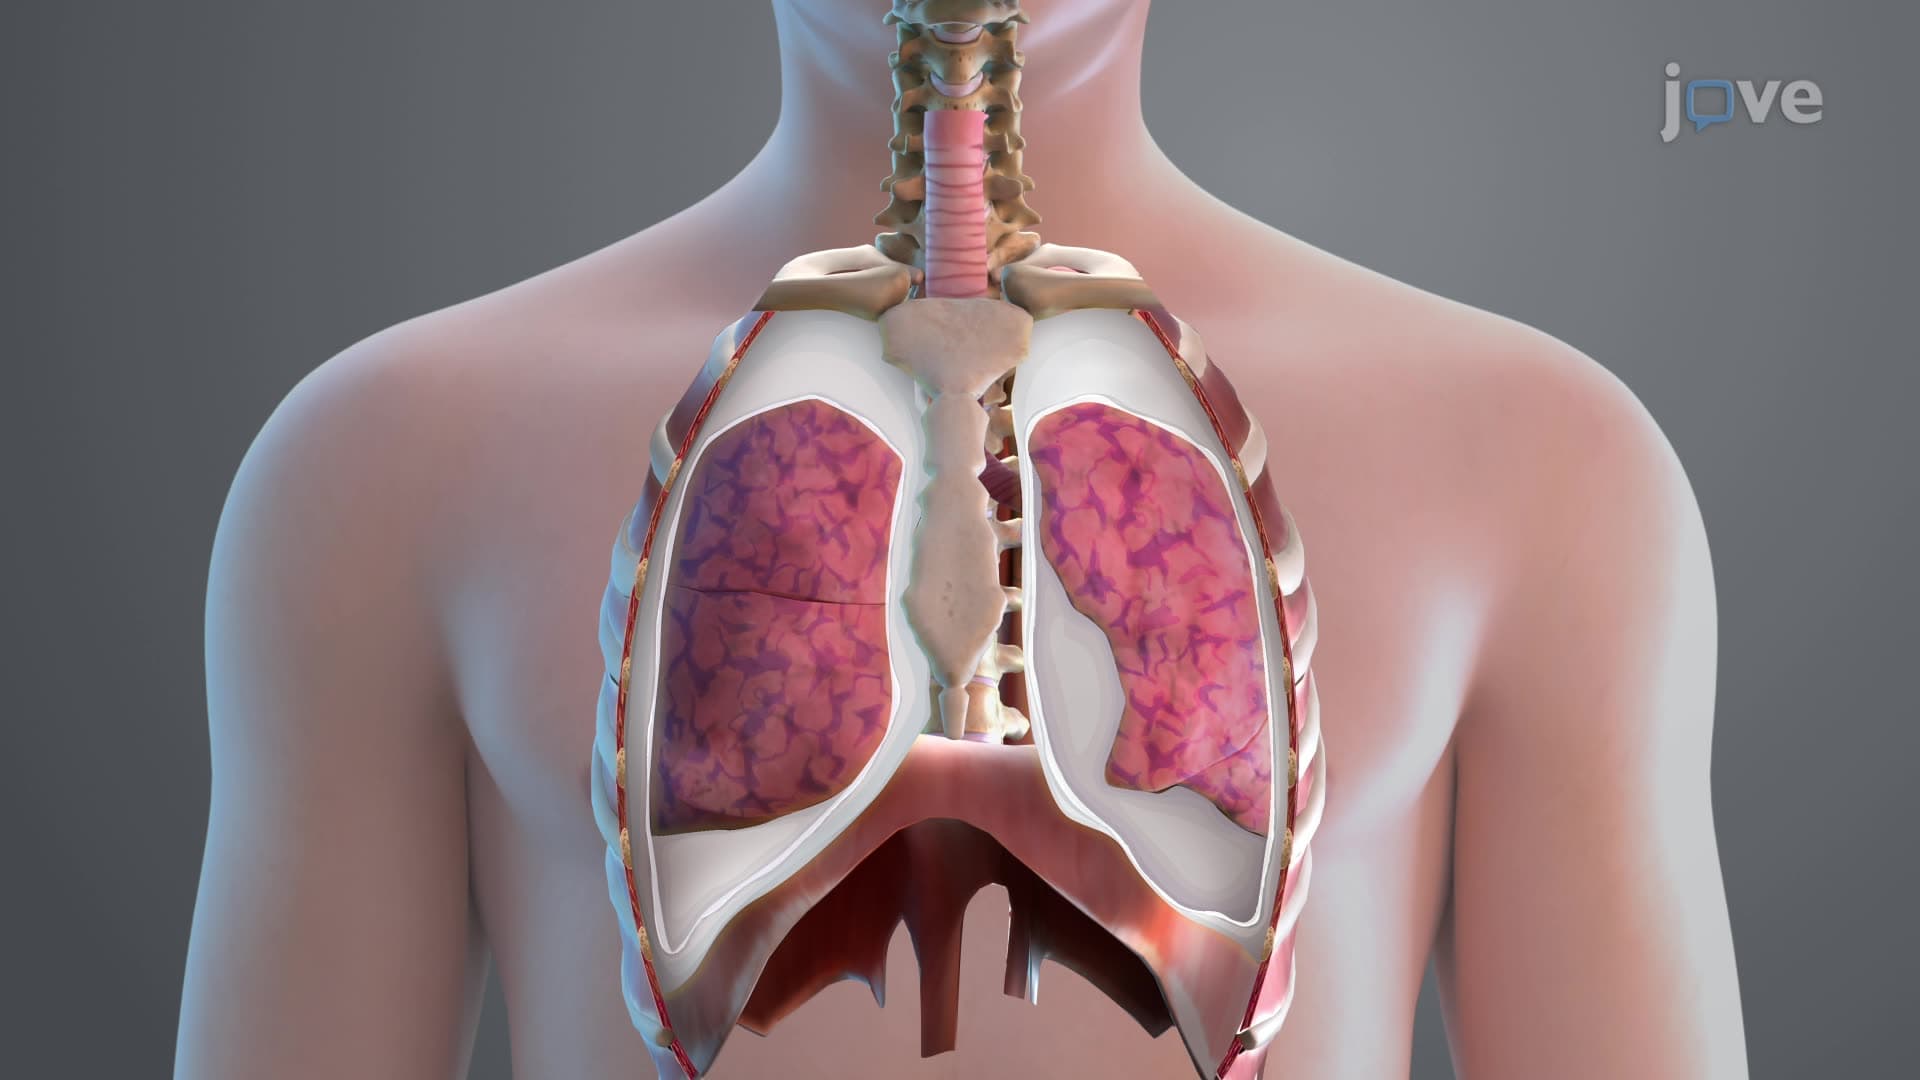
Pleura of the Lungs
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications