Related Experiment Video
Updated: May 24, 2026

Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
African fluid bolus study: implications for practice
1School of Medicine, University of Botswana, Gaborone, Botswana. david.brewster48@gmail.com

Insights
Bolus fluid therapy for severe infections in children significantly increased mortality in a large African trial. This challenges standard sepsis treatment protocols, emphasizing closer fluid monitoring in pediatric care.
Area of Science:
- Pediatric critical care medicine
- Infectious diseases
- Global health
Background:
- Bolus fluid administration is a common intervention for children with severe infections and signs of shock.
- The Fluid Expansion as Supportive Therapy (FEAST) trial investigated fluid resuscitation strategies in African children.
Purpose of the Study:
- To evaluate the impact of bolus fluid therapy versus no bolus on mortality in children with severe infections in resource-limited settings.
Main Methods:
- A high-quality randomized controlled trial involving 3170 children in Africa.
- Primary outcome was 48-hour mortality.
Main Results:
- Bolus fluid therapy was associated with significantly higher mortality compared to no bolus administration.
- Findings challenge the universal application of bolus fluid regimes for sepsis and compensated shock in pediatric advanced life support.
Conclusions:
- Intravenous fluid management, particularly bolus administration, requires critical re-evaluation in pediatric severe infections in resource-limited settings.
- Closer monitoring of fluid status is essential, and the practice of routine boluses for suspected sepsis needs careful consideration.
Abstract:
The Fluid Expansion as Supportive Therapy (FEAST) trial in an African setting without intensive care facilities found that bolus fluid therapy for severe infections (including malaria and viral infections) resulted in a significantly higher mortality than those not given a bolus. This was a high-quality study of 3170 children with 48 h mortality as the primary outcome. Despite the different setting and diseases than in a developed country context, it could be argued that this study calls into question the wisdom of bolus fluid regimes for sepsis, and perhaps even the concept of 'compensated shock' in the Advanced Paediatric Life Support protocol. Some have tried to attack the ethics of the study, but this is unjustified. The implications for paediatric practice in Africa are that intravenous fluids need to be monitored more closely, and the practice of giving boluses to every 'query septic infant and child' needs to be examined more critically.

Related Concept Videos
 01:19
One-Compartment Open Model for IV Bolus Administration: General Considerations
The drug's presence in the body is defined by an equation representing the difference between the rates of drug entry and exit. Key parameters—elimination rate constant, half-life,...
 01:18
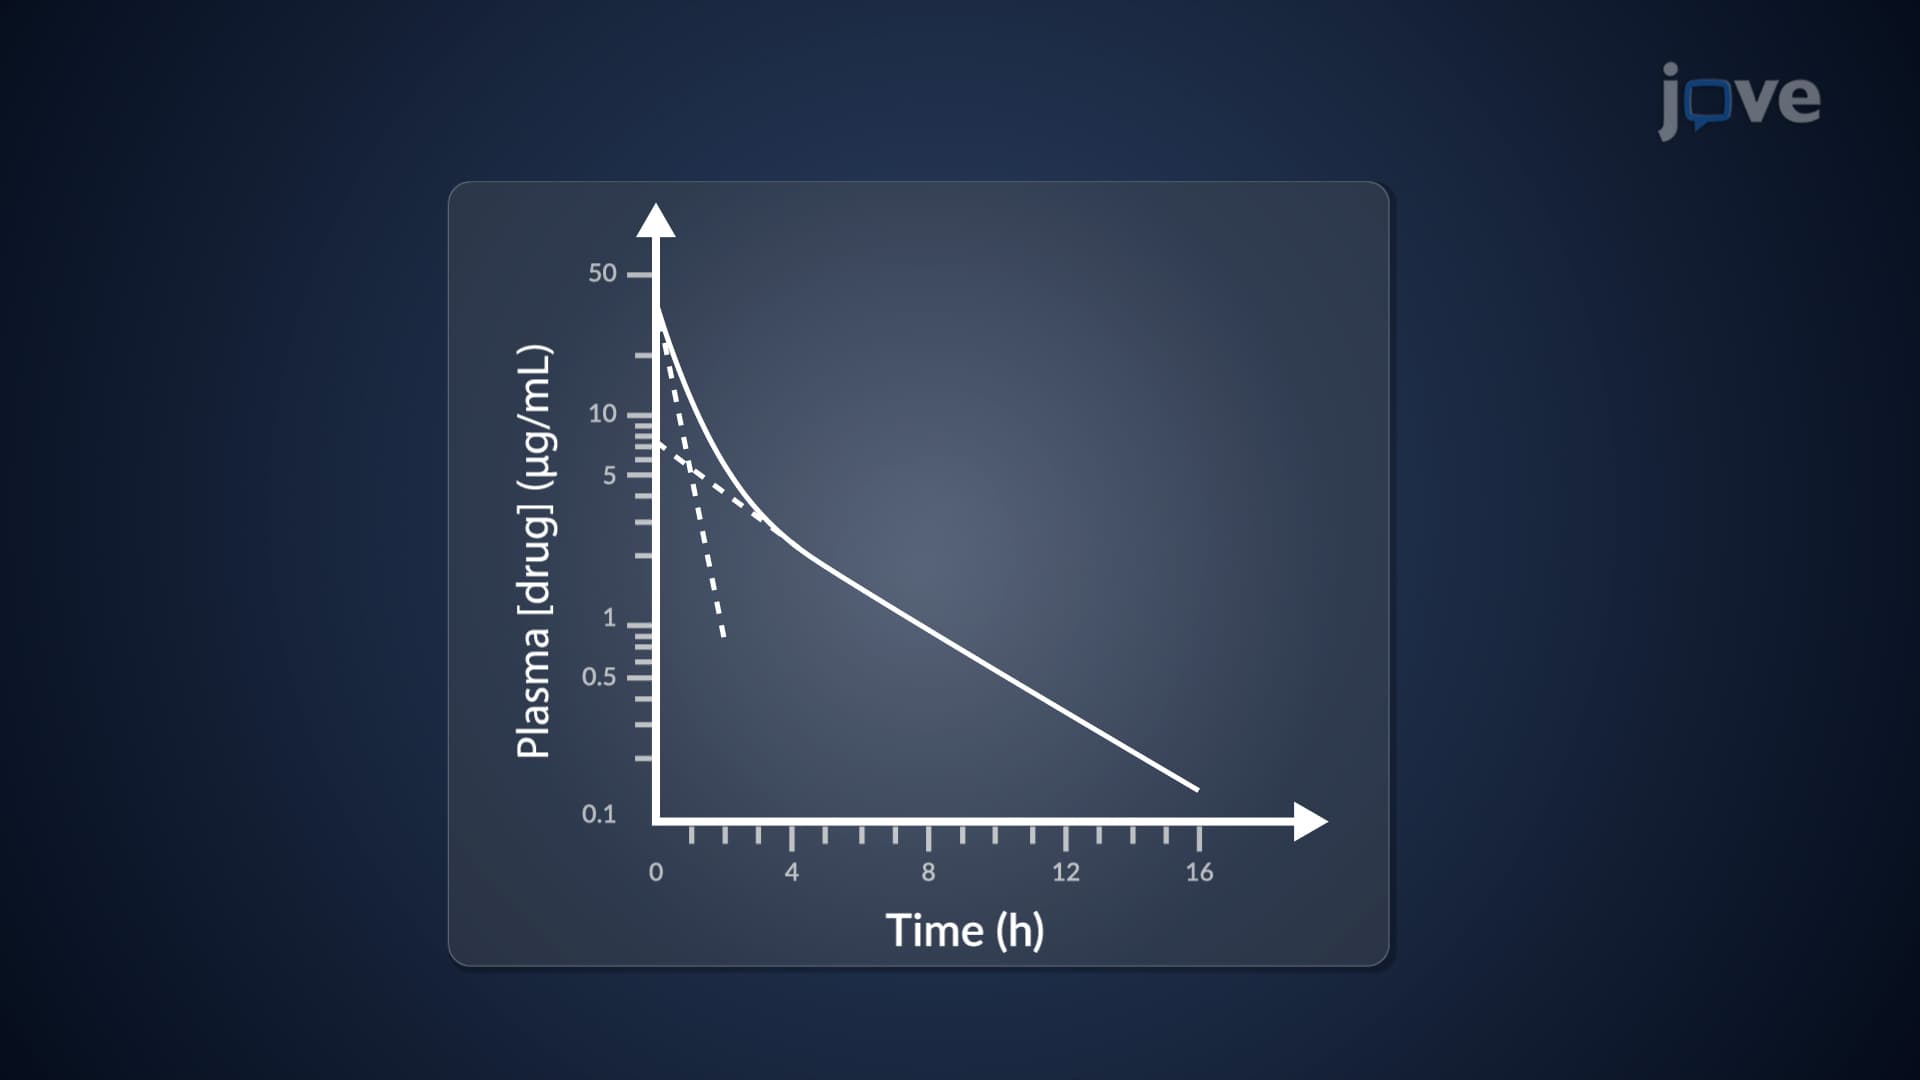
Two-Compartment Open Model: IV Bolus Administration
The disparity between drug input and the sum of drug transfer rates between...
 00:56
One-Compartment Open Model for IV Bolus Administration: Estimation of Clearance
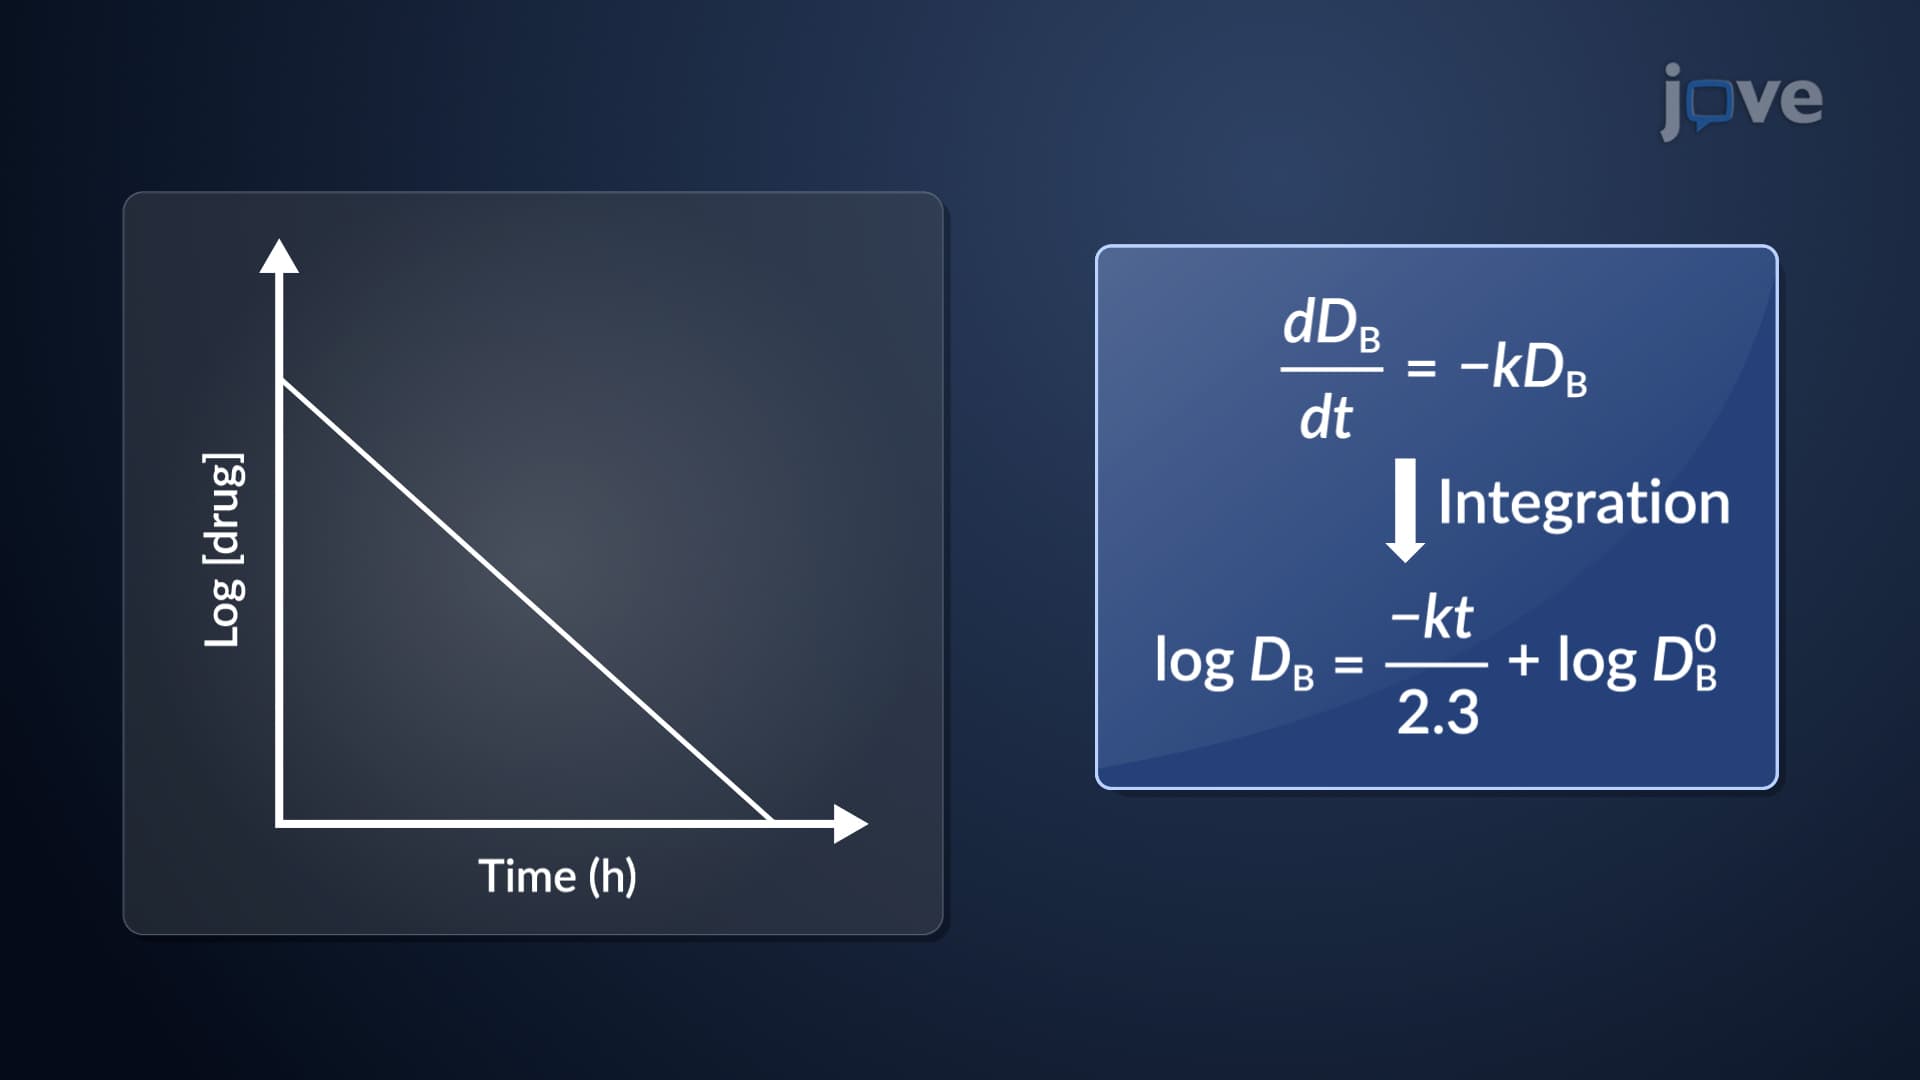
In the one-compartment open model for intravenous (IV) bolus administration, clearance is estimated by dividing the elimination rate by the plasma drug concentration. This equation leverages the elimination rate constant and the apparent...
 01:09
One-Compartment Open Model for IV Bolus Administration: Estimation of Elimination Rate Constant, Half-Life and Volume of Distribution
 00:59
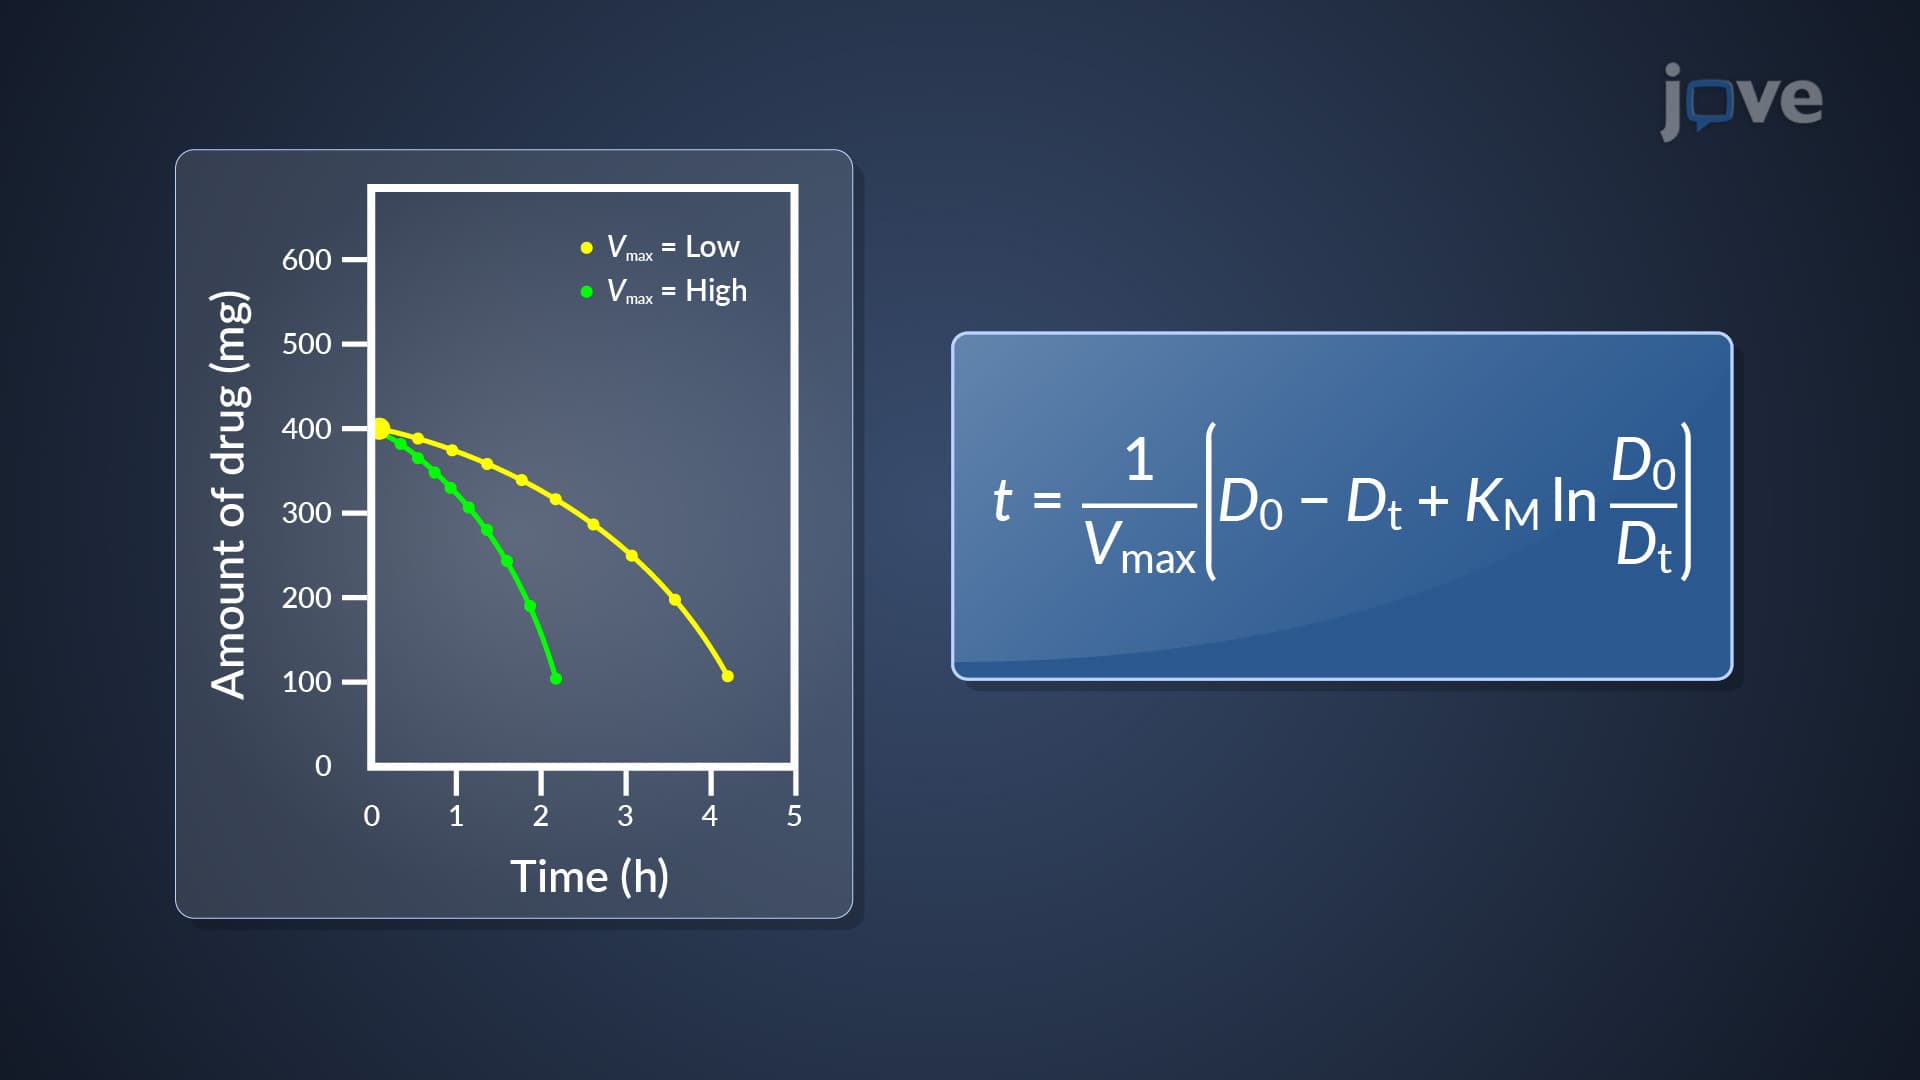
Nonlinear Pharmacokinetics: Drug Elimination for IV Bolus Injection
Following the administration of a single intravenous (IV) bolus injection, we can determine the concentration of the drug in the plasma at any given time. This calculation is achieved using a specific equation that integrates the values of Vmax and KM.
We can also...