Related Experiment Video
Updated: May 24, 2026
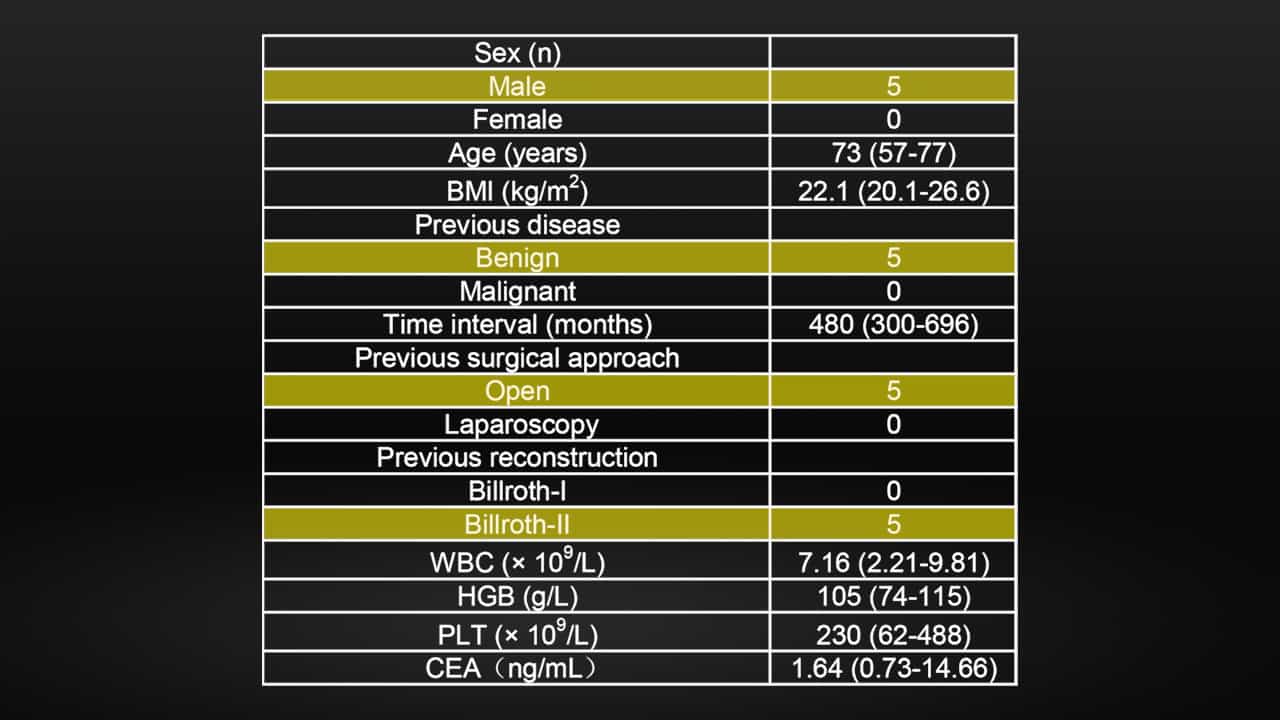

Laparoscopic Radical Gastrectomy for Remnant Gastric Cancer
Published on: October 31, 2025
Recurrence after surgical resection of gastrinoma: who, when, where and why?
Frédérique Maire1, Alain Sauvanet, Anne Couvelard
1Department of Gastroenterology and Pancreatology, Beaujon University Hospital, AP-HP, Clichy, France. frederique.maire@bjn.aphp.fr

Background:
Surgery prolongs survival in patients with gastrinomas, but postoperative recurrences are frequent and controversies still exist about the optimal surgical procedures.
Aim:
The aim of this study is to analyze biological and morphological recurrences and to search for risk factors.
Patients And Methods:
Between 1990 and 2008, 22 patients (five with multiple endocrine neoplasia type 1) who underwent curative resection for gastrinoma were evaluated every 6 months for biological and morphological recurrences. All patients were disease-free postresection.
Results:
The median postoperative follow-up was 37 months (range, 7-204 months). A biological recurrence was observed in 59% of cases, after a median time of 16.5 months (range, 7-90 months). A morphological recurrence was reported in 32% of cases, in the liver (86%) or lymph nodes (43%), after a median time of 21 months (range, 8-91 months). The median delay between biological and morphological recurrence was 3 months (range, 0-69 months). At recurrence, all patients were offered a second treatment (surgical resection in 71% of cases). One and 5 year overall survival were 100 and 76%, respectively. One and 5 year biological disease-free survival (DFS) were 76 and 27%, respectively. One and 5 year morphological DFS were 90 and 62%, respectively. Tumor size of at least 20 mm (P=0.008) and pancreatic location (P=0.04) of the primary tumor had significant effect on morphological DFS. Overall survival was significantly lower in patients with primary tumor of at least 20 mm (P=0.01).
Conclusion:
(a) Recurrence occurs in nearly two out of three patients operated upon for gastrinoma, most often detected through biological tests; (b) lymph nodes and liver are the most frequent sites of relapse and patients benefit from second treatment; (c) risk factors for recurrences are as follows: size of at least 20 mm; and the pancreatic location of the primary tumor.
Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Gastritis II: Pathophysiology
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...