Related Experiment Video
Updated: May 24, 2026

An “All-laser” Endothelial Transplant
Published on: July 6, 2015
Microbubble incision as a new rescue technique for big-bubble deep anterior lamellar keratoplasty with failed bubble
Stephan Riss1, Ludwig M Heindl, Björn O Bachmann
1Department of Ophthalmology, University of Erlangen-Nürnberg, Erlangen, Germany.

Purpose:
To describe a new surgical technique allowing dissection down to Descemet membrane in big-bubble deep anterior lamellar keratoplasty (DALK) with failed big-bubble formation (the "microbubble incision technique").
Methods:
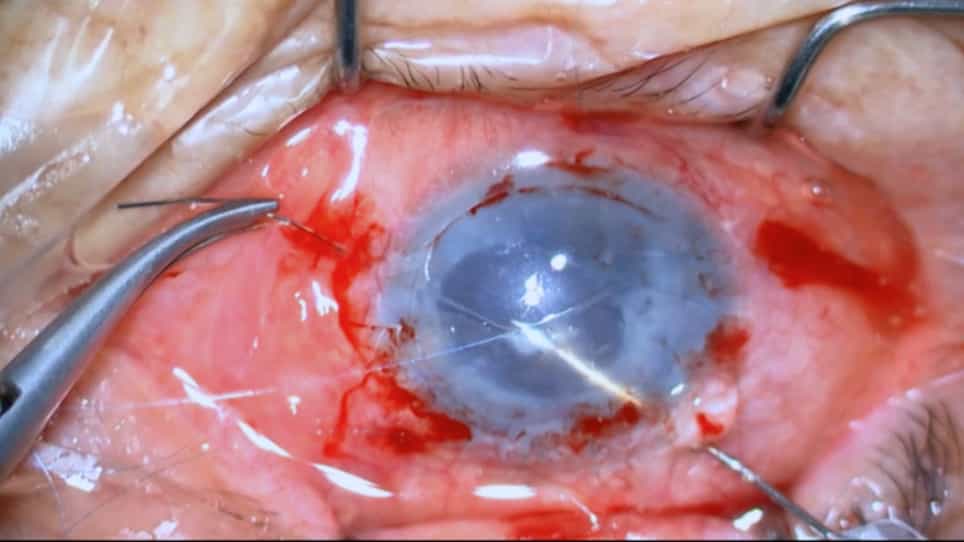
This is an interventional case series of 10 consecutive patients with keratoconus undergoing intended big-bubble DALK with failure to establish a normal big bubble. In all patients, repeated air injections into the stroma were performed, leaving a whitish colored stroma. Lamellar dissection as far down as possible was then performed within this white tissue. As soon as the anterior chamber was visible, a large remaining intrastromal air bubble was incised with a sharp 15-degree knife introduced perpendicular to the tissue to open up this predescemetic bubble. If deeper air bubbles were still visible, this approach was repeated. Using a blunt spatula, this new layer was then prepared and viscodissection performed.
Results:
Using this novel approach, in 9 of the 10 patients, it was possible to dissect down to Descemet membrane. Macroperforation made conversion to penetrating keratoplasty necessary in 1 patient. Microperforations not necessitating conversion occurred in 2 patients. All 9 patients with "rescued" DALK had an uneventful postoperative course and had a mean visual acuity of 20/63 ± 20/125 (range, 20/500-20/50) and a mean endothelial cell count of 1672 ± 163 cells per square millimeter (range, 1493-1867 cells/mm) at 3 months.
Conclusions:
Microbubble incision is a new rescue technique for big-bubble DALK patients without bubble formation allowing for a safer dissection down to Descemet membrane.