Related Experiment Video
Updated: May 24, 2026
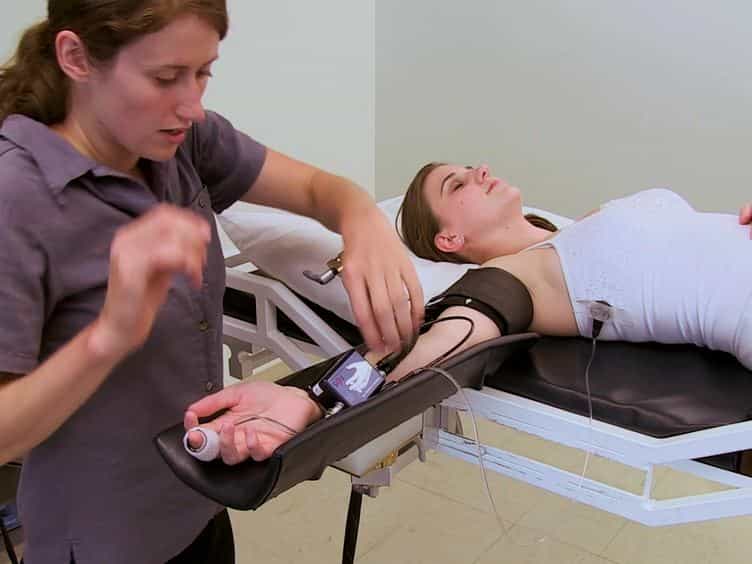

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
MSNA during prolonged post-faint hypotension
J Rozenberg1, W Wieling, I K Schon
1Department of Internal Medicine, Academic Medical Center, University of Amsterdam, Amsterdam, The Netherlands. Josien.Rozenberg@student.uva.nl

Background:
Following tilt-induced syncope, blood pressure usually recovers rapidly after tilt back to the horizontal position. However, in some patients, hemodynamic recovery is delayed, a condition recently termed "prolonged post-faint hypotension" (PPFH). The mechanism is thought to be mediated by increased vagal outflow rather than exaggerated peripheral vasodilatation and sympathetic withdrawal. To date, no muscle sympathetic nerve activity (MSNA) recordings have been reported in this condition, so we aimed to confirm that neither vasodilatation nor MSNA withdrawal was responsible.
Objectives:
To retrospectively select patients with satisfactory recordings of continuous BP and MSNA during tilt-induced syncope. To compare hemodynamic and MSNA profiles in patients with PPFH to patients with normal recovery (NR) after tilt-back.
Methods:
All patients were studied in Christchurch, New Zealand, between 1998 and 2008 using continuous arterial BP monitoring, and microneurographic recordings of MSNA from the right leg. Only patients with satisfactory BP and MSNA data throughout baseline, head-up tilt and presyncope were selected. Stroke volume (SV), cardiac output (CO), and total peripheral resistance (TPR) were derived using Modelflow. After baseline measurements, patients were tilted to the head-up 60° position and given GTN spray if asymptomatic after 20 min. Following the onset of presyncope, patients were tilted slowly back to the horizontal. PPFH was defined as systolic BP <85 mmHg for at least 2 min after tilt-back. Measurements were averaged at baseline, early tilt, presyncope, early and late recovery. Within-group comparisons were made between baseline and all other time points. Between-group comparisons were made over all time points.
Results:
Patients with PPFH (7 males, age 46 ± 5 years, n = 8) and with NR (8 males, age 47 ± 6 years, n = 8) were selected. Presyncope was provoked by GTN in 4/8 patients in each group. In both groups, MAP remained below baseline during early and late recovery: PPFH 84 ± 5 versus 51 ± 5 and 64 ± 5 mmHg (p = 0.001, p = 0.001); NR 104 ± 5 versus 83 ± 5 and 93 ± 5 mmHg (p = 0.001, p = 0.03). However, MAP and HR were lower in the PPFH group (p = 0.004, p = 0.023). During early recovery, CO remained below baseline only in the PPFH group (p = 0.001), whereas TPR remained constant in both groups. In both groups, all MSNA indices tended to remain above baseline levels during early and late recovery. PPFH 25 ± 2 increased to 31 ± 6 and 29 ± 4 bursts/min (p = 0.09, 0.02); NR 23 ± 3 increased to 33 ± 3 and 34 ± 3 bursts/min (p = 0.06, 0.01).
Conclusions:
PPFH does not appear to be mediated by exaggerated vasodilatation or sympathetic withdrawal. Delayed recovery of cardiac output by increased vagal outflow is a more likely mechanism.
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart beats)...
 01:26
Cardiac Catheterization IV: Nursing Management
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:22
Stages of General Anesthesia
 01:20
Angina V: Nursing Management