Related Experiment Video
Updated: May 24, 2026

Use of Ultra-high Field MRI in Small Rodent Models of Polycystic Kidney Disease for In Vivo Phenotyping and Drug Monitoring
Published on: June 23, 2015
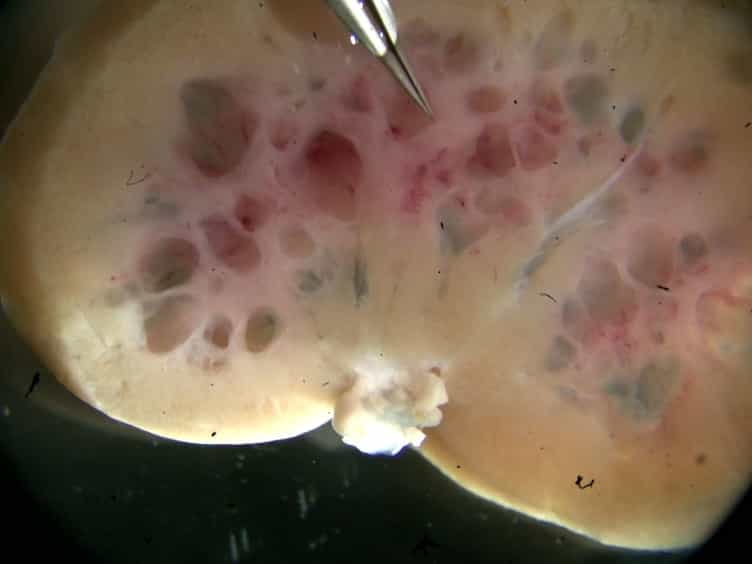
Boy with autosomal recessive polycystic kidney and autosomal dominant polycystic liver disease
Andrea Zingg-Schenk1, Jürg Caduff, Silvia Azzarello-Burri
1Children's Hospital Lucerne, 6000, Lucerne, Switzerland.

Insights
Autosomal recessive polycystic kidney disease (ARPKD) and autosomal dominant polycystic liver disease (PCLD) can co-occur. This case highlights a child with both conditions who experienced a benign clinical outcome, emphasizing the need for long-term monitoring.
Area of Science:
- Genetics and rare diseases
- Pediatric nephrology and hepatology
- Molecular diagnostics
Background:
- Autosomal recessive polycystic kidney disease (ARPKD) exhibits significant phenotypic variability.
- Autosomal dominant polycystic liver disease (PCLD) typically does not manifest in childhood.
Observation:
- A pediatric case presented with co-occurring ARPKD and PCLD.
- The patient exhibited symptoms of pyelonephritis and urosepsis at 16 days old.
- Genetic analysis identified compound heterozygous mutations in PKHD1 (ARPKD) and a missense mutation in PRKCSH (PCLD).
Findings:
- The patient demonstrated enlarged kidneys and hyperechogenic renal medulla and liver parenchyma.
- Genetic testing confirmed compound heterozygous mutations in PKHD1 and a PRKCSH mutation.
- At 13 years of age, the patient maintained normal renal and liver function without portal hypertension.
Implications:
- Co-occurrence of ARPKD and PCLD can present with a benign clinical course in childhood.
- The phenotypic variability of ARPKD is further illustrated in this case.
- Long-term follow-up is crucial for patients with co-existing ARPKD and PCLD.
Background:
Autosomal recessive polycystic kidney disease (ARPKD) shows a great phenotypic variability between patients, ranging from perinatal demise to mildly affected adults. Autosomal dominant polycystic liver disease (PCLD) does not manifest in childhood.
Case-Diagnosis/Treatment:
A boy was reported with the co-occurrence of ARPKD and PCLD. He presented at the age of 16 days with pyelonephritis and urosepsis. Subsequent investigations showed enlarged kidneys and hyperechogenic renal medulla and liver parenchyma. Genetic analysis revealed compound heterozygous mutations in the PKHD1 gene (p.Arg496X and p.Ser1862Leu). After his mother was diagnosed with PCLD, the finding of a liver cyst on ultrasound prompted analysis of the PRKCSH gene, revealing a missense mutation (p.Arg139His). At the most recent follow-up at 13 years of age, the patient's course and clinical examination was uneventful with normal renal and liver function without evidence of portal hypertension.
Conclusions:
The patient with ARPKD and PCLD has so far demonstrated a benign clinical outcome, consistent with the great phenotypic variability of ARPKD and, apart from the liver cyst, asymptomatic manifestation of PCLD in childhood. However, close long-term follow-up is mandatory.

Related Concept Videos
 01:35
Pedigree Analysis
 01:43
Sex-linked Disorders
 01:20
Inborn Errors of Metabolism
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation, but...
 01:22
Lysosomal Hydrolases
 01:11
Genetic Lingo