Related Experiment Video
Updated: May 24, 2026


Ultrasonography of the Adult Male Urinary Tract for Urinary Functional Testing
Published on: August 14, 2019
Combination pharmacological therapies for the management of benign prostatic hyperplasia
Seth A Cohen1, J Kellogg Parsons
1Division of Urology, UC San Diego Medical Center, San Diego, CA 92103-8897, USA.

Abstract:
Benign prostatic hyperplasia (BPH) is a highly prevalent condition of older men caused by unregulated growth of the prostate gland. Clinical trials of medical therapy for BPH have consistently demonstrated that combined therapy with an α(1)-adrenergic receptor (AR) antagonist and a 5α-reductase inhibitor is superior to either agent alone. The addition of anticholinergic therapy to a treatment regimen could effectively improve symptoms in men with persistent storage lower urinary tract symptoms (LUTS) who have not seen a benefit with an α(1)-AR antagonist or 5α-reductase inhibitor. Among α(1)-AR antagonists, doxazosin, terazosin, tamsulosin, and alfuzosin, although with slight differences in adverse event profiles, are equivalent in effectiveness and efficacy. No data in the form of direct comparator trials exist to suggest a difference in clinical efficacy of finasteride and dutasteride, the two 5α-reductase inhibitors currently available. Current American Urological Association guidelines do not recommend phytotherapy or dietary supplements in any combination for the medical management of BPH. The current literature supports the safety and efficacy of the combination of an α(1)-AR antagonist and a 5α-reductase inhibitor in the treatment of symptomatic BPH and, in select patients, the use of an α(1)-AR antagonist and anticholinergic medication in the treatment of LUTS suggestive of BPH.
More Related Videos
 06:04
Surgical Treatment for Benign Prostatic Hyperplasia: Holmium Laser Enucleation of the Prostate (HoLEP).
Published on: March 6, 2018
 08:38
Renal Capsule Xenografting and Subcutaneous Pellet Implantation for the Evaluation of Prostate Carcinogenesis and Benign Prostatic Hyperplasia
Published on: August 28, 2013
Related Concept Videos
 01:22
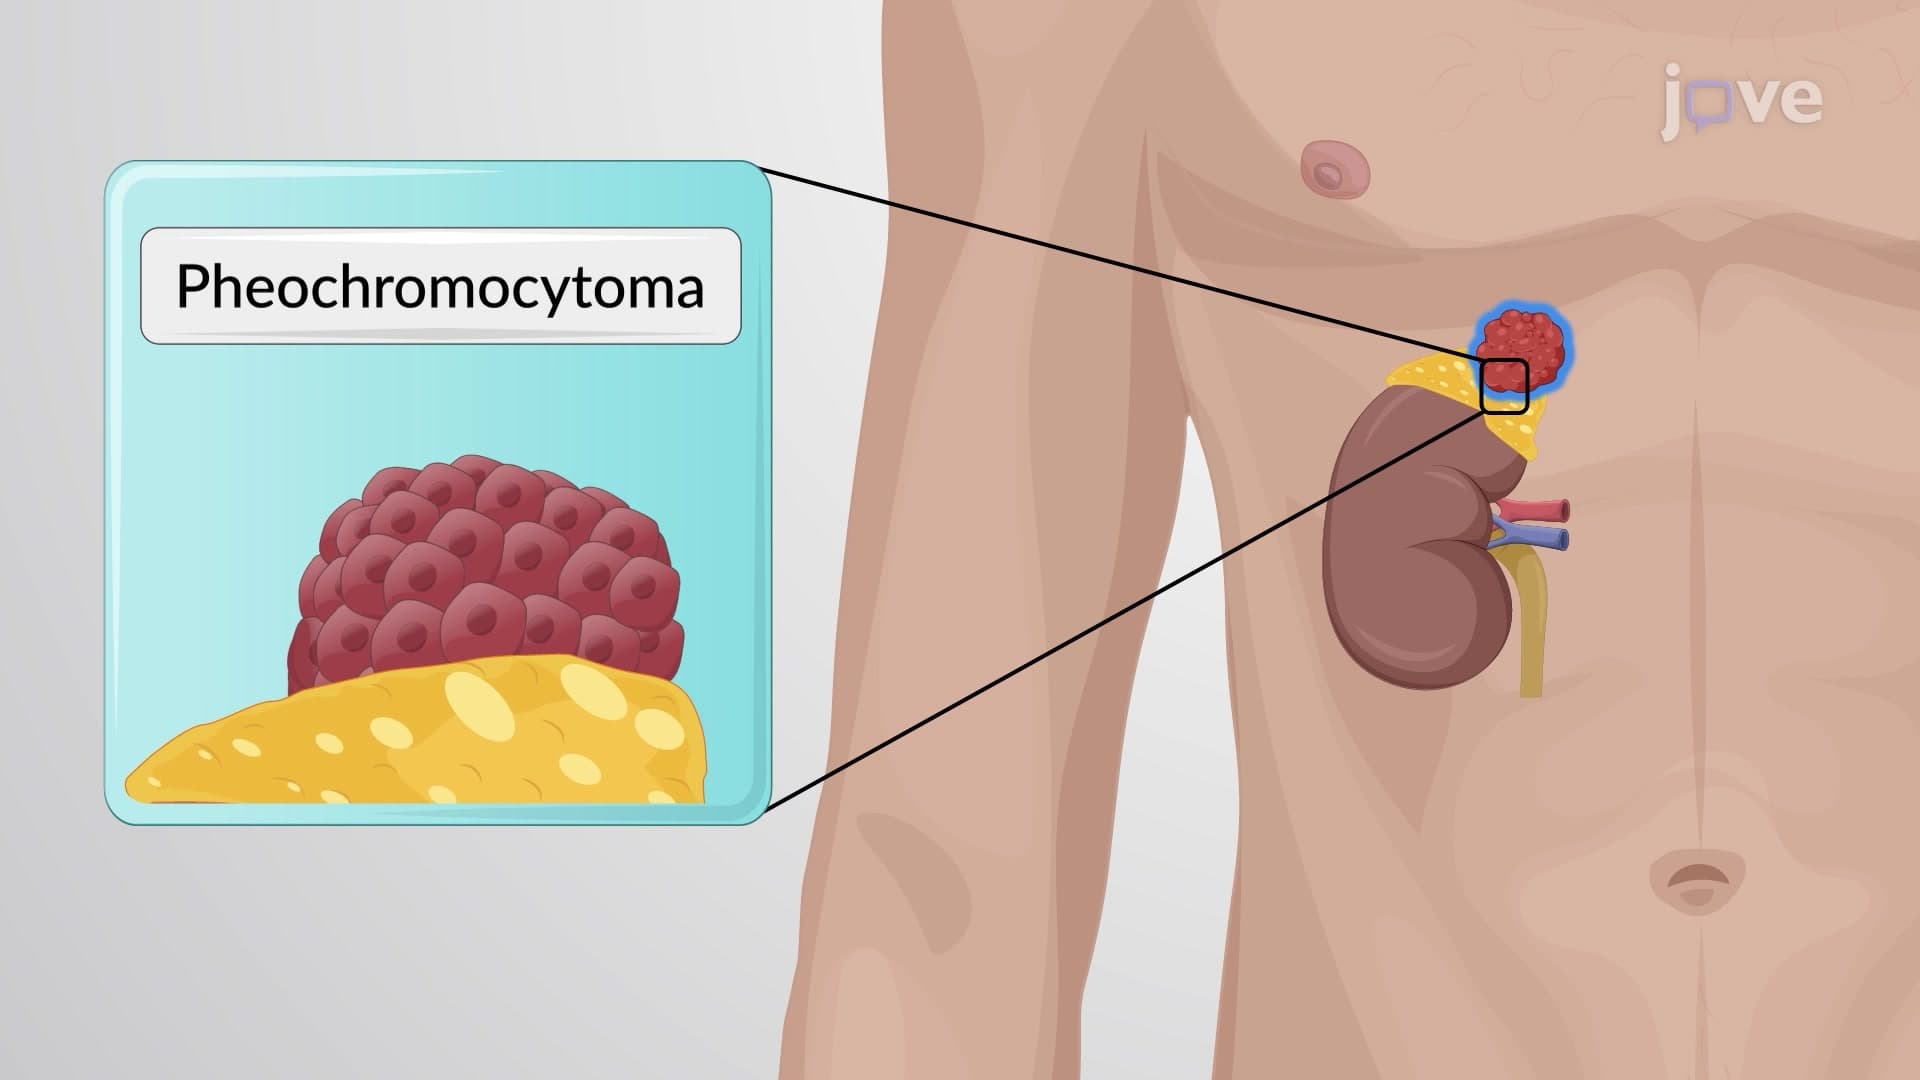
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 01:17
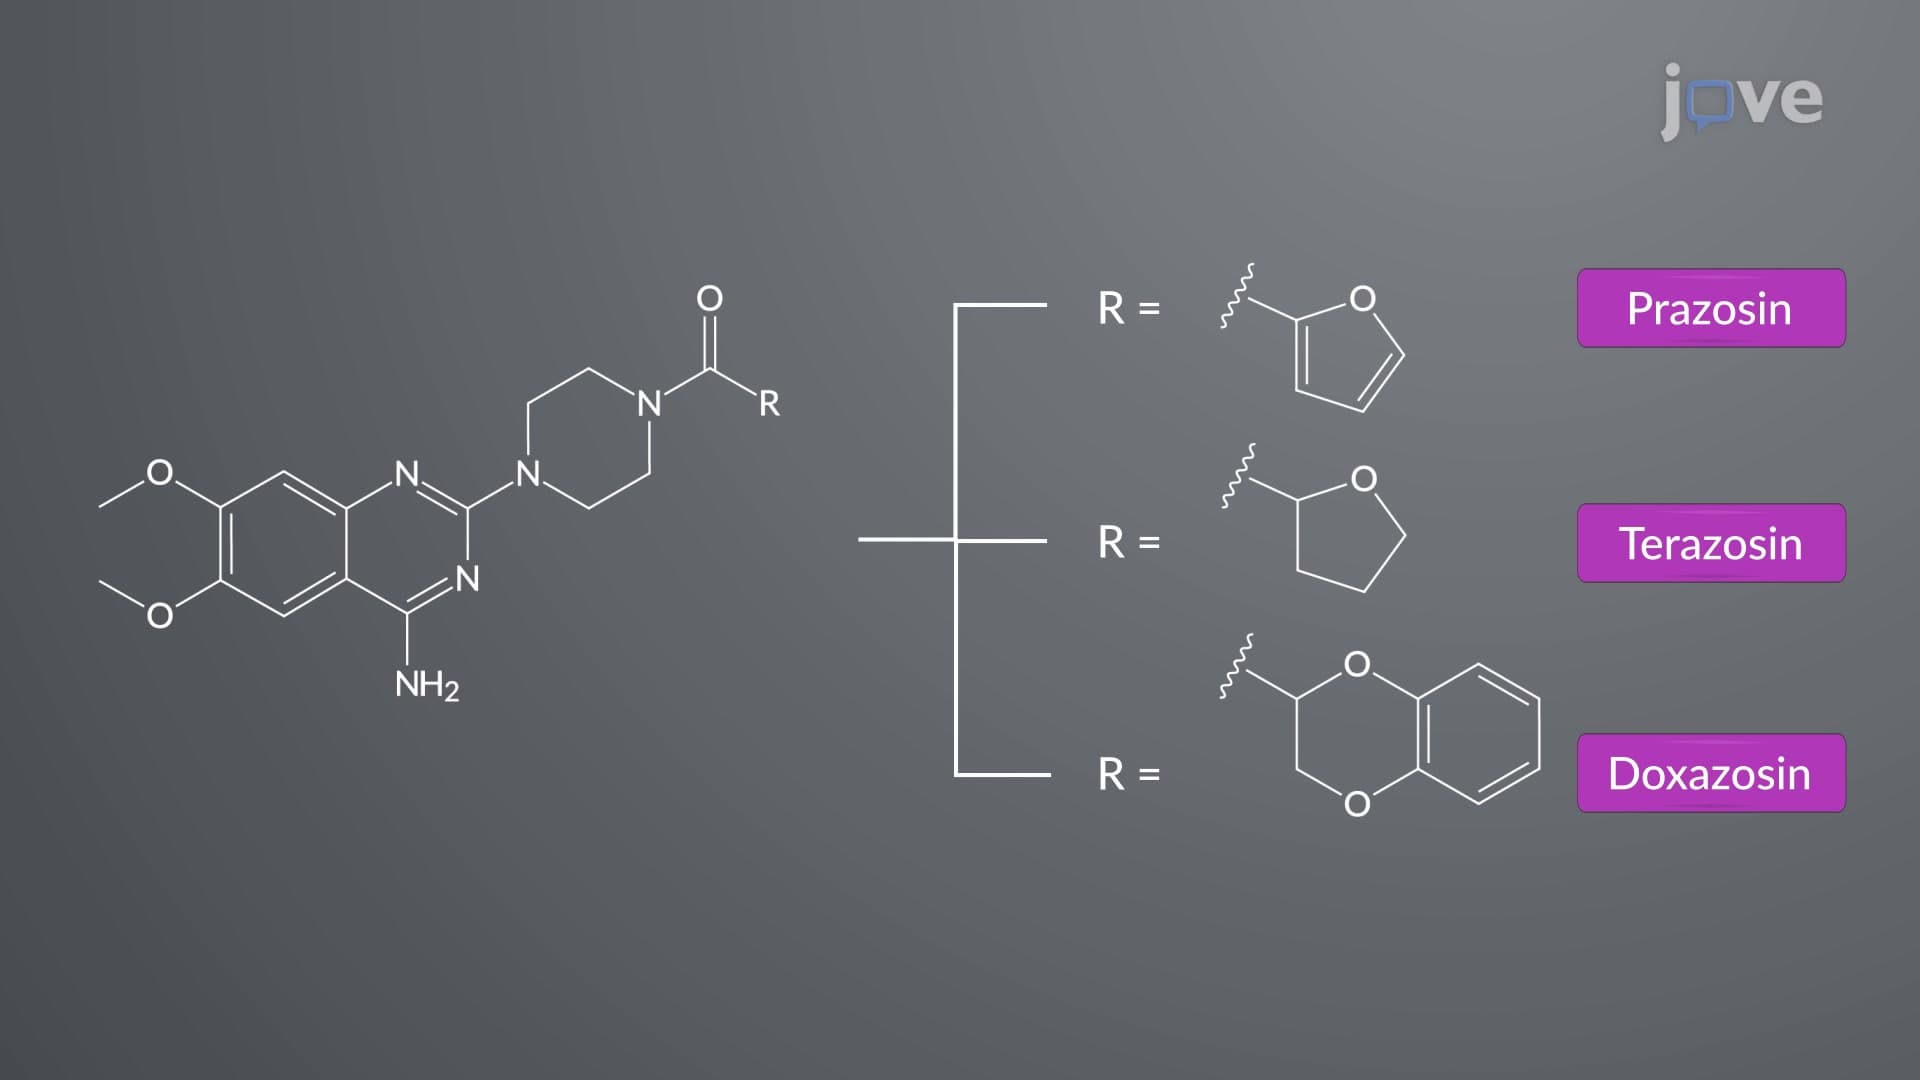
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme (ECE). Of...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System