Related Experiment Video
Updated: May 23, 2026
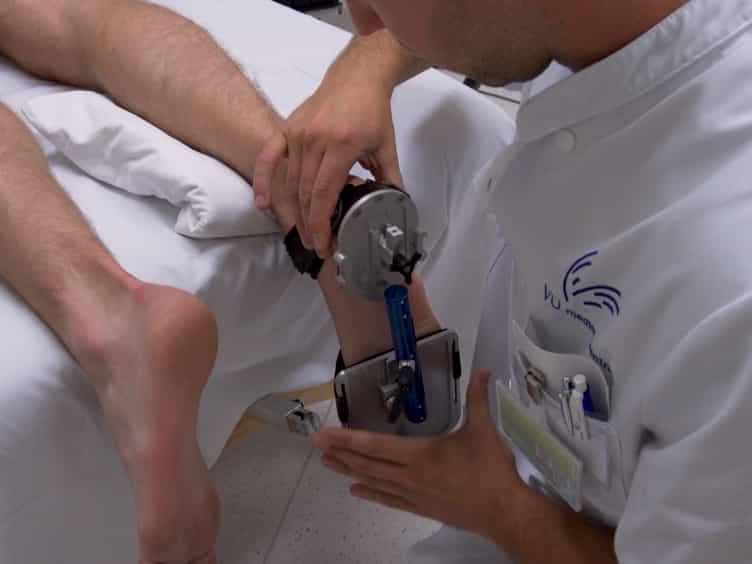
3D Ultrasound Imaging: Fast and Cost-effective Morphometry of Musculoskeletal Tissue
Published on: November 27, 2017
The association between body mass index, processes of care, and outcomes from mechanical ventilation: a prospective
James M O'Brien1, Gary S Philips, Naeem A Ali
1Division of Pulmonary, Allergy, Critical Care and Sleep Medicine, Center for Critical Care, The Ohio State University Medical Center, College of Public Health, The Ohio State University, Columbus, OH, USA. James.OBrien@osumc.edu

Objective:
To determine the association between excess weight and processes of care and outcomes for critically ill adults.
Design:
Prospective cohort study.
Setting:
Three medical intensive care units at two hospitals.
Patients:
Five hundred eighty mechanically ventilated adult patients admitted between February 1, 2006 and January 31, 2008.
Interventions:
None.
Measurements And Main Results:
After adjusting weight based on the recorded fluid balance before enrollment, 21.9% of subjects were categorized into different body mass index categories than without this adjustment. We used a competing risk analysis with events of interest considered death during hospitalization and successful liberation from mechanical ventilation. We found no statistically significant difference between body mass index categories (<25 kg/m² vs. 25 to <30 kg/m² vs. ≥30 kg/m²) in the competing risks analyses when the results were unadjusted or adjusted for severity of illness and comorbidities. When the analyses were adjusted for the use of continuous infusions of opioids and/or sedatives and ventilator parameters (tidal volume per ideal body weight, positive end-expiratory pressure, and airway pressure), subjects with an overweight fluid-balance-adjusted body mass index had significantly lower hazard ratios for dying while hospitalized (adjusted hazard ratio 0.68 [95% confidence interval 0.47-0.99], p=.044), and those with an obese fluid-adjusted body mass index had significantly higher hazard ratios for successful extubation (adjusted hazard ratio 1.53 [95% confidence interval 1.14-2.06], p=.005). An analysis of longer-term mortality found lower adjusted hazard ratios for subjects with overweight (adjusted hazard ratio 0.74 [95% confidence interval 0.56-0.96]) and obese (adjusted hazard ratio 0.74 [95% confidence interval 0.59-0.94]) fluid-balance-adjusted body mass indices.
Conclusions:
Processes of provided care may affect the observed association between excess weight and outcomes for critically ill adults and should be considered when making inferences about observed results. It is unknown if disparities in processes of care are due to clinically justified reasons for variation, bias against heavier patients, or other reasons.

Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History