Related Experiment Video
Updated: May 23, 2026
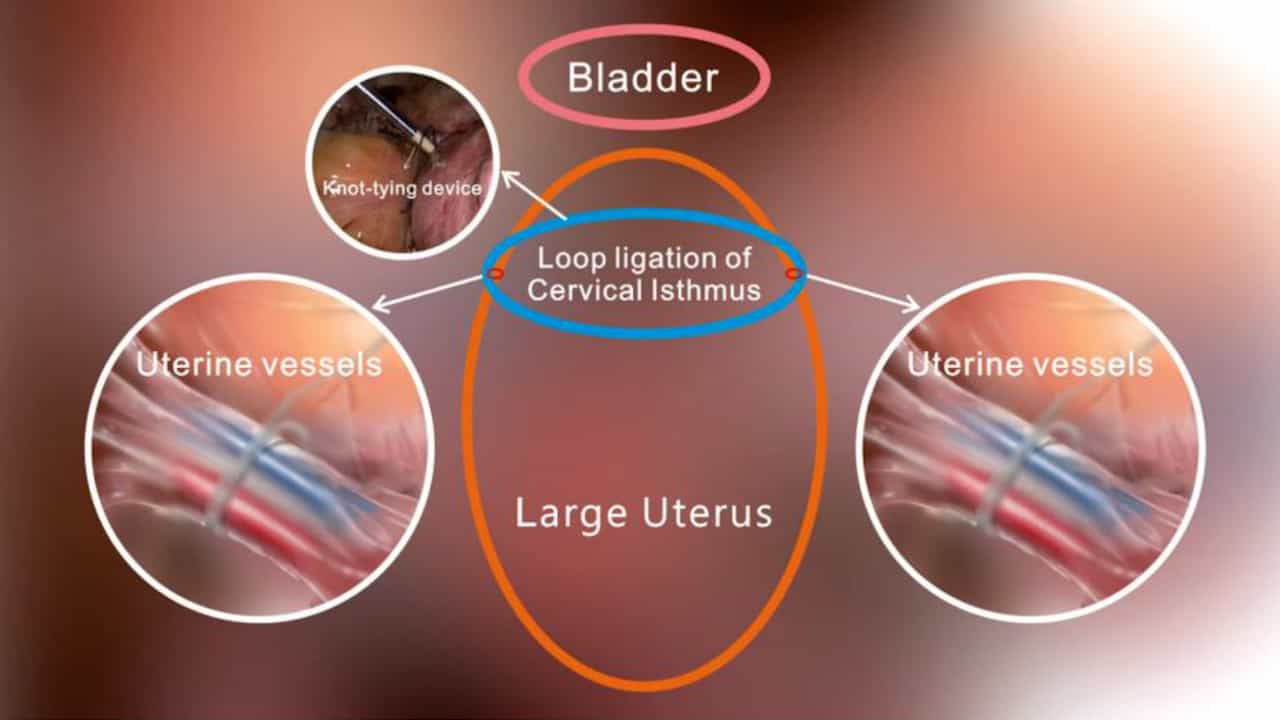

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Postpartum hemorrhage: when uterotonics and sutures fail
Andra H James1, Claire McLintock, Evelyn Lockhart
1Department of Obstetrics & Gynecology, Duke University Medical Center, Durham, North Carolina 27710, USA. andra.james@duke.edu

Systemic bleeding at the time of postpartum hemorrhage (PPH) is usually the result of coagulopathy that has developed acutely as a result of massive hemorrhage after uterotonics and sutures have failed. Occasionally, the patient has a preexisting coagulopathy, but more often, coagulopathy arises acutely as the result of massive hemorrhage, which is usually related to obstetrical and less often surgical bleeding. Despite being able to identify risk factors for PPH in the antenatal and intrapartum period, the majority of women who ultimately develop PPH do not have any such factors and every pregnancy is at risk. The coagulopathy associated with massive PPH may be due to hemodilution, failure of liver synthetic function as occurs with acute liver failure of pregnancy, or disseminated intravascular coagulation (DIC). There are no data from clinical trials to help guide management of transfusion in PPH, although the management of blood component therapy in severe PPH is similar to that in other massive hemorrhage. Standard practice is to replace fibrinogen to maintain a level of ≥ 100 mg/dL, yet recent evidence suggests that the level of fibrinogen needed to prevent PPH is at least 400 mg/dL. Recombinant activated factor VIIa (rFVIIa) has been used in the management of severe PPH unresponsive to blood component therapy. Coagulation laboratory evaluation may be useful in guiding hemostatic management during massive PPH, but for the results to be useful, they must be rapidly available and provide information that would not be available from clinical assessment alone. The hematologist or hemostasis expert has the opportunity to make the difference between life and death for the patient experiencing massive PPH.
Systemic bleeding at the time of postpartum hemorrhage (PPH) is usually the result of coagulopathy that has developed acutely as a result of massive hemorrhage after uterotonics and sutures have failed. Occasionally, the patient has a preexisting coagulopathy, but more often, coagulopathy arises acutely as the result of massive hemorrhage, which is usually related to obstetrical and less often surgical bleeding. Despite being able to identify risk factors for PPH in the antenatal and intrapartum period, the majority of women who ultimately develop PPH do not have any such factors and every pregnancy is at risk. The coagulopathy associated with massive PPH may be due to hemodilution, failure of liver synthetic function as occurs with acute liver failure of pregnancy, or disseminated intravascular coagulation (DIC). There are no data from clinical trials to help guide management of transfusion in PPH, although the management of blood component therapy in severe PPH is similar to that in other massive hemorrhage. Standard practice is to replace fibrinogen to maintain a level of ≥ 100 mg/dL, yet recent evidence suggests that the level of fibrinogen needed to prevent PPH is at least 400 mg/dL. Recombinant activated factor VIIa (rFVIIa) has been used in the management of severe PPH unresponsive to blood component therapy. Coagulation laboratory evaluation may be useful in guiding hemostatic management during massive PPH, but for the results to be useful, they must be rapidly available and provide information that would not be available from clinical assessment alone. The hematologist or hemostasis expert has the opportunity to make the difference between life and death for the patient experiencing massive PPH.

Related Concept Videos
 01:22
Aneurysm IV: Nursing Management
 01:26
Aneurysm III: Interprofessional Care