Related Experiment Video
Updated: May 23, 2026
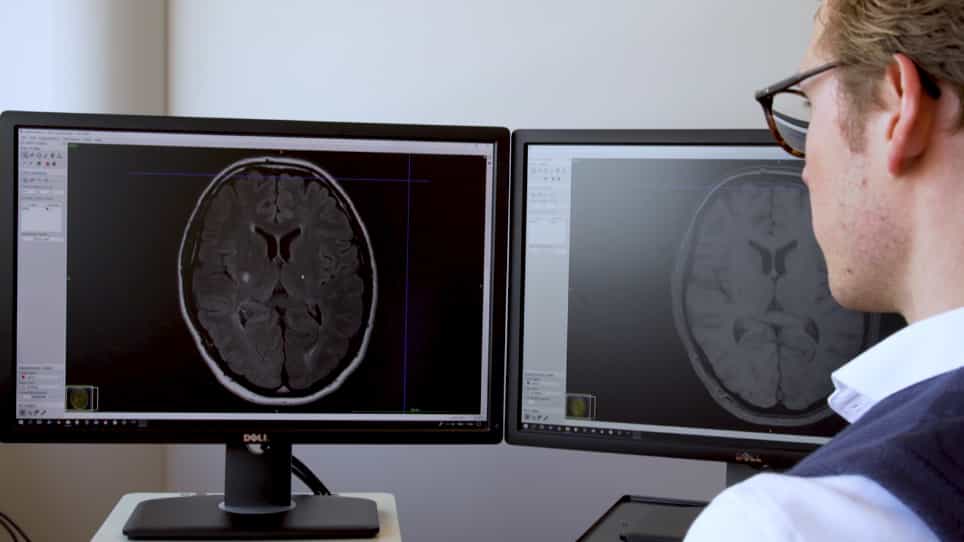

Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
The evolution of the cerebral blood volume abnormality in patients with ischemic stroke: a CT perfusion study
Christopher D d'Esterre1, Richard I Aviv, Ting Yim Lee
1Lawson Health Research Institute, London, Ontario, Canada.

Background:
Accurate identification of the acute infarct core abnormality is important for guiding acute stroke treatment. Abnormality volumes from diffusion-weighted MRI (DWI) and CT perfusion (CTP)-cerebral blood volume (CBV) are highly correlated. DWI lesions have been shown to be reversible at 24 h.
Purpose:
To examine the temporal profile of the CT perfusion (CTP)-derived CBV abnormality out to 7 days post ischemic stroke.
Material And Methods:
Twenty-six patients were included. Group A (n = 13) underwent a non-contrast CT (NCCT), CTP/CT angiography (CTA) within 6 h of stroke onset, CTP/CTA at 24 h, and CTP/NCCT at 5-7 days post stroke. Group B (n = 13) underwent a NCCT, CTP/CTA within 6 h of stroke onset, and NCCT at 5-7 days. Recanalization status was established in all patients. For both groups, infarct volumes were traced on 5-7 day NCCT images and superimposed onto all CTP-CBV functional maps to determine CBV. Group B (n = 13) admission images were used to define CBV infarct thresholds for gray and white matter. CBV-lesion over-estimation was determined for Group A using the thresholds from Group B.
Results:
CBV (mL·100g(- 1); mean ± stdev) for gray/white matter, within confirmed infarcted regions (CBV(I)) at admission, 24 h, and 5-7 days were 1.82 ± 0.56, 1.56 ± 0.42, 1.75 ± 0.31, and 1.38 ± 0.65, 1.13 ± 0.31, 1.32 ± 0.44, respectively, when averaged over all patients (P > 0.05). Four patients had tissue time-density curves from ischemic lesions (TDC(i)) with an incomplete contrast medium wash-out phase (truncation) at admission and/or 24 h. Compared to admission, gray matter CBV(I) was higher at 5-7 days for patients with TDC(i) truncation (P < 0.05). There were no significant CBV(I) increases for the eight patients without truncation (P > 0.05). Over-estimation of acute CBV lesion was present in 3/4 (75%) and 1/9 (11%) of patients with/without TDC(i) truncation, respectively.
Conclusion:
CTP-derived CBV lesion reversal is associated with TDC(i) truncation during the acute stroke phase.
Related Concept Videos
 01:15
Ischemic Stroke ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology
 01:29
Hemorrhagic Stroke ll: Pathophysiology