Related Experiment Video
Updated: May 23, 2026


Determination of Cardiac Output in a Porcine Model for Ex Vivo Pulmonary Perfusion
Published on: June 28, 2024
Effects of one-lung ventilation on thermodilution-derived assessment of cardiac output
1Department of Anaesthesiology, Center of Anaesthesiology and Intensive Care Medicine, Cardiovascular Research Center, University Medical Center Hamburg-Eppendorf, Martinistrasse 52, D-20246 Hamburg, Germany.

Background:
Cardiac output (CO) monitoring can be useful in high-risk patients during one-lung ventilation (OLV), but it is unclear whether thermodilution-derived CO monitoring is valid during OLV. Therefore, we compared pulmonary artery (CO(PATD)) and transcardiopulmonary thermodilution (CO(TPTD)) with an experimental reference in a porcine model.
Methods:
CO(PATD) and CO(TPTD) were measured in 23 pigs during double-lung ventilation (DLV) and 15 min after the onset of OLV, during conditions of normovolaemia and after haemorrhage. An ultrasonic flow probe placed around the pulmonary artery (CO(PAFP)) was used for reference.
Results:
The range of CO in these experiments was 1.5-3 litre min(-1). Normovolaemia: during DLV and conditions of normovolaemia, the mean (95% limits of agreement) bias for CO(PATD) compared with CO(PAFP) was -0.05 (-0.92 and 0.83) litre min(-1), and 0.58 (-0.40 and 1.55) litre min(-1) for CO(TPTD). During OLV, the bias for CO(PATD) remained unchanged at 0.08 (-0.51 and 0.66) litre min(-1), P=0.15, and the bias for CO(TPTD) increased significantly to 0.85 (0.05 and 1.64) litre min(-1), P=0.047. Hypovolaemia: during DLV, the bias for CO(PATD) compared with CO(PAFP) was 0.22 (-0.20 and 0.66) litre min(-1) and for CO(TPTD) was 0.60 (0.12 and 1.10) litre min(-1). There was no significant change of bias during OLV for CO(PATD) [0.30 (-0.10 and 0.70) (litre min(-1)), P=0.25] or bias CO(TPTD) [0.72 (0.21 and 1.22) (litre min(-1)), P=0.14]. Trending ability during OLV, quantified by the mean of angles θ, showed good values for both CO(PATD) (θ=11.2°) and CO(TPTD) (θ=1.3°).
Conclusions:
CO(TPTD) is, to some extent, affected by OLV, whereas CO(PATD) is unchanged. Nonetheless, both methods provide an acceptable estimation of CO and particularly of relative changes of CO during OLV.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 08:44
Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
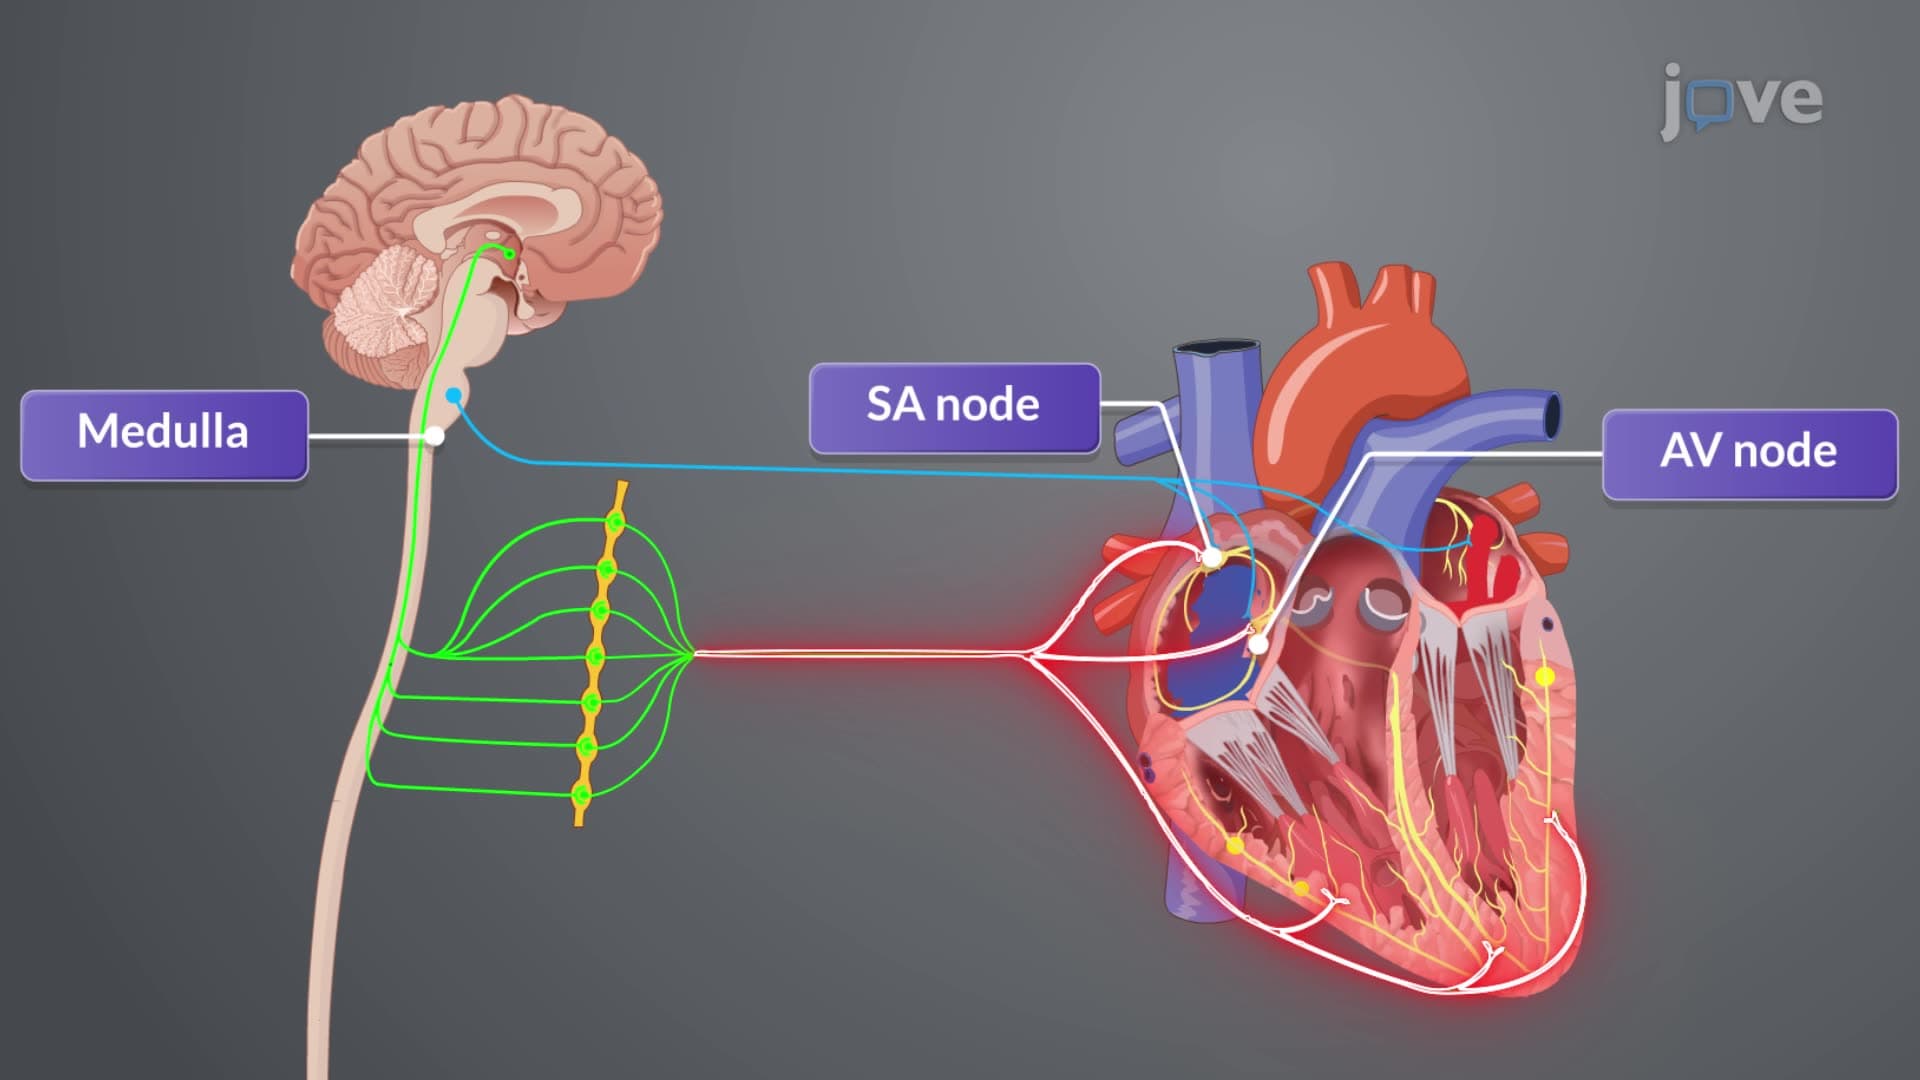
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: