Related Experiment Video
Updated: May 23, 2026

Management of the Uncinate Process in No-Touch Laparoscopic Pancreaticoduodenectomy
Published on: May 5, 2023
Preoperative pancreas CT/MRI characteristics predict fistula rate after pancreaticoduodenectomy
F Frozanpor1, L Loizou, C Ansorge
1Department of Clinical Science and Education, Karolinska Institutet, Stockholm, Sweden. farshad.frozanpor@ki.se

Insights
A large pancreatic remnant volume and narrow pancreatic duct increase pancreatic fistula risk after pancreaticoduodenectomy. Preoperative imaging can predict this complication.
Area of Science:
- Gastroenterology and Hepatology
- Surgical Oncology
- Radiology
Background:
- Pancreatic fistula (PF) is a major complication following pancreaticoduodenectomy (PD).
- Pancreatic remnant volume (PRV) was previously linked to PF risk after distal pancreatectomy.
- This study investigated PRV as a determinant of PF risk after PD.
Purpose of the Study:
- To evaluate the association between pancreatic remnant volume (PRV) and pancreatic duct width (PDW) with the risk of pancreatic fistula (PF) after pancreaticoduodenectomy (PD).
- To determine if preoperative imaging can predict PF formation.
Main Methods:
- Retrospective analysis of 182 patients undergoing PD between 2007 and 2010.
- Preoperative CT or MRI was used to measure PRV and PDW at the resection line.
- PF diagnosis based on ISGPF criteria.
Main Results:
- PF occurred in 20.3% of patients.
- A larger PRV (OR 3.71) and smaller PDW (OR 8.46) were significantly associated with increased PF risk in univariate analysis.
- These factors remained significant in multivariate analysis.
Conclusions:
- Increased PRV and decreased PDW are significant predictors of PF after PD.
- Preoperative CT and MRI are valuable tools for predicting PF risk before pancreaticoduodenectomy.
Background:
Pancreatic fistula (PF) is considered to be the main cause of morbidity after pancreaticoduodenectomy (PD). A recent study from our institution suggested the risk for pancreatic fistula after distal pancreatectomy to be closely related to the pancreatic remnant volume (PRV). The hypothesis was formulated that after PD the PRV is an important determinant of the risk for PF formation.
Method:
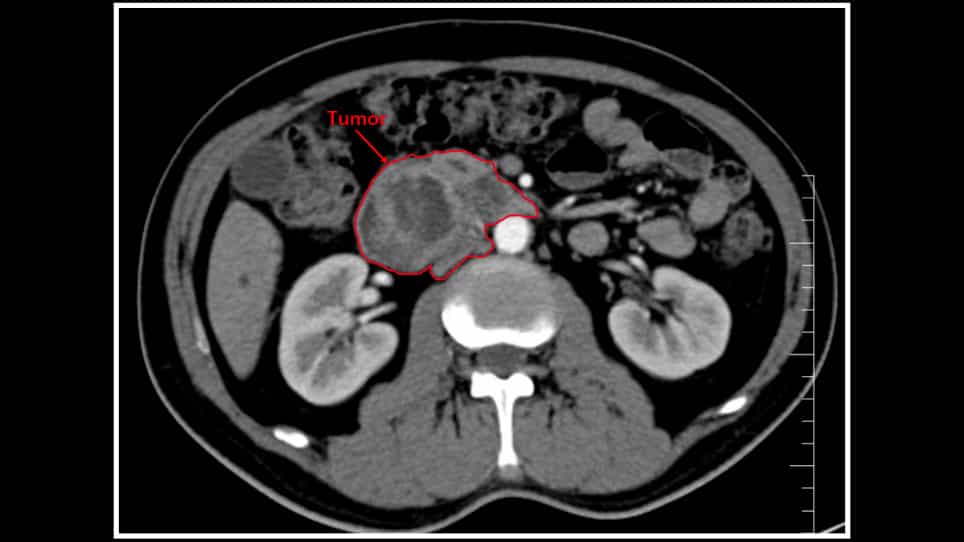
All patients undergoing PD between September 2007 and November 2010 at the Karolinska University Hospital Stockholm were included. Preoperative multidetector computed tomography (CT) or magnetic resonance imaging (MRI) was used to calculate the PRV and the pancreatic duct width (PDW) at the alleged resection line.
Results:
A total of 182 patients (median age 67 years) undergoing PD were included. The diagnosis was malignant in 144 patients (79.1 %) and benign in 38 (20.9 %). Pancreatic fistula defined according to the International Study Group on Pancreatic Fistula (ISGPF) criteria was diagnosed in 37 patients (20.3 %). The median PRV was 35.2 cm(3) and the median PDW was 3.9 mm. In a univariate analysis a large calculated volume of the pancreatic remnant increased the subsequent risk of PF (odds ratio [OR], 3.71; 95% confidence interval [95% CI], 1.58-8.71; P < 0.01), as did a small duct width (OR, 8.46; 95% CI, 3.11-23.04; P < 0.01). According to the multivariate analysis, the size of the pancreatic remnant and the width of the pancreatic duct maintained their impact on leakage risk.
Conclusions:
A large pancreatic volume and small pancreatic duct increase the risk of PF. Preoperative CT and/or MRI therefore are useful in predicting fistula formation before pancreaticoduodenectomy.