Related Experiment Video For Follow-up
Updated: May 23, 2026


Establishment and Evaluation of a Risk Prediction Model for Pathological Escalation of Gastric Low-Grade Intraepithelial Neoplasia
Published on: February 16, 2024
Follow-up of intestinal metaplasia in the stomach: When, how and why
Angelo Zullo1, Cesare Hassan, Adriana Romiti
1Angelo Zullo, Cesare Hassan, Michela Giusto, Carmine Guerriero, Roberto Lorenzetti, Salvatore MA Campo, Gastroenterology and Digestive Endoscopy, Nuovo Regina Margherita Hospital, 00153 Rome, Italy.

Abstract:
Gastric cancer remains the second most frequent cause of cancer-related mortality in the world. Screening programs in some Asian countries are impractical in the majority of other countries worldwide. Therefore, follow-up of precancerous lesions is advisable for secondary gastric cancer prevention. Intestinal metaplasia (IM) is recognized as a precancerous lesion for gastric cancer, increasing the risk by 6-fold. IM is highly prevalent in the general population, being detected in nearly 1 of every 4 patients undergoing upper endoscopy. The IM prevalence rate is significantly higher in patients with Helicobacter pylori (H. pylori) infection, in first-degree relatives of gastric cancer patients, in smokers and it increases with patient age. IM is the "breaking point" in the gastric carcinogenesis cascade and does not appear to regress following H. pylori eradication, although the cure of infection may slow its progression. Gastric cancer risk is higher in patients with incomplete-type IM, in those with both antral and gastric body involvement, and the risk significantly increases with IM extension over 20% of the gastric mucosa. Scheduled endoscopic control could be cost-effective in IM patients, depending on the yearly incidence of gastric cancer in IM patients, the stage of gastric cancer at diagnosis discovered at surveillance, and the cost of endoscopy. As a pragmatic behavior, yearly endoscopic control would appear justified in all IM patients with at least one of these conditions: (1) IM extension > 20%; (2) the presence of incomplete type IM; (3) first-degree relative of gastric cancer patients; and (4) smokers. In the remaining IM patients, a less intensive (2-3 years) could be proposed.
Related Concept Videos
 01:26
Gastritis II: Pathophysiology
 01:24
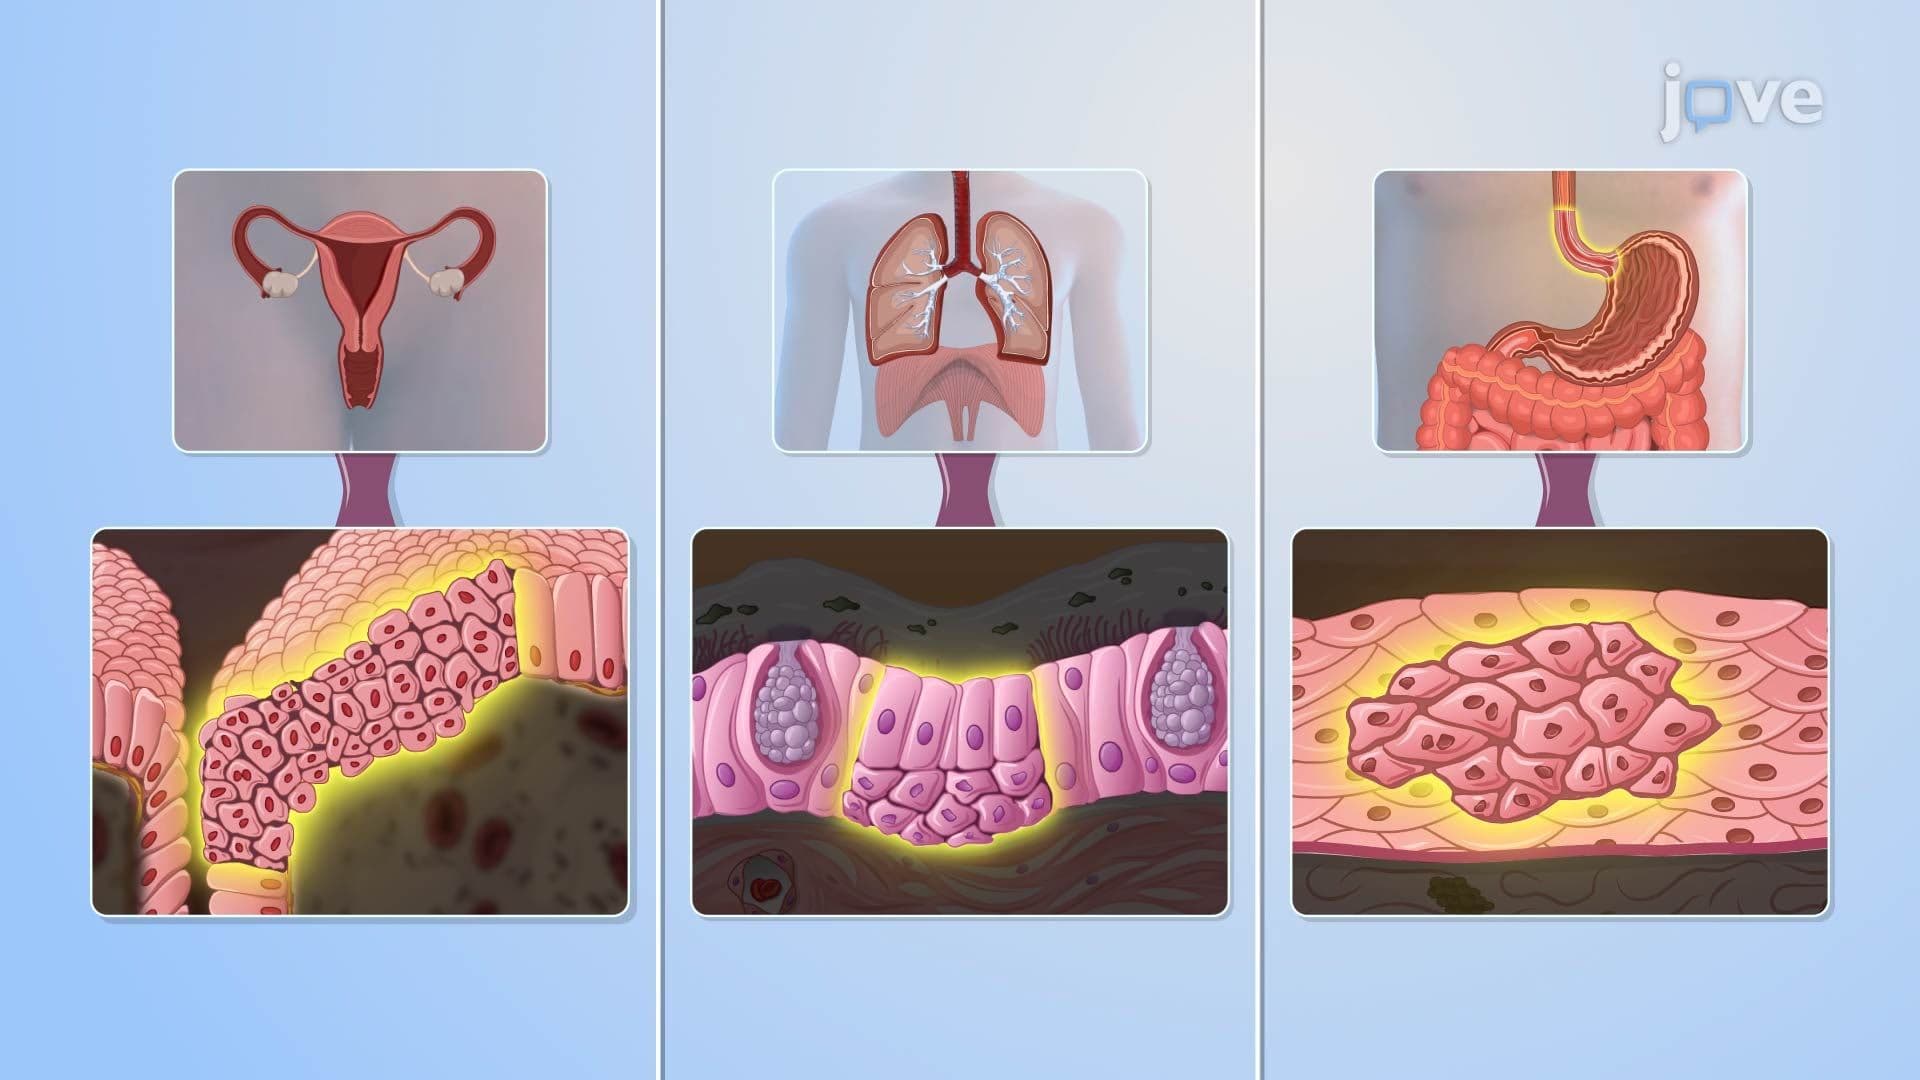
Cellular Adaptation IV: Dysplasia and Metaplasia
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...