Related Experiment Video
Updated: May 23, 2026
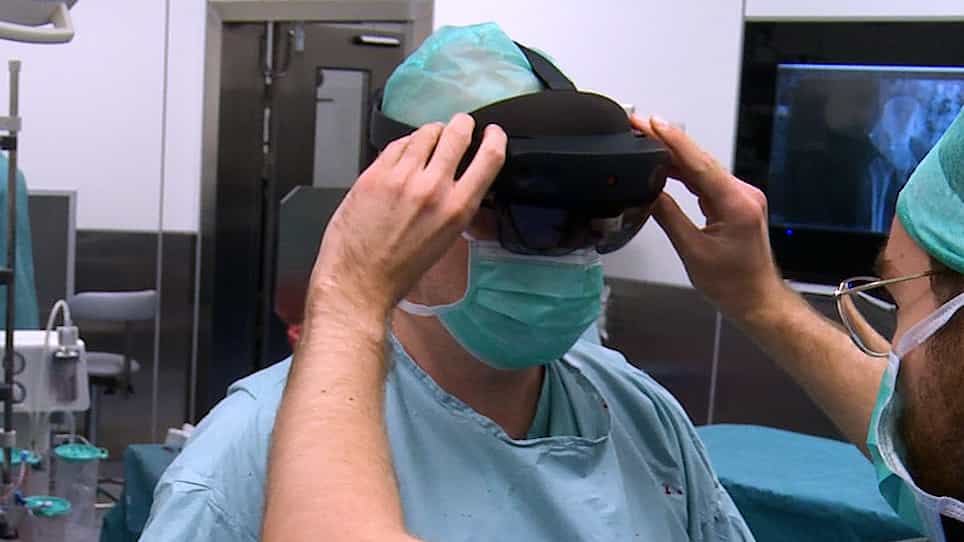

The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Total hip replacement in patients with history of illicit injecting drug use
Karl Wieser1, Patrick O Zingg, Michael Betz
1Orthopaedic Department, Balgrist University Hospital, University of Zurich, Forchstrasse 340, Zurich, Switzerland. karl.wieser@balgrist.ch

Insights
Total hip arthroplasty (THA) in patients with a history of drug use has high failure rates, especially with recent use. Documented abstinence of at least one year is crucial before THA.
Area of Science:
- Orthopedic Surgery
- Infectious Disease
- Addiction Medicine
Background:
- Patients with a history of illicit drug use present unique challenges for total hip arthroplasty (THA) due to increased infection risks.
- End-stage hip osteoarthritis in this population requires careful consideration of surgical intervention versus ongoing risks.
Purpose of the Study:
- To evaluate the survivorship and failure modes of THA in patients with a history of illicit drug use.
- To determine the impact of recent drug use on THA outcomes.
Main Methods:
- Retrospective survivorship analysis of 27 THA cases in patients with a history of illicit drug use.
- Follow-up included WOMAC scores, standardized interviews, clinical examinations (Harris Hip Score), radiological assessment, and blood tests.
- Endpoints defined as death, revision surgery, or loss to follow-up after a minimum of 2 years.
Main Results:
- Five- and 10-year implant survival rates were 61% and 52.3% for any reason, and 70.6% and 60.5% for septic reasons, respectively.
- Abstinence for less than 1 year prior to THA was significantly associated with higher recurrence and septic failure rates (p=0.001, p=0.023).
- Human immunodeficiency virus (HIV) serology did not impact implant failure rates.
Conclusions:
- The high failure rate observed necessitates careful counseling for patients and healthcare professionals regarding THA in individuals with a history of illicit drug use.
- Hair analysis for drugs to document at least one year of abstinence is recommended before indicating THA.
Background:
A history of illicit injecting drug use makes indication of total hip arthroplasty (THA) in patients with end stage hip osteoarthritis difficult, as the risk of infection with colonized strains is multiplied if the patient continues to inject or inhale illicit drugs.
Methods:
A retrospective survivorship analysis of a consecutive series of 27 THA in patients with a history of illicit drug use was performed. Follow-up evaluation consisted of (1) a WOMAC score, (2) a standardized interview including queries on drug habits and eventual additional medico-surgical treatments of the affected hip, (3) a clinical examination in order to complete a Harris Hip Score, (4) radiological examination and (5) blood tests (blood sedimentation rates and C-reactive protein). Defined endpoints were death, implant revised or awaiting revision for deep infection or any other reason and lost to follow-up or follow-up after at least 2 years.
Results:
Overall, 5- and 10-year implant survival rates with failure for any reason were 61 % (CI: 41;81) and 52.3 % (CI: 29;76) and for septic reasons 70.6 % (CI: 52;89) and 60.5 % (CI: 36;85), respectively. Even if at the time of THA all patients and respective health care professionals confirmed abstinence of illicit injecting drug use, five patients reported occasional use. Declared abstinence of less than 1 year before THA was associated with higher recurrence rates (p = 0.001) and both with higher septic failure rates (p = 0.023, p = 0.061). Positive serology for human deficiency virus did not increase implant failure rates.
Conclusion:
We use this unacceptable high failure rate as evidence when counseling patients and their health care professionals about the appropriate treatment of osteoarthritis in patients with a history of illicit drug use. Furthermore, we support the request of hair analysis for drugs documenting abstinence of at least 1 year before indicating THA.
Related Concept Videos
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:30
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis