Related Experiment Video
Updated: May 23, 2026
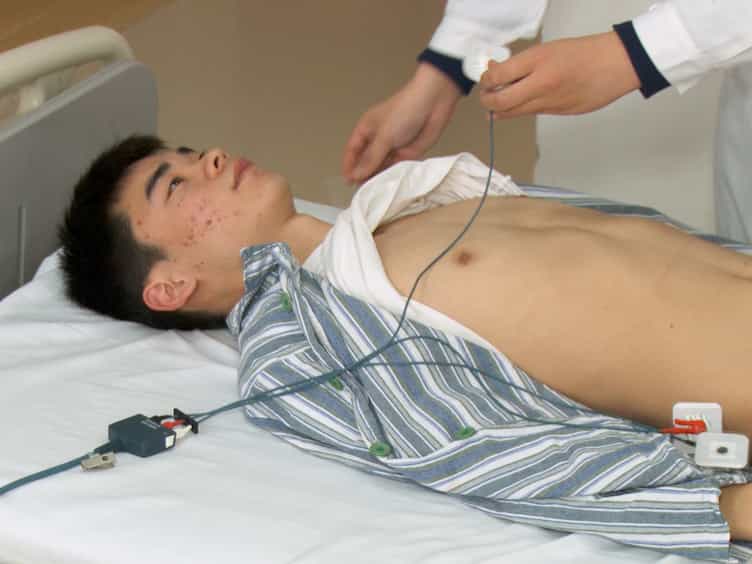

Measuring the Carotid to Femoral Pulse Wave Velocity (Cf-PWV) to Evaluate Arterial Stiffness
Published on: May 3, 2018
RV dysfunction in pulmonary hypertension is independently related to pulmonary artery stiffness
Gerin R Stevens1, Ana Garcia-Alvarez, Sheila Sahni
1Montefiore-Einstein Center for Heart and Vascular Care, Albert Einstein College of Medicine, Bronx, New York, New York, USA. gstevens@montefiore.org

Objectives:
This study investigated whether right ventricular (RV) adaptation to chronic pressure overload is associated with pulmonary artery (PA) stiffness beyond the degree of severity of pulmonary hypertension (PH).
Background:
Increased PA stiffness has been associated with reduced survival in PH. The mechanisms for this association remain unclear.
Methods:
Right heart catheterization and cardiac magnetic resonance were performed within 1 week in 124 patients with known or suspected chronic PH. Pulmonary vascular resistance index (PVRI) and PA pressures were quantified from right heart catheterization. Cardiac magnetic resonance included standard biventricular cine sequences and main PA flow quantification with phase-contrast imaging. Indexes of PA stiffness (elasticity, distensibility, capacitance, stiffness index beta, and pulse pressure) were quantified combining right heart catheterization and cardiac magnetic resonance data. RV performance and adaptation were measured by RV ejection fraction, right ventricular mass index (RVMI), RV end-systolic volume index, and right ventricular stroke work index (RVSWI).
Results:
All indexes of PA stiffness were significantly correlated with measures of RV performance (Spearman rho coefficients ranging from -0.20 to 0.61, p < 0.05). Using multivariate regression analysis, PA elasticity, distensibility, and index beta were independently associated with all measures of RV performance after adjusting PVRI (p ≤ 0.024). PA capacitance was independently associated with RV ejection fraction, RVMI, and RVSWI (p < 0.05), whereas PA pulse pressure was associated with RVMI and RVSWI (p ≤ 0.027). Compared with PVRI, PA elasticity, distensibility, capacitance, and index beta explained 15% to 68% of the variability in RV ejection fraction, RVMI, and RV end-systolic volume index. Relative contributions of PA stiffness for RVSWI were 1.2× to 18.0× higher than those of PVRI.
Conclusions:
PA stiffness is independently associated with the degree of RV dysfunction, dilation, and hypertrophy in PH. RV adaptation to chronic pressure overload is related not only to the levels of vascular resistance (steady afterload), but also to PA stiffness (pulsatile load).

Related Concept Videos
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:20
Vascular Resistance
The primary determinants of vascular resistance are vessel diameter, blood viscosity, and vessel length. Among these, vessel diameter plays the most significant role due to the fourth power relationship described by...
 01:22
Mitral Stenosis I: Introduction
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 01:23
Rheumatic Heart Disease I: Introduction