Related Experiment Video
Updated: May 23, 2026
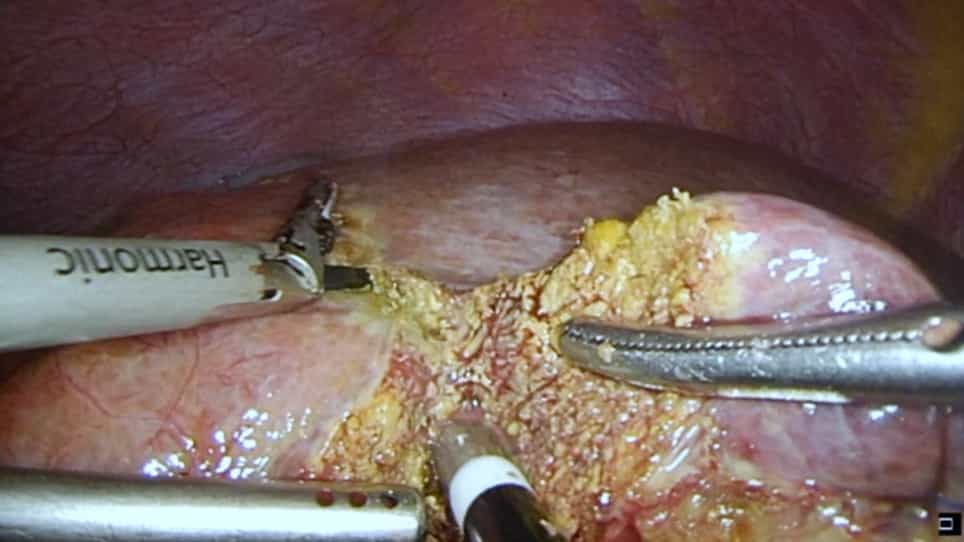

Application of Hemostatic Devices in Laparoscopic Hepatectomy
Published on: April 19, 2022
Prohemostatic interventions in liver surgery
Menno Stellingwerff1, Amarins Brandsma, Ton Lisman
1Department of Surgery, Section of Hepatobiliary Surgery and Liver Transplantation, University Medical Center Groningen, The University of Groningen, Groningen, The Netherlands.

Surgical procedures of the liver, such as partial liver resections and liver transplantation, are major types of abdominal surgery. Liver surgery can be associated with excessive intraoperative blood loss, not only because the liver is a highly vascularized organ, but also because it plays a central role in the hemostatic system. Intraoperative blood loss and transfusion of blood products have been shown to be negatively associated with postoperative outcome after liver surgery. Dysfunction of the liver is frequently accompanied with a dysfunctional hemostatic system. However, in general, there is a poor correlation between preoperative coagulation tests and the intraoperative bleeding risk in patients undergoing liver surgery. Strategies to avoid excessive blood loss in liver surgery have been an active field of research and include three different areas: surgical methods, anesthesiological methods, and pharmacological agents.Surgeons can minimize blood loss by clamping the hepatic vasculature, by using specific dissection devices, and by using topical hemostatic agents. Anesthesiologists play an important role in minimizing blood loss by avoiding intravascular fluid overload. Maintaining a low central venous pressure has shown to be very effective in reducing blood loss during partial liver resections. Prophylactic transfusion of blood products such as fresh frozen plasma (FFP) has not been shown to reduce intraoperative bleeding and even seems counterproductive as it results in an increase of the intravascular filling status, which may enhance the bleeding risk. In patients with liver cirrhosis, there is increasing evidence that factors such as portal hypertension and the hyperdynamic circulation play a more important role in the bleeding tendency than changes in the coagulation system. Therefore, intravenous fluid restriction rather than prophylactic administration of large volumes of blood products (i.e., FFP) is recommended in patients undergoing major liver surgery. Pharmacological agents such as antifibrinolytic drugs or recombinant factor VIIa may be indicated in selected individual patients, but these agents do not have a routine role in the management of patients undergoing liver surgery.
Surgical procedures of the liver, such as partial liver resections and liver transplantation, are major types of abdominal surgery. Liver surgery can be associated with excessive intraoperative blood loss, not only because the liver is a highly vascularized organ, but also because it plays a central role in the hemostatic system. Intraoperative blood loss and transfusion of blood products have been shown to be negatively associated with postoperative outcome after liver surgery. Dysfunction of the liver is frequently accompanied with a dysfunctional hemostatic system. However, in general, there is a poor correlation between preoperative coagulation tests and the intraoperative bleeding risk in patients undergoing liver surgery. Strategies to avoid excessive blood loss in liver surgery have been an active field of research and include three different areas: surgical methods, anesthesiological methods, and pharmacological agents.Surgeons can minimize blood loss by clamping the hepatic vasculature, by using specific dissection devices, and by using topical hemostatic agents. Anesthesiologists play an important role in minimizing blood loss by avoiding intravascular fluid overload. Maintaining a low central venous pressure has shown to be very effective in reducing blood loss during partial liver resections. Prophylactic transfusion of blood products such as fresh frozen plasma (FFP) has not been shown to reduce intraoperative bleeding and even seems counterproductive as it results in an increase of the intravascular filling status, which may enhance the bleeding risk. In patients with liver cirrhosis, there is increasing evidence that factors such as portal hypertension and the hyperdynamic circulation play a more important role in the bleeding tendency than changes in the coagulation system. Therefore, intravenous fluid restriction rather than prophylactic administration of large volumes of blood products (i.e., FFP) is recommended in patients undergoing major liver surgery. Pharmacological agents such as antifibrinolytic drugs or recombinant factor VIIa may be indicated in selected individual patients, but these agents do not have a routine role in the management of patients undergoing liver surgery.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:29
Venous Thrombosis III: Interprofessional Care