Related Experiment Video
Updated: May 23, 2026
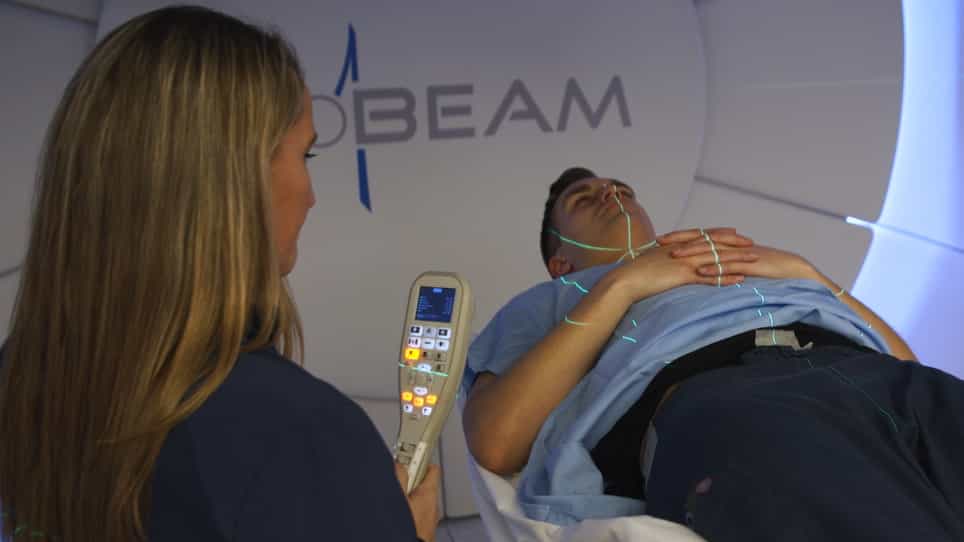

Proton Therapy Delivery and Its Clinical Application in Select Solid Tumor Malignancies
Published on: February 6, 2019
Intracystic bleomycin for cystic craniopharyngiomas in children
Yuan Fang1, Bo Wen Cai, Heng Zhang
1Department of Neurosurgery, West China Hospital, Sichuan University, Chengdu, China.

Insights
Limited research exists on intracystic bleomycin for pediatric cystic craniopharyngiomas. One small trial showed no significant difference in cyst reduction compared to other treatments, but found increased headache and vomiting with bleomycin. More high-quality studies are needed.
Area of Science:
- Pediatric neurosurgery
- Oncology
- Clinical research
Background:
- Craniopharyngiomas are common pediatric brain tumors affecting the hypothalamo-pituitary region.
- Cystic craniopharyngiomas are prevalent, and their optimal treatment remains debated.
- Intracystic bleomycin is explored to reduce treatment-related morbidity in children.
Purpose of the Study:
- To evaluate the benefits and harms of intracystic bleomycin versus alternative treatments for pediatric cystic craniopharyngiomas.
- To synthesize evidence from randomized controlled trials (RCTs), quasi-RCTs, and controlled clinical trials (CCTs).
Main Methods:
- Comprehensive literature search of major electronic databases (CENTRAL, MEDLINE/PubMed, EMBASE/Ovid) up to October 2010.
- Inclusion of RCTs, quasi-RCTs, or CCTs involving children (0-18 years) with cystic craniopharyngiomas.
- Independent data extraction and risk of bias assessment by two reviewers.
Main Results:
- No studies exclusively compared intracystic bleomycin with other treatments.
- One small RCT (7 children) compared intracystic bleomycin with intracystic 32P, showing no significant difference in cyst reduction.
- The 32P group had significantly fewer headaches and vomiting compared to the bleomycin group.
Conclusions:
- Insufficient high-quality evidence exists to recommend intracystic bleomycin for pediatric cystic craniopharyngiomas.
- The single available trial had a high risk of bias and limited power.
- Further high-quality RCTs are necessary to determine the efficacy and safety of intracystic bleomycin.
Background:
Craniopharyngiomas are the commonest benign histological tumours to involve the hypothalamo-pituitary region in childhood. Cystic craniopharyngiomas occur in more than 90% of tumours. The optimal treatment of cystic craniopharyngioma remains controversial. Radical resection is the treatment of choice in patients with favourable tumour localization. When the tumour localization is unfavourable, a gross-total or partial resection followed by radiotherapy is the main treatment option in adults. However, it presents risk of morbidity especially for children. Intracystic bleomycin has been utilized to potentially delay the use of radiotherapy or radical resection to decrease morbidity.
Objectives:
To determine the benefits and harms of intracystic bleomycin versus other treatments for cystic craniopharyngiomas in children.
Search Methods:
We searched the electronic databases of CENTRAL (The Cochrane Library 2010, Issue 4), MEDLINE/PubMed (from 1966 to Oct 2010), and EMBASE/Ovid (from 1980 to Oct 2010) with pre-specified terms. In addition, we searched reference lists of relevant articles and reviews, conference proceedings and ongoing trial databases.
Selection Criteria:
Randomised controlled trials (RCTs) quasi-randomised trials or controlled clinical trials (CCTs) comparing intracystic bleomycin and other treatments for cystic craniopharyngiomas in children (from birth to 18 years).
Data Collection And Analysis:
Two review authors independently performed the data extraction and the 'Risk of bias' assessment. We used risk ratio (RR) for binary data and mean difference (MD) for continuous data. We planned that if one of the treatment groups experienced no events and there was only one study available for the outcome, we would use the Fischer's exact test.
Main Results:
We could not identify any studies in which the only difference between the treatment groups was the use of intracystic bleomycin. We did identify a RCT comparing intracystic bleomycin with intracystic (32)P (n = 7 children). The trial had a high risk of bias. Survival could not be evaluated. There was no evidence of a significant difference in cyst reduction (MD = -0.15, 95% confidence interval (CI) -0.69 to 0.39, P= 0.59), neurological status (Fisher's exact P = 0.429), 3rd nerve paralysis (Fischer's exact P = 1.00), fever (RR = 2.92, 95% CI 0.73 to 11.70, P = 0.13) and total adverse effects (RR = 1.75, 95% CI 0.68 to 4.53, P = 0.25 ) between the treatment groups. There was a significant difference in favour of the (32)P group for the occurrence of headache and vomiting (Fischer's exact P = 0.029 for both outcomes).
Authors' Conclusions:
Since no RCTs, quasi-randomised trials or CCTs in which only the use of intracystic bleomycin differed between the treatment groups in the treatment of cystic craniopharyngiomas in children, no definitive conclusions could be made about the effects of intracystic bleomycin in these patients. Only one low-power RCT comparing intracystic bleomycin with intracystic (32)P treatment was available, but no definitive conclusions can be made about the effectiveness of these agents in children with cystic craniopharyngiomas. Based on the currently available evidence, we are not able to give recommendations for the use of intracystic bleomycin in the treatment of cystic craniopharyngiomas in children. High quality RCTs are needed.

