Related Experiment Video
Updated: May 22, 2026
07:22

A Standardized Procedure of Dressing Management for Toxic Epidermal Necrolysis
Published on: March 14, 2025
Gastrointestinal involvement in Stevens-Johnson syndrome: prompt recognition and successful treatment
International Journal of Colorectal Disease
|May 8, 2012

Abstract
No abstract available in PubMed .
Related Concept Videos
 01:24
Drugs for Peptic Ulcer Disease: Sucralfate as Mucosal Protective Agents
In the intricate landscape of the gastric lumen, excessive acid secretion disrupts the natural defense mechanisms, weakening the mucus-bicarbonate barrier. This vulnerability allows pepsin to infiltrate epithelial cells, digesting mucosal proteins and triggering erosion, leading to ulcer formation.
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
 01:23
Gastritis III: Clinical Manifestations and Management
The clinical manifestations of gastritis can vary depending on the cause and type of gastritis, but some common symptoms may include the following.
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
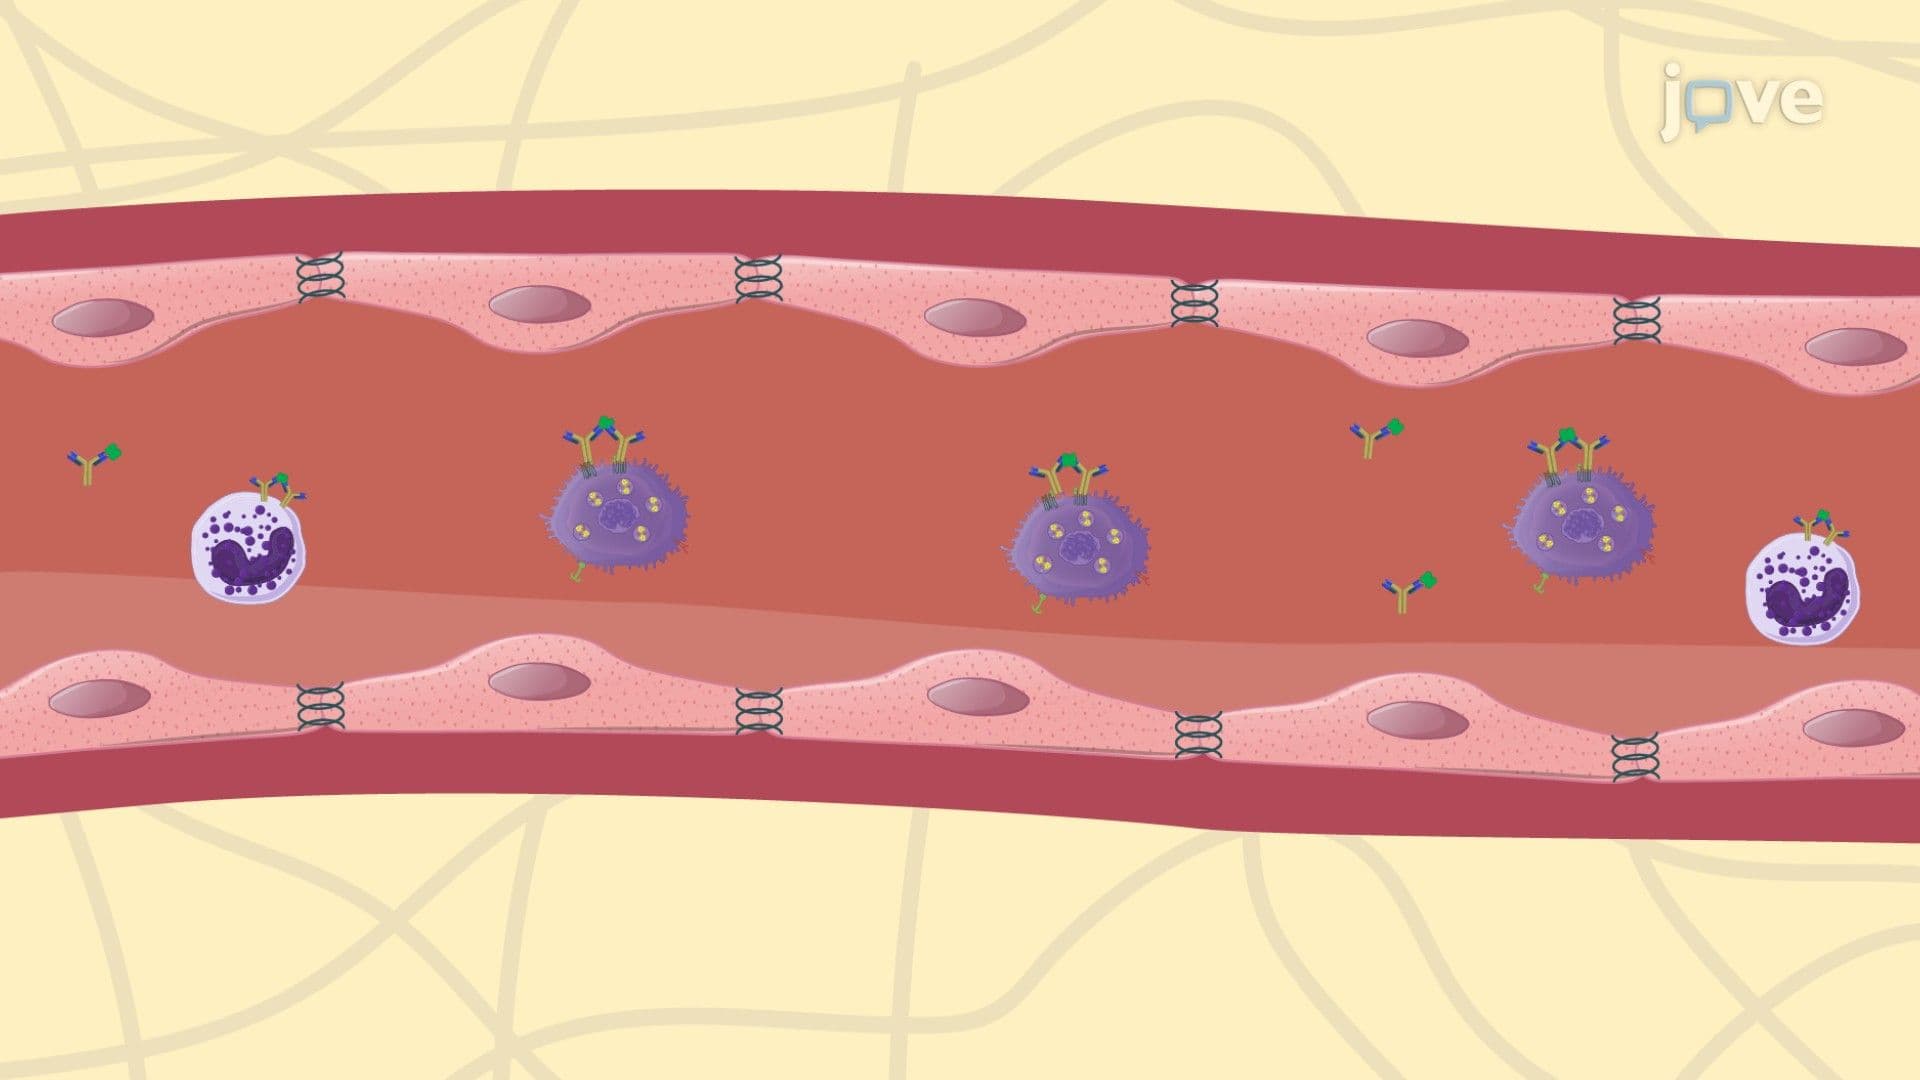 01:30
Drug Toxicity: Allergic Reactions
Drug-related allergies are immune-mediated responses triggered by the administration of pharmacological agents. These hypersensitivity reactions are classified based on the immune mechanisms involved. The four primary types—Type I, II, III, and IV—are mediated by different immunological pathways and exhibit distinct clinical manifestations.Type I Hypersensitivity/ IgE-Mediated Reactions: Immunoglobulin E (IgE) immediately mediates Type I hypersensitivity reactions. Upon initial exposure to a...
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
Duodenal UlcersDuodenal ulcers are the most common form of peptic ulcer disease, presenting with chronic, intermittent epigastric pain. Pain typically appears 2–3 hours after meals, especially when the stomach is empty, often waking patients at night. It is characteristically relieved by food or antacids (“pain–food–relief”). Some patients remain asymptomatic until complications like bleeding or perforation emerge, particularly with NSAID or anticoagulant use.Gastric UlcersGastric ulcers share...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical management and nursing care are crucial in treating Peptic Ulcer Disease (PUD). Here is an organized and enhanced overview of the surgical interventions and the associated nursing care for PUD:
Surgical Interventions for Peptic Ulcer Disease
Surgical Interventions for Peptic Ulcer Disease
 01:29
Staphylococcal Skin Infections
Staphylococcus aureus is a Gram-positive coccus that resides harmlessly on the skin and mucous membranes of healthy individuals. When the skin barrier is breached, it can shift from a commensal to an opportunistic pathogen. This transition is facilitated by surface adhesins, such as clumping factor B and S. aureus surface protein G (SasG), which bind to structural proteins, including loricrin and cytokeratin, in the damaged epidermis. Protein A, another key factor, binds the Fc region of...