Related Experiment Video
Updated: May 22, 2026

Sodium Taurocholate Induced Severe Acute Pancreatitis in C57BL/6 Mice
Published on: June 28, 2021
Differences between diffuse and focal autoimmune pancreatitis
Taku Tabata1, Terumi Kamisawa, Kensuke Takuma
1Department of Internal Medicine, Tokyo Metropolitan Komagome Hospital, 3-18-22 Honkomagome, Bunkyo-ku, Tokyo 113-8677, Japan.

Aim:
To investigate differences in clinical features between diffuse- and focal-type autoimmune pancreatitis (AIP).
Methods:
Based on radiological findings by computed tomography and/or magnetic resonance imaging, we divided 67 AIP patients into diffuse type (D type) and focal type (F type). We further divided F type into head type (H type) and body and/or tail type (B/T type) according to the location of enlargement. Finally, we classified the 67 AIP patients into three groups: D type, H type and B/T type. We compared the three types of AIP in terms of clinical, laboratory, radiological, functional and histological findings and clinical course.
Results:
There were 34 patients with D-type, 19 with H-type and 14 with B/T-type AIP. Although obstructive jaundice was frequently detected in D-type patients (88%) and H-type patients (68%), no B/T-type patients showed jaundice as an initial symptom (P < 0.001). There were no differences in frequency of abdominal pain, but acute pancreatitis was associated more frequently in B/T-type patients (36%) than in D-type patients (3%) (P = 0.017). Serum immunoglobulin G (IgG)4 levels were significantly higher in D-type patients (median 309 mg/dL) than in B/T-type patients (133.5 mg/dL) (P = 0.042). Serum amylase levels in B/T-type patients (median: 114 IU/L) were significantly greater than in H-type patients (72 IU/L) (P = 0.049). Lymphoplasmacytic sclerosing pancreatitis (LPSP) was histologically confirmed in 6 D-type, 7 H-type and 4 B/T-type patients; idiopathic duct-centric pancreatitis was observed in no patients. Marked fibrosis and abundant infiltration of CD20-positive B lymphocytes with few IgG4-positive plasma cells were detected in 2 B/T-type patients. Steroid therapy was effective in all 50 patients (31 D type, 13 H type and 6 B/T type). Although AIP relapsed during tapering or after stopping steroids in 3 D-type and 3 H-type patients, no patients relapsed in B/T type. During follow-up, radiological features of 6 B/T-type patients were not changed and 1 B/T-type patient improved naturally.
Conclusion:
Clinical features of H-type AIP were similar to those of D-type, but B/T-type differed from D and H types. B/T-type may involve diseases other than LPSP.

Related Concept Videos
 01:24
Chronic Pancreatitis I: Introduction
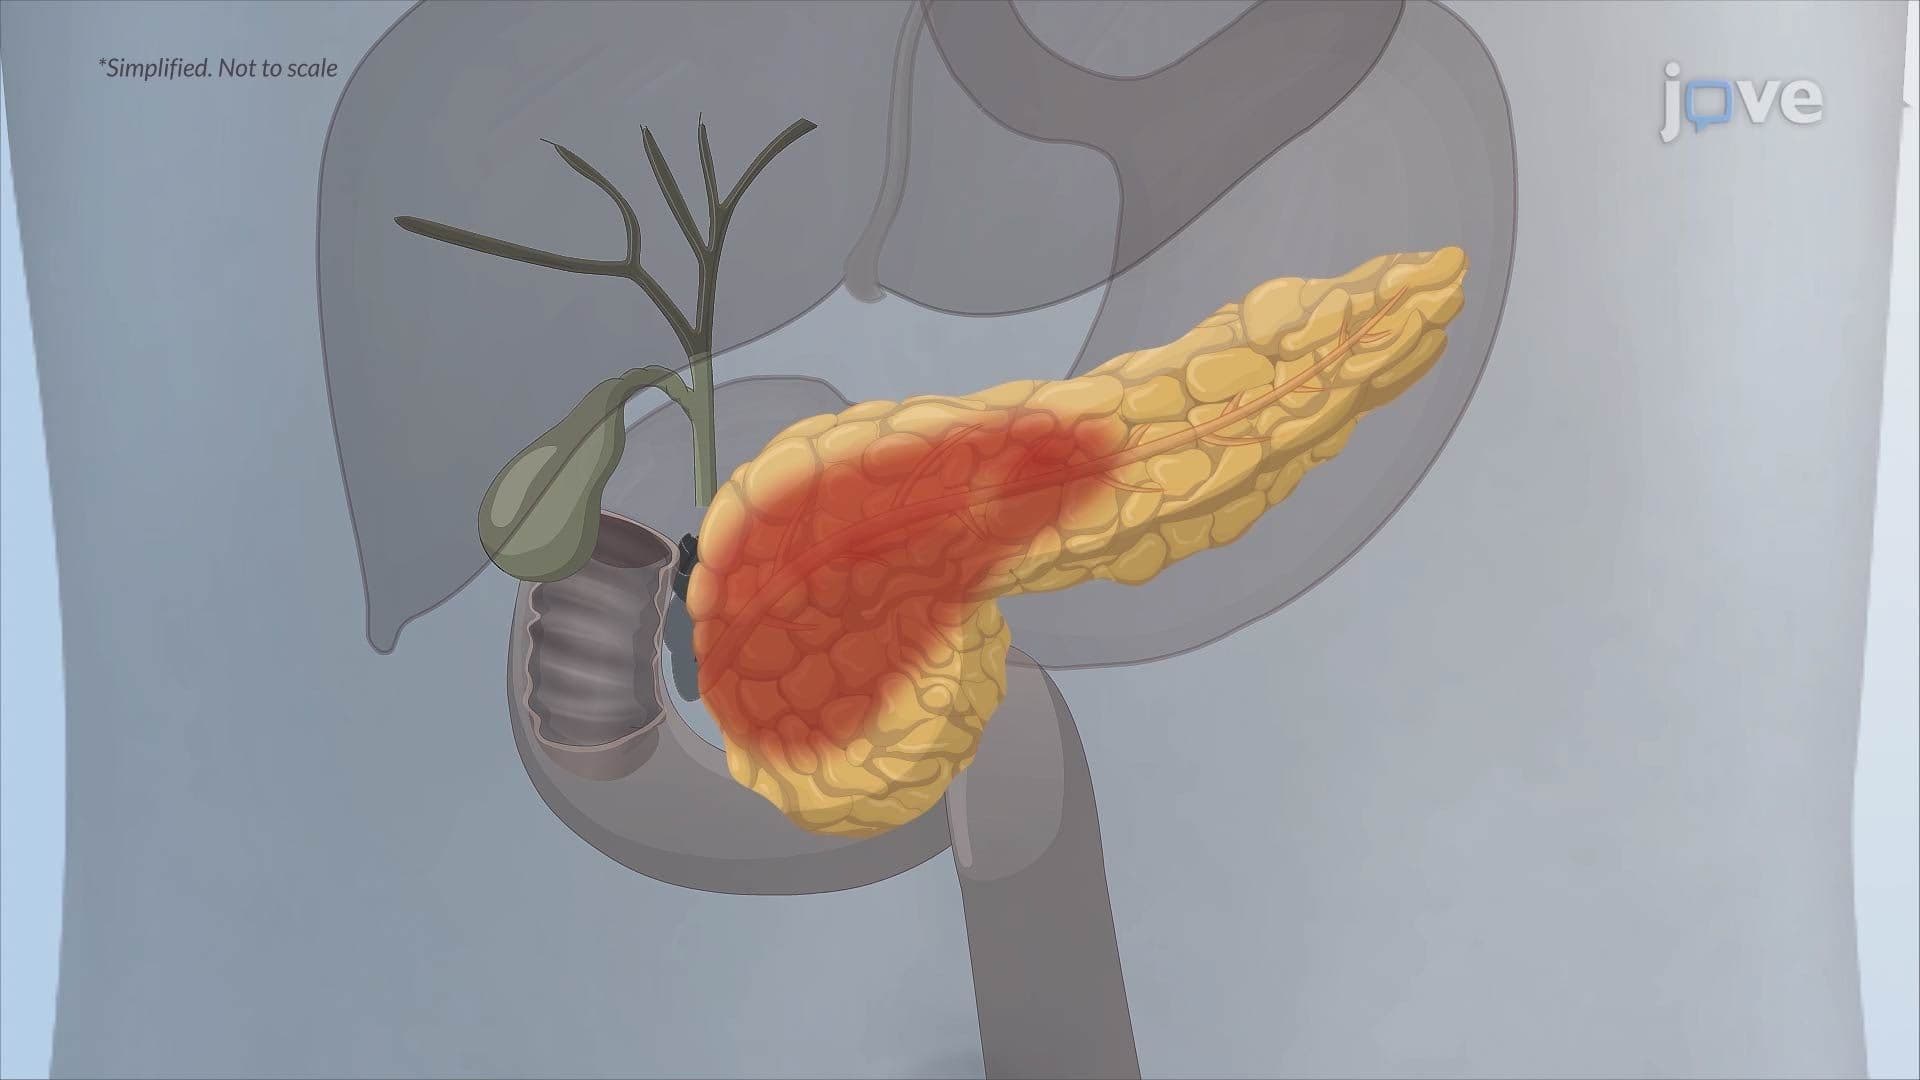
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Chronic Pancreatitis I: Introduction
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include: