Related Experiment Video
Updated: May 22, 2026
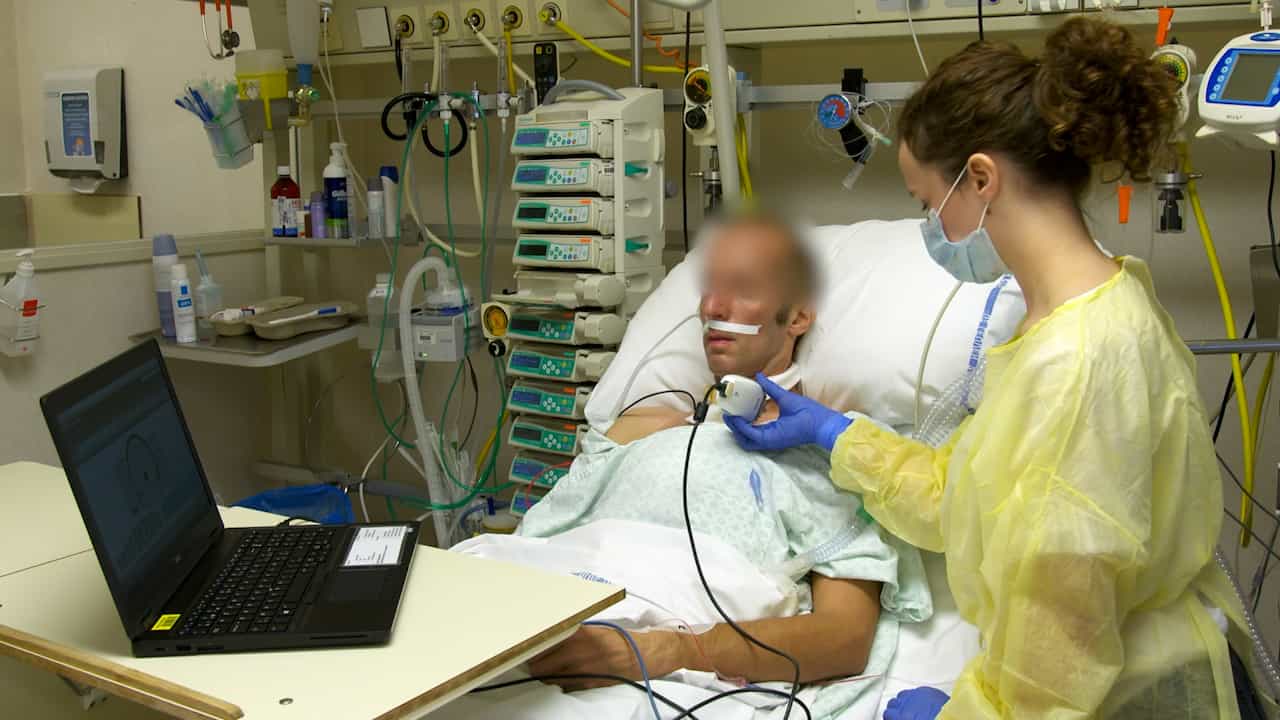

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Intensive medical nutrition therapy: methods to improve nutrition provision in the critical care setting
Patricia M Sheean1, Sarah J Peterson, Weihan Zhao
1University of Illinois at Chicago Institute for Health Policy and Research, Chicago, IL 60608, USA. psheea1@uic.edu

Abstract:
Patients requiring mechanical ventilation in an intensive care unit commonly fail to attain enteral nutrition (EN) infusion goals. We conducted a cohort study to quantify and compare the percentage of energy and protein received between standard care (n=24) and intensive medical nutrition therapy (MNT) (n=25) participants; to assess the percentage of energy and protein received varied by nutritional status, and to identify barriers to EN provision. Intensive MNT entailed providing energy at 150% of estimated needs, using only 2.0 kcal/cc enteral formula and 24-hour infusions. Estimated energy and protein needs were calculated using 30 kcal/kg and 1.2 g protein/kg actual or obesity-adjusted admission body weight. Subjective global assessment was completed to ascertain admission intensive care unit nutritional status. Descriptive statistics and survival analyses were conducted to examine time until attaining 100% of feeding targets. Patients had similar estimated energy and protein needs, and 51% were admitted with both respiratory failure and classified as normally nourished (n=25/49). Intensive MNT recipients achieved a greater percentage of daily estimated energy and protein needs than standard care recipients (1,198±493 vs 475±480 kcal, respectively, P<0.0001; and 53±25 vs 29±32 g, respectively, P=0.007) despite longer intensive care unit stays. Cox proportional hazards models showed that intensive MNT patients were 6.5 (95% confidence interval 2.1 to 29.0) and 3.6 (95% confidence interval 1.2 to 15.9) times more likely to achieve 100% of estimated energy and protein needs, respectively, controlling for confounders. Malnourished patients (n=13) received significantly less energy (P=0.003) and protein (P=0.004) compared with normally nourished (n=11) patients receiving standard care. Nutritional status did not affect feeding intakes in the intensive MNT group. Clinical management, lack of physician orders, and gastrointestinal issues involving ileus, gastrointestinal hemorrhage, and EN delivery were the most frequent clinical impediments to EN provision. It was concluded that intensive MNT could achieve higher volumes of EN infusion, regardless of nutritional status. Future studies are needed to advance this methodology and to assess its influence on outcomes.
Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:20
Acute Kidney Injury V: Interprofessional Care