Related Experiment Video
Updated: May 22, 2026

Biochemical Measurement of Neonatal Hypoxia
Published on: August 24, 2011
UGT1A1, SLCO1B1, and SLCO1B3 polymorphisms vs. neonatal hyperbilirubinemia: is there an association?
Laura Alencastro de Azevedo1, Themis Reverbel da Silveira, Clarissa Gutierrez Carvalho
1Postgraduate Program in Child and Adolescent Health, Universidade Federal do Rio Grande do Sul, Porto Alegre, Brazil.

Insights
Genetic variations in newborns can influence jaundice risk, especially with other conditions. Certain gene variants may offer protection against hyperbilirubinemia, while others combined with G6PD deficiency increase risk.
Area of Science:
- Neonatal Medicine
- Medical Genetics
- Pharmacogenomics
Background:
- Jaundice is common in newborns, but severe hyperbilirubinemia affects 5-6%.
- Genetic variations may increase hyperbilirubinemia risk when combined with other factors.
- Investigating genetic predispositions is crucial for understanding severe neonatal jaundice.
Purpose of the Study:
- To investigate the association between specific gene polymorphisms and the risk of severe hyperbilirubinemia in newborns.
- To explore the role of UGT1A1, SLCO1B1, and SLCO1B3 gene variants in neonatal jaundice.
Main Methods:
- Study included newborns with gestational age >35 weeks and weight >2,000g requiring phototherapy.
- Analyzed polymorphisms in UGT1A1 (rs8175347), SLCO1B1 (rs4149056, rs2306283), and SLCO1B3 (rs17680137, rs2117032) using capillary electrophoresis.
- Compared allelic and genotypic frequencies between 167 hyperbilirubinemic infants and 247 controls.
Main Results:
- While gender, ABO incompatibility, birth weight, and gestational age differed, SLCO1B gene polymorphism frequencies did not significantly vary between groups.
- Logistic regression identified ABO incompatibility, gestational age, and the rs2117032 T allele as significant factors.
- The rs2117032 polymorphism appeared protective against hyperbilirubinemia.
- Homozygosity for the rs2306283 G allele and glucose-6-phosphate-dehydrogenase deficiency were more common in infants with hyperbilirubinemia.
Conclusions:
- Genetic variations contribute significantly to neonatal hyperbilirubinemia.
- The interplay between genetic polymorphisms and environmental factors requires further investigation.
- Understanding these associations can inform risk assessment and management strategies for neonatal jaundice.
Background:
Jaundice is a physiological phenomenon; however, severe hyperbilirubinemia occurs in only 5 to 6% of the healthy newborn population. It has been suggested that genetic variation could enhance the risk of hyperbilirubinemia when coexpressed with other icterogenic conditions.
Methods:
The study included newborns with a gestational age of greater than 35 wk and weights greater than 2,000 g with indications for phototherapy. The polymorphisms from UGT1A1 (rs8175347), SLCO1B1 (rs4149056 and rs2306283), and SLCO1B3 (rs17680137 and rs2117032) were analyzed by capillary electrophoresis and hydrolysis probes.
Results:
A total of 167 hyperbilirubinemic infants and 247 control subjects were enrolled. The gender, ABO incompatibility, birth weight, and gestational age differed between the groups, but the allelic and genotypic frequency of the polymorphisms from SLCO1B genes did not. In logistic regression, the ABO incompatibility, gestational age, and polymorphic T allele of rs2117032 remained in the model. The presence of this polymorphism seemed to provide protection from hyperbilirubinemia. The individuals who were homozygous for the G allele of rs2306283 and who were glucose 6-phosphate-dehydrogenase deficient were more frequent among the cases.
Conclusion:
Although genetic variation accounts for a good part of this condition, the association between different polymorphisms and environmental factors has yet to be explained.
Related Concept Videos
 01:16
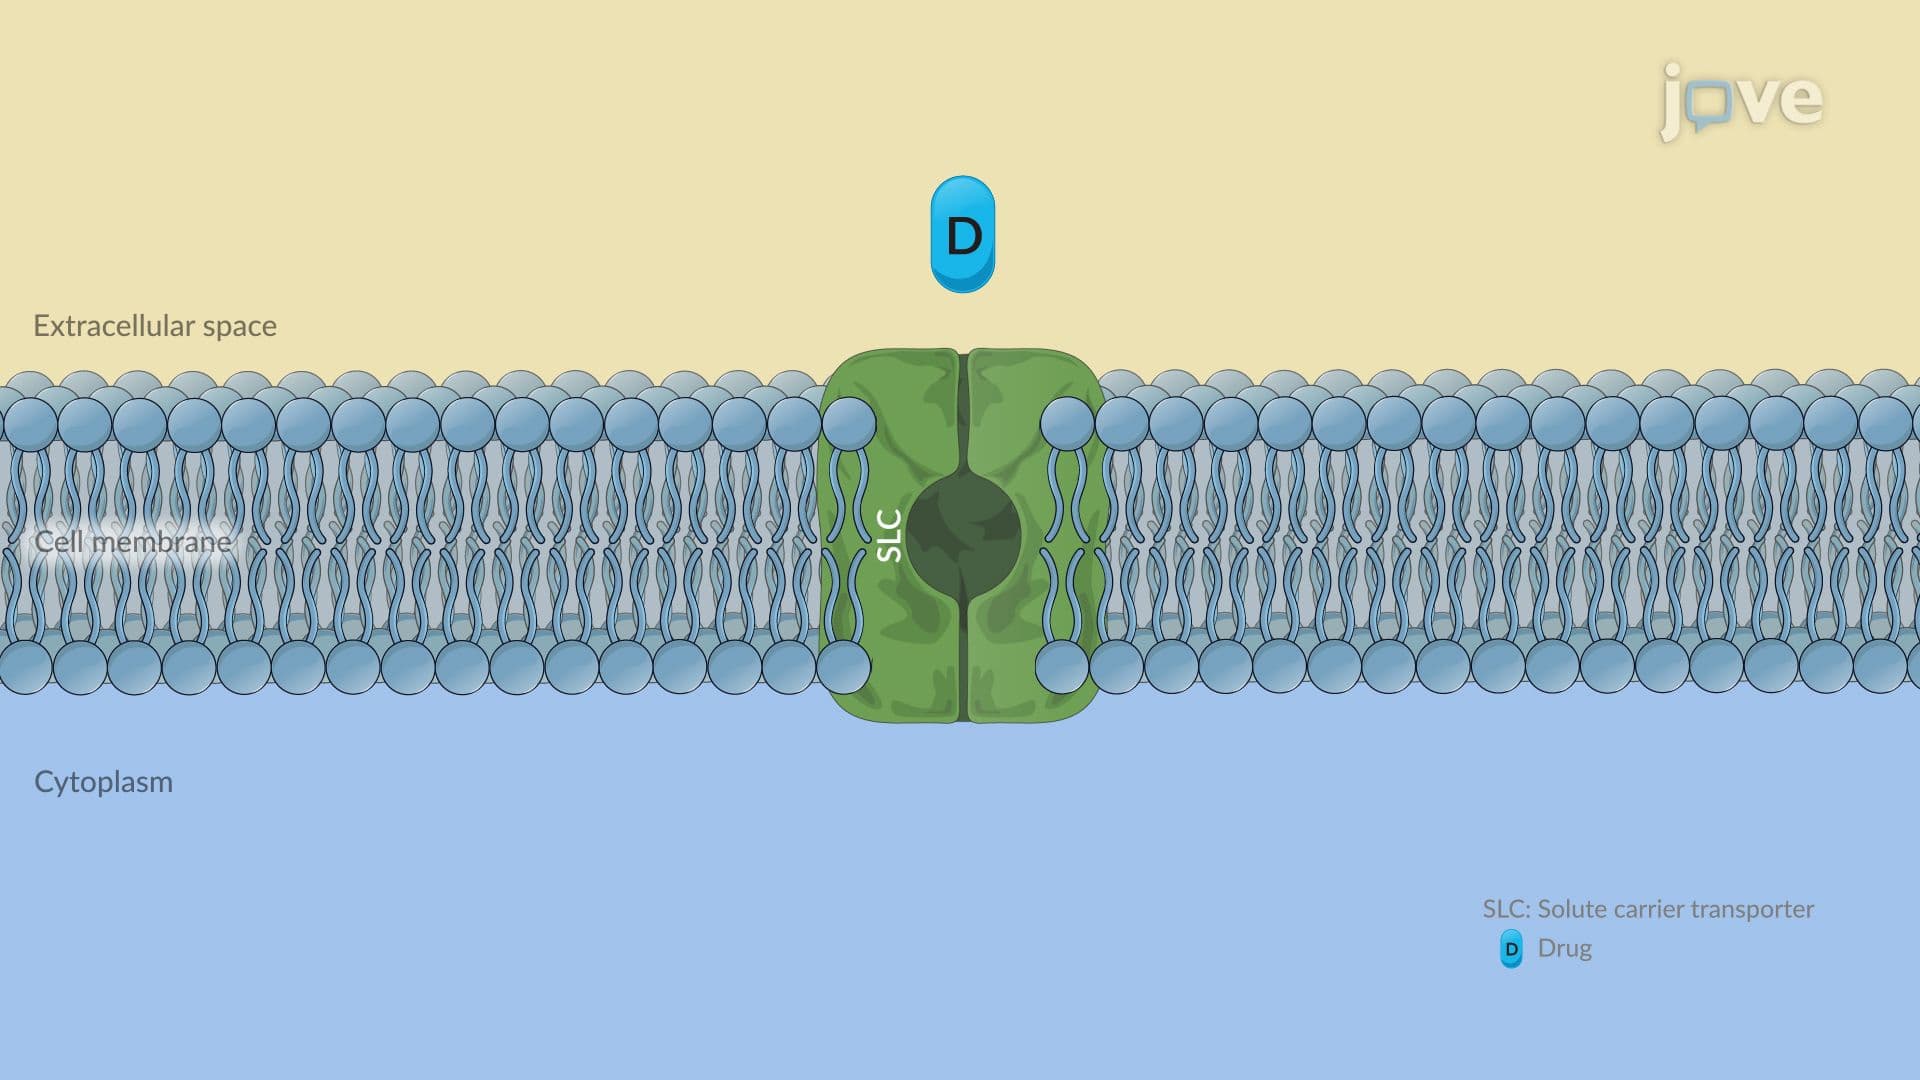
Pharmacogenetics of Drug Transporters: P-Glycoprotein and Solute Carrier Transporters
 01:25
Jaundice
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu
 01:11
Pharmacogenetics of Drug Targets: β₂-Adrenergic Receptors, Apo E, Thymidylate Synthase
 01:27
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase