Related Experiment Video
Updated: Oct 3, 2026
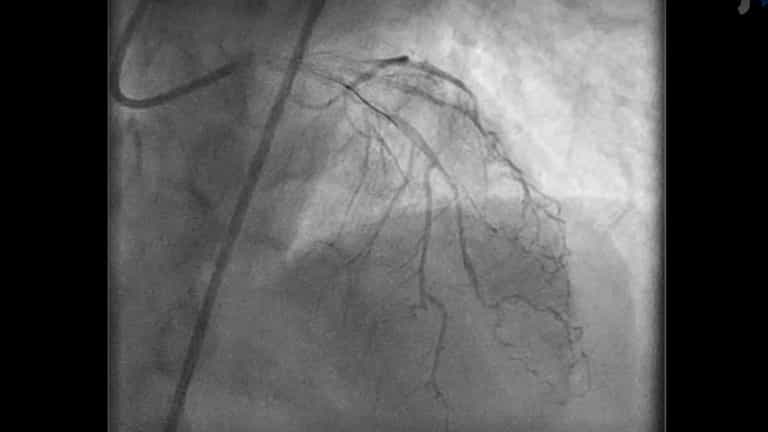
Acetylcholine Re-Challenge After Intracoronary Nitroglycerine Administration
Published on: April 4, 2022
Hypertension and arrhythmias: effects of slow-release nicardipine vs chlorthalidone: a double-blind crossover study
M Galderisi1, A Celentano, P Tammaro
1Cardioangiology Department-2nd Medical School, University of Naples, Italy.

Abstract:
The aim of the study was to compare the effect of slow-release (SR) nicardipine, placebo and chlorthalidone on hypertension-related arrhythmias evaluating 24-h ambulatory ECG. After a 2-week placebo run-in, the patients were randomized according to a double-blind design and treated with either SR nicardipine (40 mg b.i.d.) or chlorthalidone (25 mg once daily) for 8 weeks. At the end of this period, the patients were again treated with placebo for an additional 2 weeks and then crossed over and treated with either SR nicardipine or chlorthalidone for another 8 weeks. Three patients were withdrawn from the study at the end of the first period (1 after SR nicardipine and 2 after chlorthalidone) because of severe arrhythmias (Lown's class 4B) requiring antiarrhythmic therapy. The statistical evaluation was performed on data from 36 patients. SR nicardipine and chlorthalidone determined a significant reduction of both systolic and diastolic BP, with greater decrease with SR nicardipine and without modification of HR. Twenty-four-h ambulatory ECG showed a reduction of both supraventricular and ventricular arrhythmias by SR nicardipine not only compared to placebo but also vs chlorthalidone. Similarly, the severity of ventricular arrhythmias, according to Lown's classes, was reduced only after SR nicardipine. These results were confirmed also dividing the patients according to echocardiographic criteria of LVH. The adverse effects were slight and well tolerated with both drugs. Among hematochemical data, only chlorthalidone induced significant reduction of blood potassium (with 3 cases of hypokalemia). In conclusion, SR nicardipine was found to be more efficacious than chlorthalidone in controlling not only BP but also the arrhythmic events related to hypertension.
Related Concept Videos
 01:18
Antihypertensive Drugs: Action of Calcium Channel Blockers
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...