Related Experiment Video
Updated: May 22, 2026


Establishment and Evaluation of a Risk Prediction Model for Pathological Escalation of Gastric Low-Grade Intraepithelial Neoplasia
Published on: February 16, 2024
Chronic atrophic gastritis is a progressive disease: analysis of medical reports from Shanghai (1985-2009)
Eugene Yuo Hao Chooi1, Hui-Min Chen, Qi Miao
1Division of Gastroenterology and Hepatology, Shanghai Jiao-Tong University School of Medicine, Renji Hospital, Shanghai 200001, China.

Introduction:
We aimed to examine the turnover of chronic atrophic gastritis (CAG) pathologically and endoscopically and explore its potential causes.
Methods:
A retrospective analysis was conducted of prospective data collected from 1,592 patients who underwent gastroscopy three times or more during the period 1985-2009 at Renji Hospital, Shanghai, China. Pathological and endoscopic findings were analysed. Data collected included gender, age, length of follow-up period, family history, past medical history, history of Helicobacter (H.) pylori infection, drug history for the use of proton pump inhibitors (PPIs), antacids and non-steroidal anti-inflammatory drugs [NSAIDs], and lifestyle history, including the patients' eating habits.
Results:
23 (1.44%) patients presented with gastric cancers resulting from CAG and 349 (21.92%) patients had dysplasia. Pathological and endoscopic findings suggested that the proportion of patients with worsening gastric mucosa during the atrophic and intestinal metaplasia (IM) phases was over 35% with increasing age. Gastric mucosa was found to be pathologically aggravated by carbonated drinks and fast food, and pathologically degenerated by H. pylori infection. Smoking deteriorated the gastric mucosa. Side dishes of vegetables may benefit the gastric mucosa even in the atrophic and IM phases.
Conclusion:
Our findings support the consensus that CAG is a progressive disease. Potential factors that were found to affect the state of the gastric mucosa in our patient group were gender, H. pylori infection, use of PPIs or NSAIDs, and intake of vegetable side dishes, spicy food, carbonated drinks and fast food.
Related Concept Videos
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:26
Gastritis II: Pathophysiology
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:25
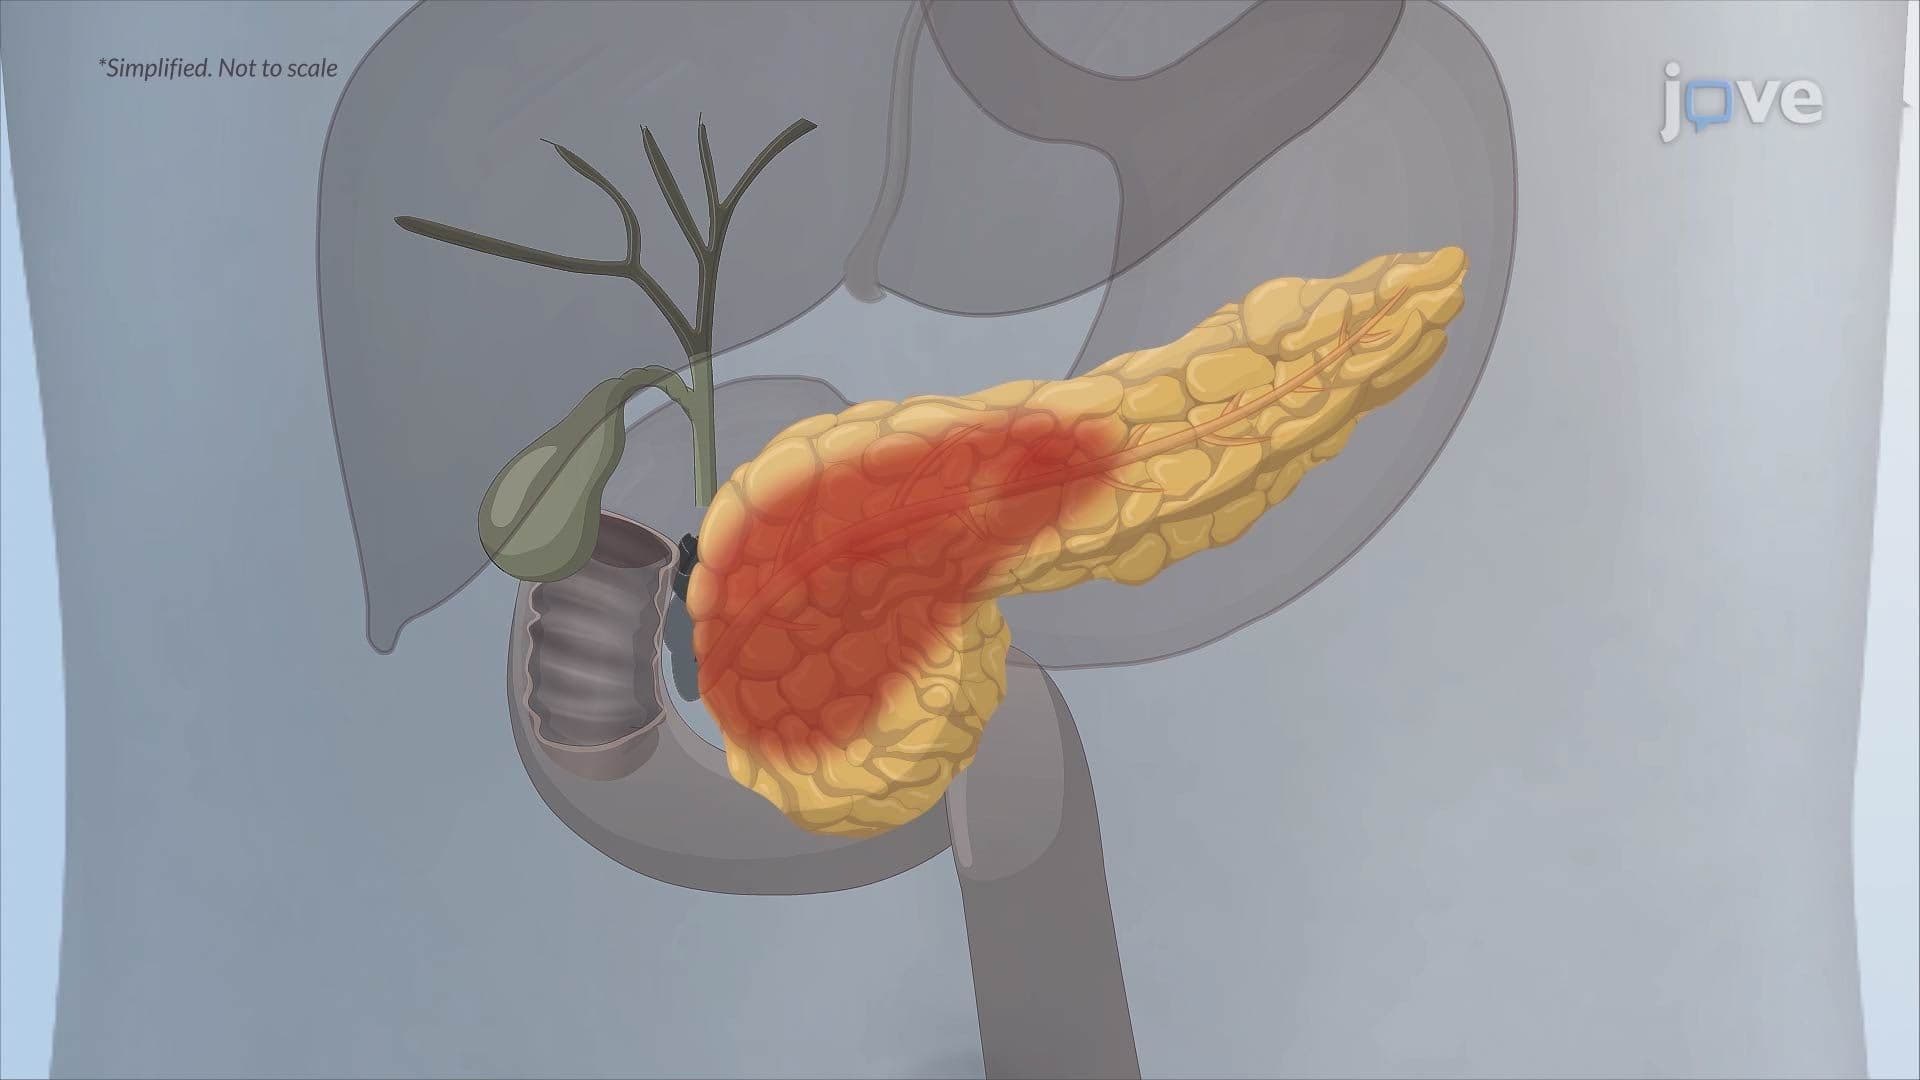
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...