Related Experiment Video
Updated: May 22, 2026
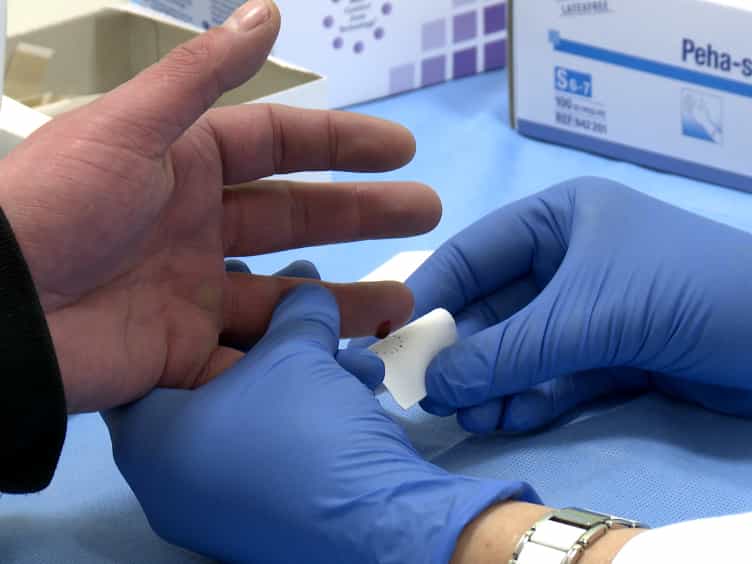

Dried Blood Spots - Preparing and Processing for Use in Immunoassays and in Molecular Techniques
Published on: March 13, 2015
Difference in serum complement component C4a levels between hepatitis C virus carriers with persistently
Kazuyuki Imakiire1, Hirofumi Uto, Yuko Sato
1Digestive and Lifestyle Diseases, Department of Human and Environmental Sciences, Kagoshima University Graduate School of Medical and Dental Sciences, Kagoshima, Japan.

Certain hepatitis C virus (HCV) carriers exhibit persistently normal alanine aminotransferase (ALT) levels (PNALT) (≤ 30 IU/l) accompanied by normal platelet counts (≥ 15 x 10(4)/µl); these individuals show milder disease activity and slower progression to cirrhosis. This study aimed to elucidate the characteristics of HCV carriers with PNALT using serum proteomics. The first group of subjects, who underwent clinical evaluation in the hospital, consisted of 19 HCV carriers with PNALT (PNALT-1) and 20 chronic hepatitis C (CHC-1) patients. The second group of subjects was part of a cohort study on the natural history of liver disease, and included 37 PNALT (PNALT-2) and 30 CHC (CHC-2) patients. Affinity bead-purified serum protein was subjected to matrix-assisted laser desorption ionization time-of-flight mass spectrometry analysis. Serum proteomics showed that 6 protein peaks with mass-to-charge ratios ranging from 1,000 to 3,000 differed significantly between the PNALT-1 and CHC-1 groups. Among these peaks, a 1738-m/z peak protein was identified as a fragment of complement component 4 (C4) and correlated significantly with serum C4a concentrations as determined by enzyme immunoassay. Serum C4a levels were also significantly higher in the PNALT-2 group compared to the CHC-2 group and healthy volunteers. Furthermore, in the PNALT-2 group, serum C4a levels negatively correlated with transaminase levels, but not with other biochemical tests, HCV core antigen levels, peripheral blood cell counts or serum hepatic fibrosis markers. This study indicates that host factors such as C4a not only differ between HCV carriers with PNALT and CHC, but that proteomic approaches could also contribute to the elucidation of factors in PNALT as more differences are discovered.
Certain hepatitis C virus (HCV) carriers exhibit persistently normal alanine aminotransferase (ALT) levels (PNALT) (≤ 30 IU/l) accompanied by normal platelet counts (≥ 15 x 10(4)/µl); these individuals show milder disease activity and slower progression to cirrhosis. This study aimed to elucidate the characteristics of HCV carriers with PNALT using serum proteomics. The first group of subjects, who underwent clinical evaluation in the hospital, consisted of 19 HCV carriers with PNALT (PNALT-1) and 20 chronic hepatitis C (CHC-1) patients. The second group of subjects was part of a cohort study on the natural history of liver disease, and included 37 PNALT (PNALT-2) and 30 CHC (CHC-2) patients. Affinity bead-purified serum protein was subjected to matrix-assisted laser desorption ionization time-of-flight mass spectrometry analysis. Serum proteomics showed that 6 protein peaks with mass-to-charge ratios ranging from 1,000 to 3,000 differed significantly between the PNALT-1 and CHC-1 groups. Among these peaks, a 1738-m/z peak protein was identified as a fragment of complement component 4 (C4) and correlated significantly with serum C4a concentrations as determined by enzyme immunoassay. Serum C4a levels were also significantly higher in the PNALT-2 group compared to the CHC-2 group and healthy volunteers. Furthermore, in the PNALT-2 group, serum C4a levels negatively correlated with transaminase levels, but not with other biochemical tests, HCV core antigen levels, peripheral blood cell counts or serum hepatic fibrosis markers. This study indicates that host factors such as C4a not only differ between HCV carriers with PNALT and CHC, but that proteomic approaches could also contribute to the elucidation of factors in PNALT as more differences are discovered.

Related Concept Videos
 01:25
Hepatitis
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:28
Viral Hepatitis I: Introduction