Related Experiment Video
Updated: May 22, 2026
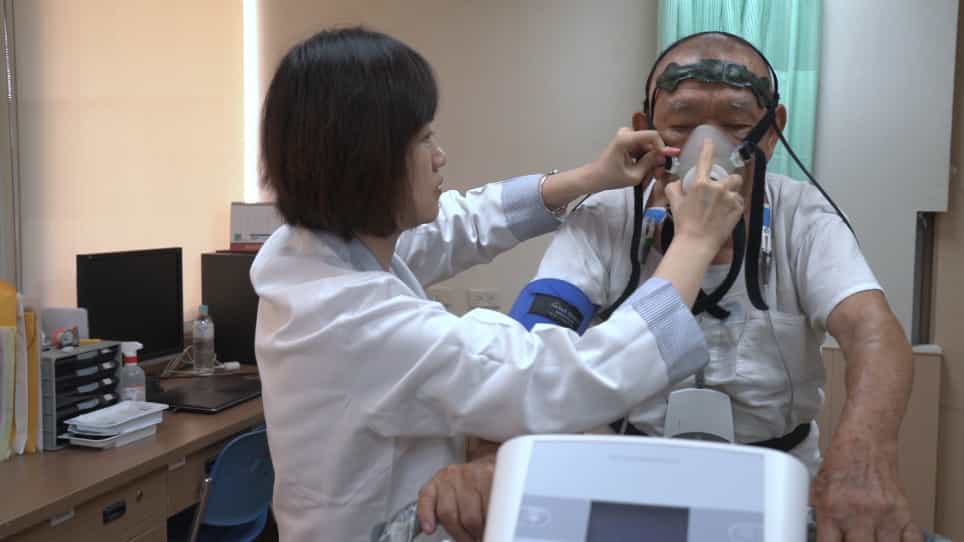

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
[The source and influential factors in signals of trans-esophageal oxygen saturation]
1Department of Anesthesiology, West China Hospital, Sichuan University, Chengdu 610041, China.

Abstract:
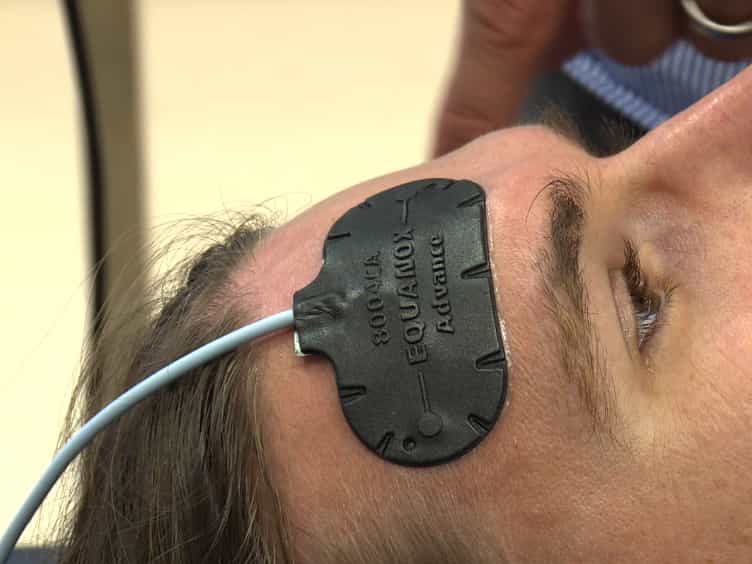
This paper is aimed to investigate the signal source and influential factors in signals of trans-esophageal pulse oxygen saturation (SeO2). The red light of the SeO2 probe was faced directly to the descending aorta (DA) of the mongrel dogs. The readings and waveform of SeO2 signals were recorded under following conditions: before and after DA was shield; before and after the blood supply of esophagus was cut off; under the different touch pressures between the SeO2 probe and the esophageal wall. The readings and waveform of SeO2 signals were also recorded respectively at both different esophageal depth and directions when mechanical ventilation was on and off. The tongue oxygen saturation (StO2) was recorded simultaneously as control. The waveform of SeO2 signals disappeared after DA was shield (P < 0.001). No significant difference was found in the SeO2 signals before and after the blood supply of esophagus was cut off (P > 0.05). Compared with the StO2 readings when the SeO2 probe was placed at different esophageal depth, the waldeyer ring, cervical area and thoracic inlet,the readings of SeOz significantly decreased (P < 0.05) while mechanical ventilation was on and off. However, there was no significant difference in the readings between SeO2 signals from DA, aortic arch (AA) and left subclavian artery and the StO2 signals recorded simultaneously. Mechanical ventilation had a remarkable effect on the SeO2 signals at different esophageal depth (P < 0.05), but the StO2 signals lay in its insensitivity to its influence. The readings of StO2 signals were significantly different from that of StO2 signals when the touch pressure between the SeO2 probe and the esophageal wall below 40 mmHg (P < 0.01). The directions of the optimum SeO2 signals acquired at different esophageal depth were not the same. The SeO2 signals were primarily derived from deeper arteries around the esophagus. All of Mechanical ventilation, location of the SeO2 probe in the esophagus and the touch pressure between the probe and esophageal wall can influence SeO2 signals.
Related Concept Videos
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is important.
 01:24
Pulse Oximetry
Purpose
Average SpO2 values are greater than 95%. If the readings fall below 90%, it indicates that...
 01:19
Guidelines For Measuring Vital Signs
Before taking a patient's vital signs, a nurse would consider and assess the patient's comfort level and ensure appropriate equipment is available.
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:17
Other Factors Affecting Respiration Centers
However, the ability to hold one's breath voluntarily is not limitless. When the CO2 concentration in the blood reaches a critical level,...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...