Related Experiment Video
Updated: May 22, 2026


Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
[How to deal with those low parathyroid hormone values in dialysis patients?]
Guillaume Jean1, Marie-Hélène Lafage-Proust, Jean-Claude Souberbielle
1Nephrocare Tassin-Charcot, 7, avenue Maréchal-Foch, 69110 Sainte-Foy-Les-Lyon, France. guillaume-jean-crat@wanadoo.fr

Background:
The target for serum parathyroid (PTH) hormone level in dialysis patients is higher than that in the normal population in order to prevent adynamic bone disease (ABD) that is associated with more frequent cardiovascular and bone disease. Based on biological and clinical data, we aimed at identifying the different types of low PTH (L-PTH) in order to determine the best therapeutic strategies in these patients.
Methods:
Between 2004 and 2010, all haemodialysis (HD) patients were assessed. Patients with serum L-PTH (<130pg/mL) were classified into five groups as follows : 'PTX' for patients with a history of parathyroidectomy (PTX); 'HypoMed' for patients with a tendency to hypocalcemia without PTX; 'IatroMed' for patients who had undergone excessive PTH-lowering treatments (calcium, vitamin D, or cinacalcet); 'EndoG' for patients with endogenous hypercalcaemia (immobilization, cancer, or granulomatosis); and 'SponT' for patients with L-PTH without evident causes and with 'normal' biology in most cases.
Results:
From 520 charts, 163 (31.3 %) L-PTH cases were recorded, with 17.7% of PTX in younger patients with longer dialysis times; 2.4% of HypoMed in older women with high co-morbidities (these two groups needed calcium and vitamin D therapy to prevent hypocalcaemia); 22.6% of IatroMed in diabetic patients receiving excessive PTH-lowering treatments; 3% of EndoG in hypercalcaemic patients, more frequently in the hospitalization ward; and 54% of SponT, more frequently comprising old diabetic patients not receiving PTH-lowering treatment and without biological signs of ABD. Treatment changes were necessary only in cases of IatroMed and EndoG, requiring a lowered prescription of PTH-lowering therapies and the addition of bisphosphonates for EndoG.
Conclusion:
In our HD population, we could identify five types of L-PTH based on medical conditions and biological data. Only two types, i.e. approximately 25% of patients needed therapeutic modifications. For the other patients, L-PTH could be maintained without decreasing the calcium and vitamin D intake that can lead to osteomalacia or administering recombinant PTH 1-34 or calcium-receptor inhibitors that need to be assessed in HD patients.
Related Concept Videos
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:25
Peritoneal Dialysis III: Nursing Management
 00:59
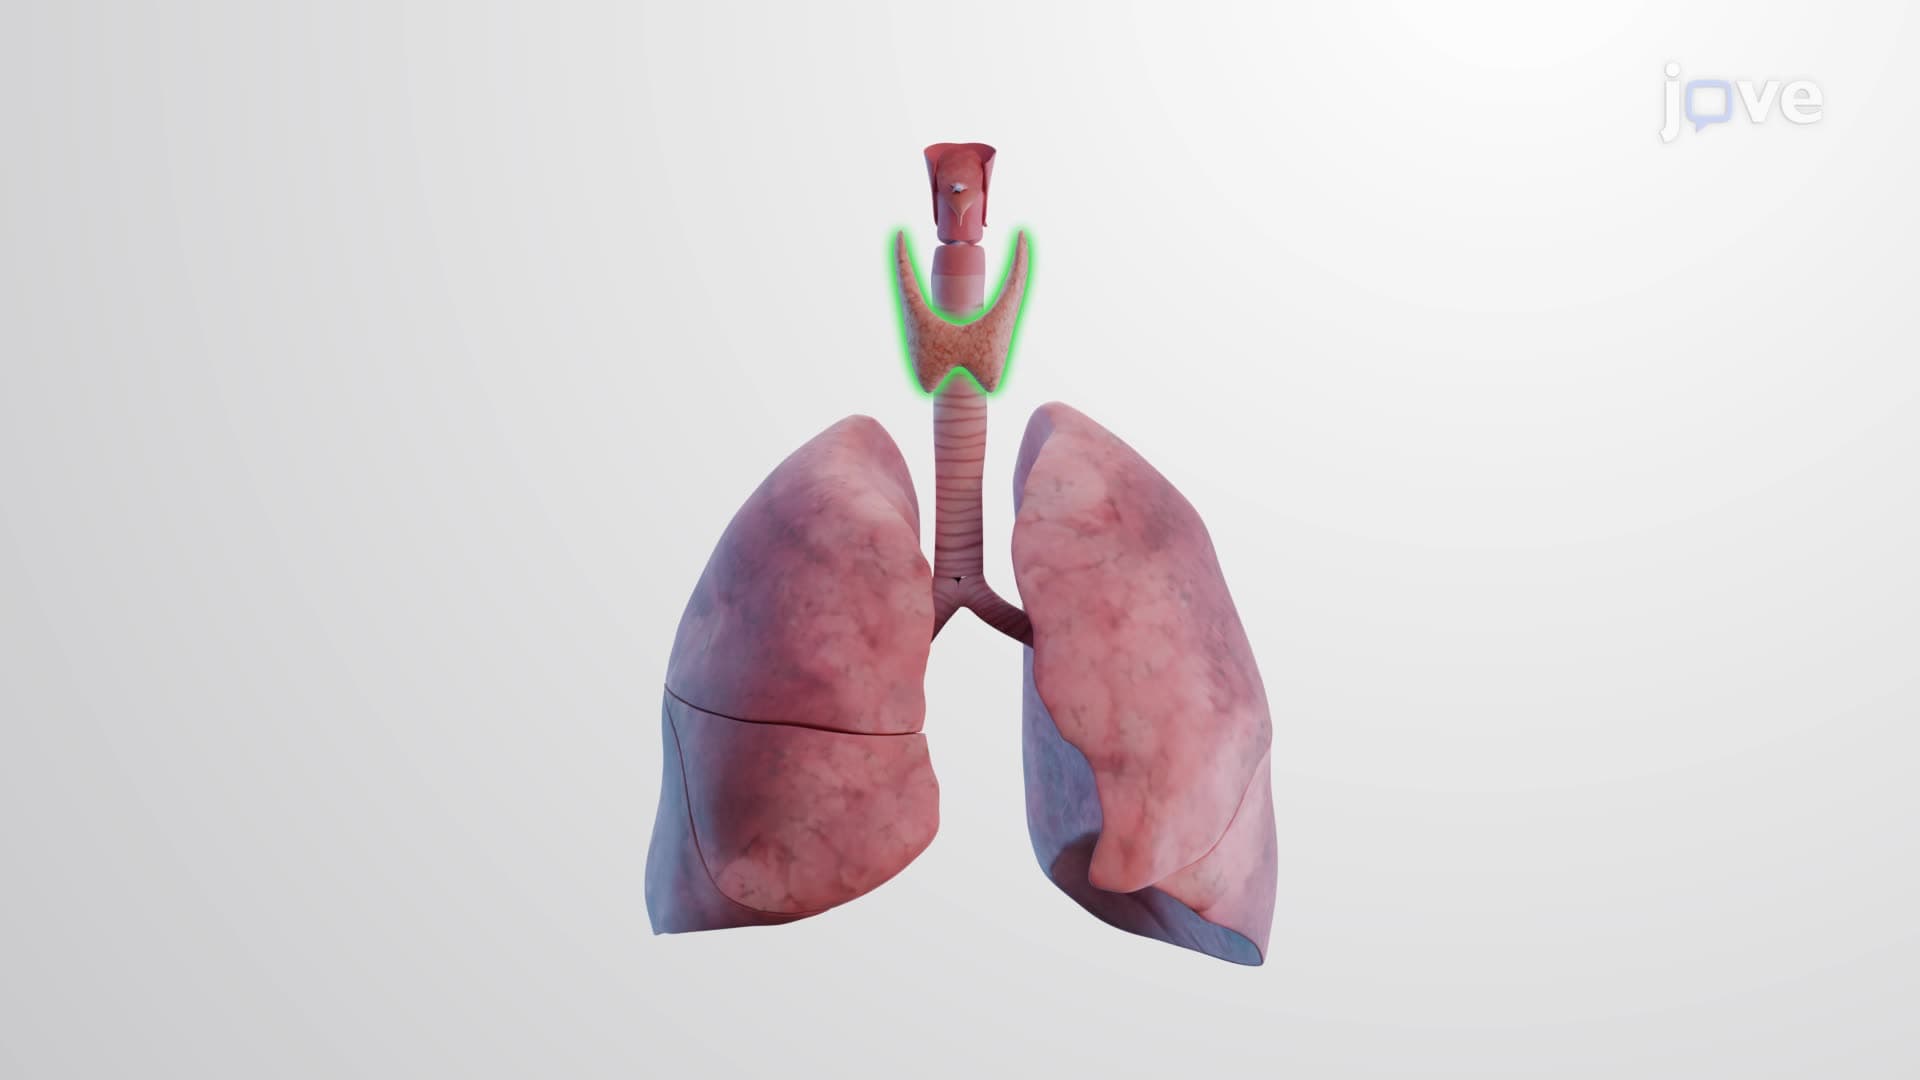
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:25
Hemodialysis III: Nursing Management
 01:21
Skeleton and Calcium Homeostasis
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...