Related Experiment Video
Updated: May 22, 2026
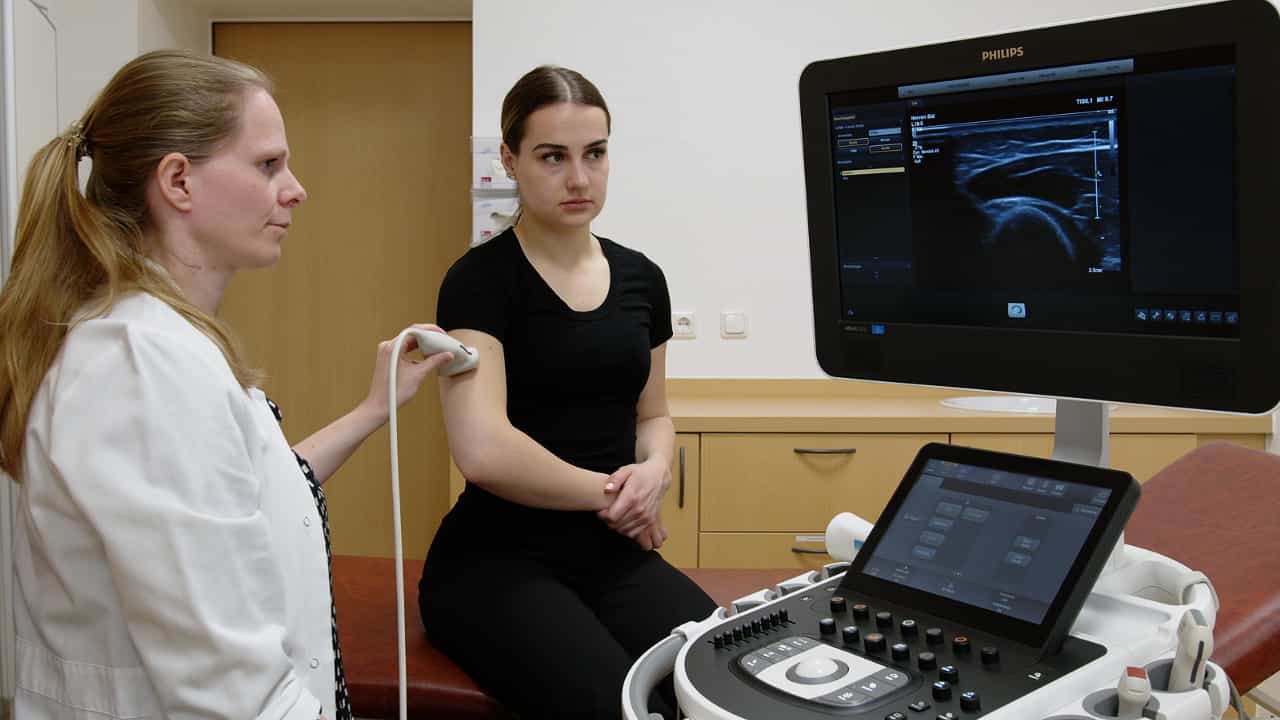

Nerve Ultrasound Protocol to Detect Dysimmune Neuropathies
Published on: October 7, 2021
Clinical and pathological heterogeneity in a series of 31 patients with IgM-related neuropathy
M Luigetti1, A Conte, N Montano
1Institute of Neurology, Catholic University of the Sacred Heart, Rome, Italy. mluigetti@gmail.com

Background:
IgM-related neuropathy generally presents as a late-onset demyelinating polyneuropathy with predominant sensory loss and ataxia. Sporadic cases with atypical presentation have been described.
Patients And Methods:
We report clinical and pathological findings from 31 patients with IgM-related neuropathy followed in our Institute of Neurology over a 20-year period.
Results:
Typical presentation with predominant sensory ataxic neuropathy was observed in 18/31 patients. In the remaining 13/31 (42%), we observed an atypical phenotype, characterized by multiple mononeuropathy or polyneuropathy with predominant motor impairment; one patient had polyneuropathy with predominant small-fibre involvement. Uncommon pathological findings consisting in inflammatory infiltrates, focal axonal loss or light chain deposition were observed in 8 patients, all with atypical clinical phenotype. Almost all patients with atypical phenotype improved with immunosuppressive therapy.
Conclusions:
A significant proportion of patients with IgM-related neuropathy presents with atypical clinical features. In these patients, sural nerve biopsy helps clarify heterogeneous disease mechanisms and identify patients who might benefit from immunosuppressive therapy.
Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:19
Type I Diabetes III: Clinical Manifestations
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:22
Diabetic Neuropathy
 01:26
Type I Diabetes II: Pathophysiology
 01:21
Chronic Pancreatitis II: Pathophysiology