Related Experiment Video
Updated: May 22, 2026


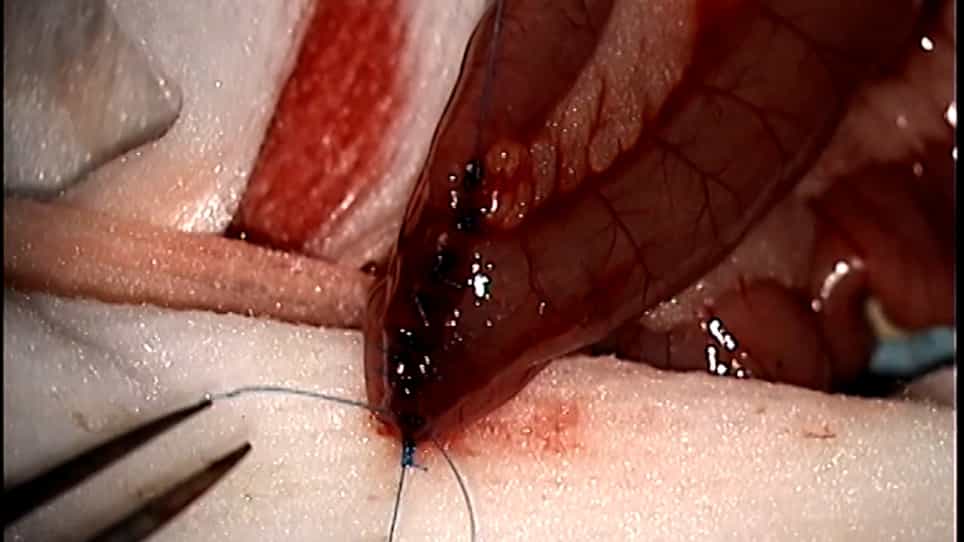
Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
Conjugated bile acids associate with altered rates of glucose and lipid oxidation after Roux-en-Y gastric bypass
M Simonen1, N Dali-Youcef, D Kaminska
1Department of Medicine, University of Eastern Finland and Kuopio University Hospital, Kuopio, Finland.

Background:
Laparoscopic Roux-en-Y gastric bypass (RYGB) induces a more favorable metabolic profile than expected by weight loss alone. In this study, we investigated the effect of RYGB on serum bile acid levels and their relation to clinical outcomes.
Methods:
We included 30 obese patients who underwent RYGB (BMI = 46.1 ± 5.9 kg/m(2)). Clinical measurements and laboratory determinations were performed before surgery and 1 year after surgery. Fasting serum bile acids were measured by an enzymatic method and individual bile acids were quantified by HLPC-tandem mass spectrometry. Indirect calorimetry was performed to measure the rates of energy expenditure and substrate oxidation.
Results:
Fasting total serum bile acid levels increased twofold after RYGB (pre, 3.68 ± 2.03 vs. post, 7.06 ± 9.65 micromol/l, +92 %, p = 0.002). This increase in total bile acids was accompanied by a decrease in conjugated bile acids, which correlated with decreased glucose oxidation (r = 0.571, p = 0.002) and with increased lipid oxidation (r = -0.626, p = 0.0004). The change in taurine-conjugated bile acids correlated with altered DIO2 mRNA expression in adipose tissue (r = -0.498, p = 0.013) potentially linking bile acid conjugation to substrate oxidation through DIO2.
Conclusions:
Fasting serum bile acid levels increase after RYGB. More specifically, changes in bile acid conjugation after RYGB associate with altered energy metabolism.

Related Concept Videos
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:24
Lipid Absorption
These breakdown products bind with bile salts and lecithin to form micelles, which quickly pass between microvilli to come in close contact with the apical...
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:19
Oral Hypoglycemic Agents: α-Glucosidase Inhibitors
Acarbose and miglitol are typically...
 01:20
Cholecystitis