Related Experiment Videos
Craniocervical fusions in children
1Department of Neurosurgery, University of Iowa Hospitals and Clinics, University of Iowa Carver College of Medicine, Iowa City, IA, USA.

Insights
Pediatric craniovertebral junction (CVJ) instability requires specialized surgical techniques. This review of over 850 pediatric CVJ fusions shows high success rates with modern instrumentation, ensuring safe craniocervical stabilization.
Area of Science:
- Neurosurgery
- Pediatric Orthopedics
- Spine Surgery
Background:
- Pediatric craniovertebral junction (CVJ) instability presents unique surgical challenges due to anatomical variations and smaller structures compared to adults.
- Syndromic abnormalities and diminutive osseous/ligamentous components further complicate management.
- Advances in imaging and instrumentation have enhanced treatment options for pediatric craniocervical stabilization.
Purpose of the Study:
- To review the author's extensive experience with over 850 pediatric craniovertebral junction (CVJ) fusions.
- To detail the indications and surgical techniques for atlantoaxial arthrodesis and occipitocervical fusion in children.
- To assess the outcomes, complications, and long-term effects of pediatric CVJ stabilization.
Main Methods:
- Review of surgical techniques for pediatric atlantoaxial and occipitocervical fusions, including historical (interlaminar rib graft) and modern (screw and rod fixation) approaches.
- Description of specific fixation methods: transarticular screws, lateral mass screws, C-2 pars/pedicle screws, C-2 translaminar screws, and contoured loop fixation.
- Analysis of outcomes based on fusion success rates and observed effects on spinal growth and patient well-being.
Main Results:
- Bone fusion success rates reached 98% with fusion alone and nearly 100% with rigid instrumentation.
- No abnormal spine growth was observed in children stabilized below age 5.
- No deleterious effects were noted in children treated with rigid instrumentation, indicating safety and efficacy.
Conclusions:
- Modern surgical techniques and instrumentation provide highly successful and safe management for pediatric craniovertebral junction instability.
- Craniocervical stabilization in pediatric patients can be achieved with excellent fusion rates and without compromising spinal growth.
- Detailed understanding of indications, techniques, and complication management is crucial for optimal outcomes in pediatric CVJ surgery.
Abstract:
The surgical management of craniovertebral junction (CVJ) instability in pediatric patients presents unique challenges. As compared with the adult patient, the anatomical variations of the CVJ in the pediatric patient are significant, complicate the approach, and limit the use of internal fixation. Diminutive osseous and ligamentous structures and syndromic craniovertebral abnormalities complicate the issue. Advances in imaging analysis and instrumentation have improved the armamentarium for managing the pediatric patient who requires craniocervical stabilization. In this paper, the author's experience of performing more than 850 pediatric CVJ fusions is reviewed. This work includes the indications for atlantoaxial arthrodesis and occipitocervical fusion. Early atlantoaxial fusions were performed using interlaminar rib graft fusion, and more recently using either transarticular screw fixation in the older patient, or lateral mass screws at C-1 and rod fixation with either C-2 pars interarticular screw fixation or pedicle screw fixation. A C-2 translaminar screw fixation is also described. Occipitocervical fusions are performed with rib grafts in patients younger than 6 years of age. Subsequently, above that age, contoured loop fixation was performed, and in the past 8-10 years, screw and rod fixation was used. Abnormal spine growth was not observed in children who underwent craniocervical stabilization below the age of 5 years (clearly the bone grew with the patient). However, no deleterious effects were noted in the children treated with rigid instrumentation. The success rate for bone fusion alone was 98%. The author's success rate with rigid instrumentation is nearly 100%. A detailed review of the technique of fusion is presented, as well as the indications and means of avoidance of complications, their prevention, and management.
Related Concept Videos
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:28
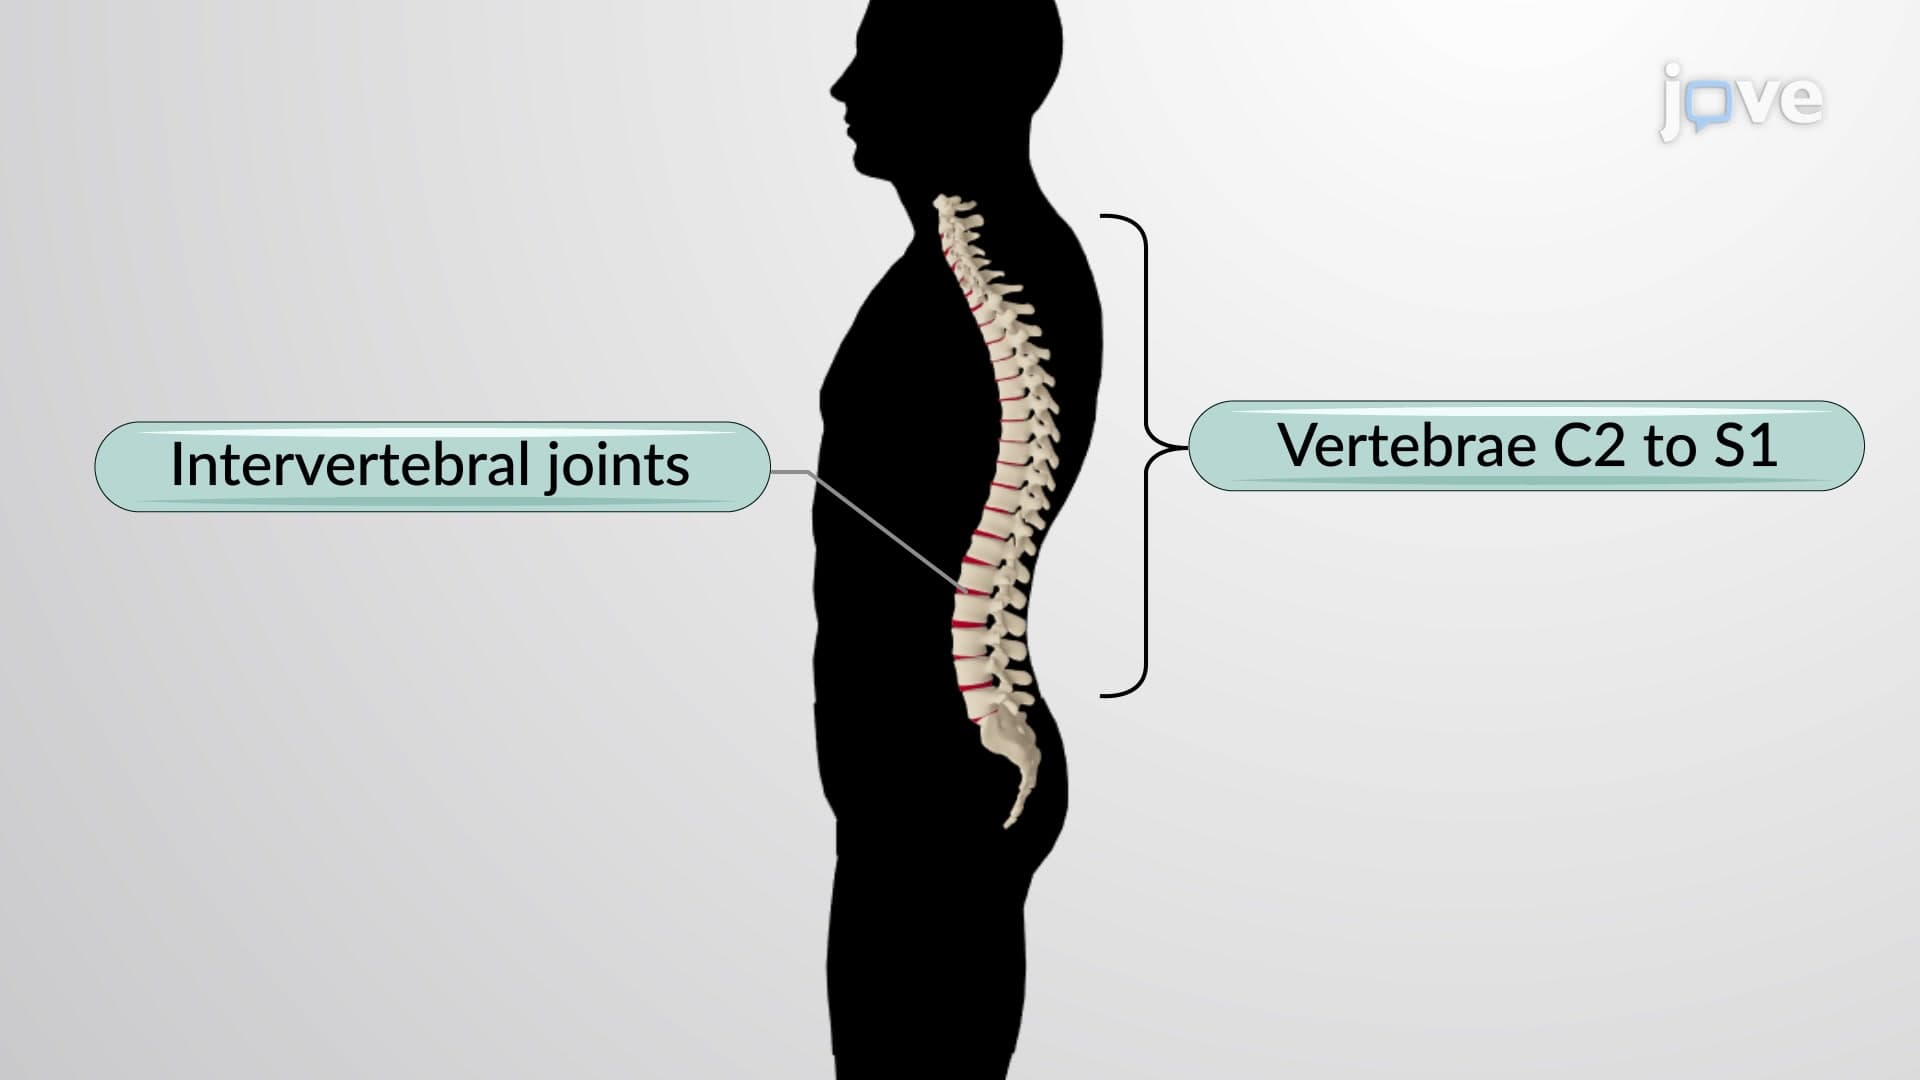
Articulations of the Vertebral Column
 01:16
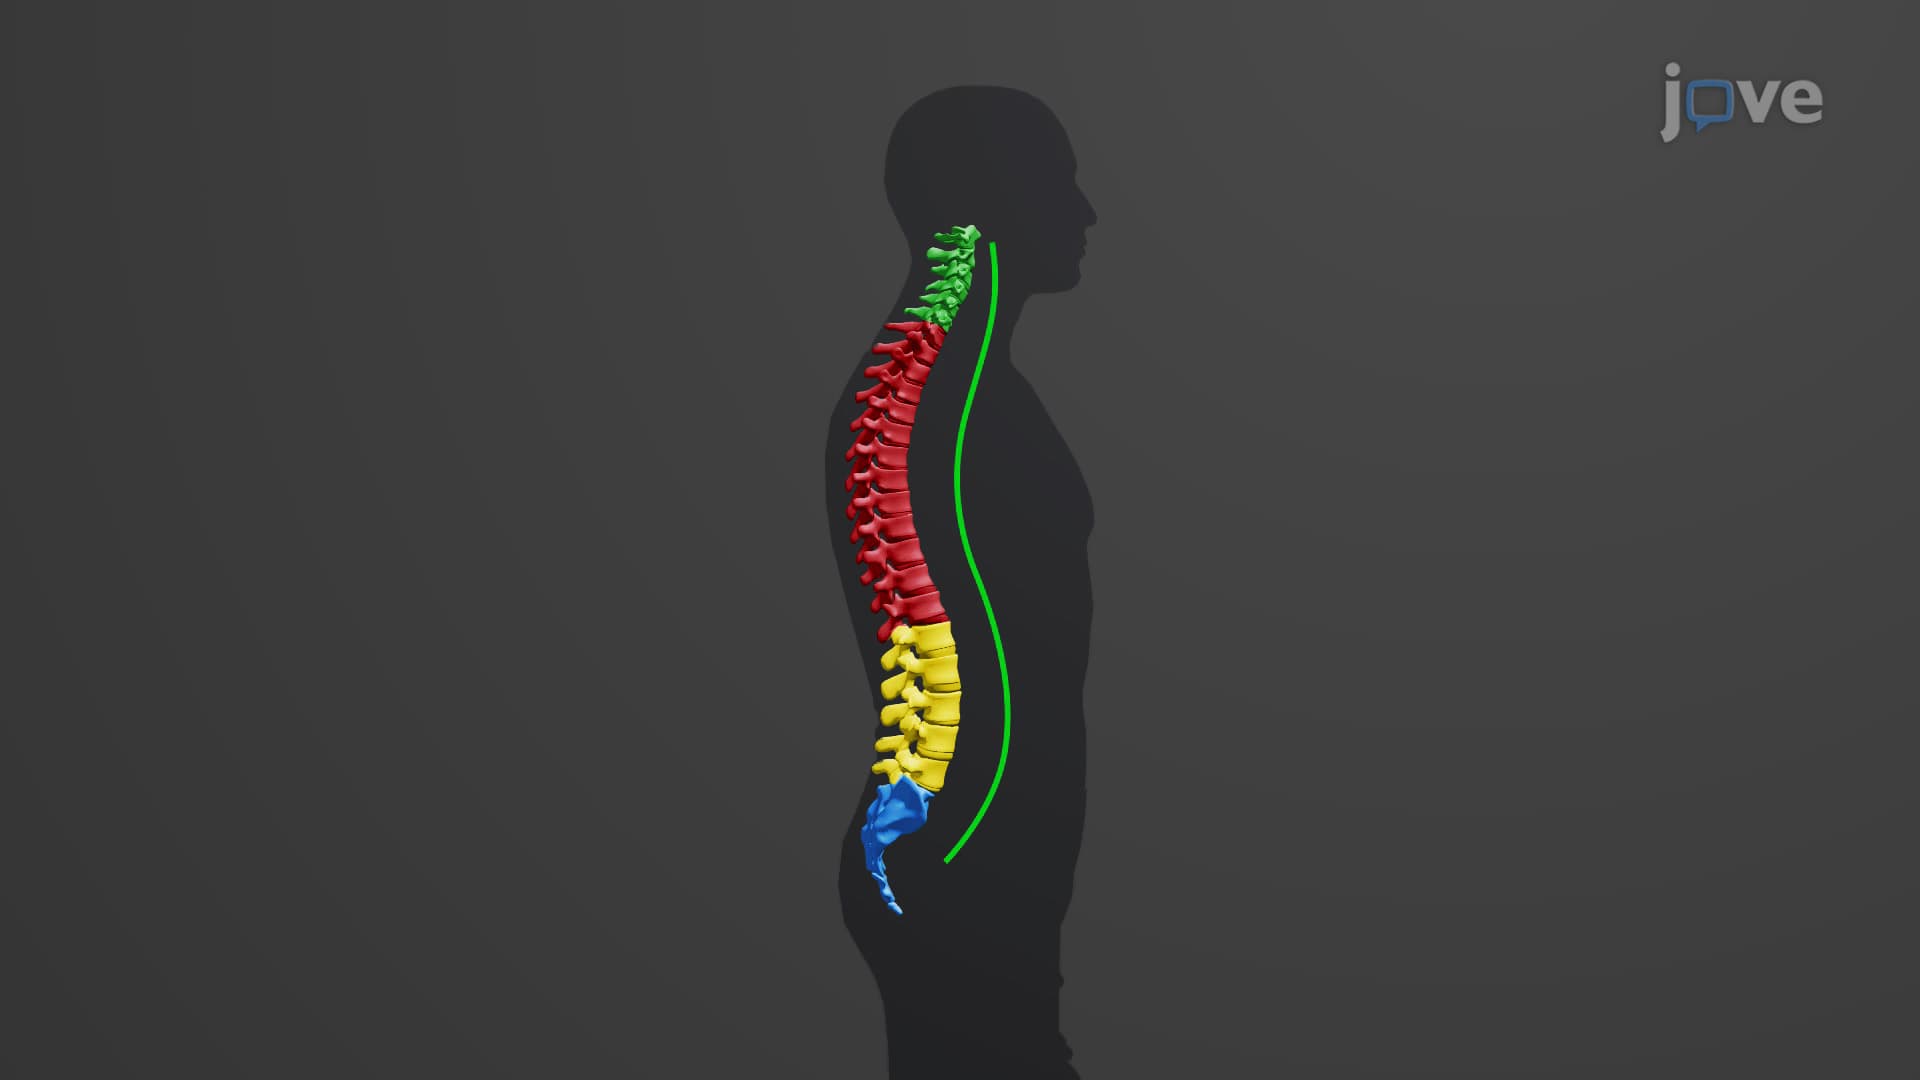
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...