Related Experiment Video
Updated: May 21, 2026
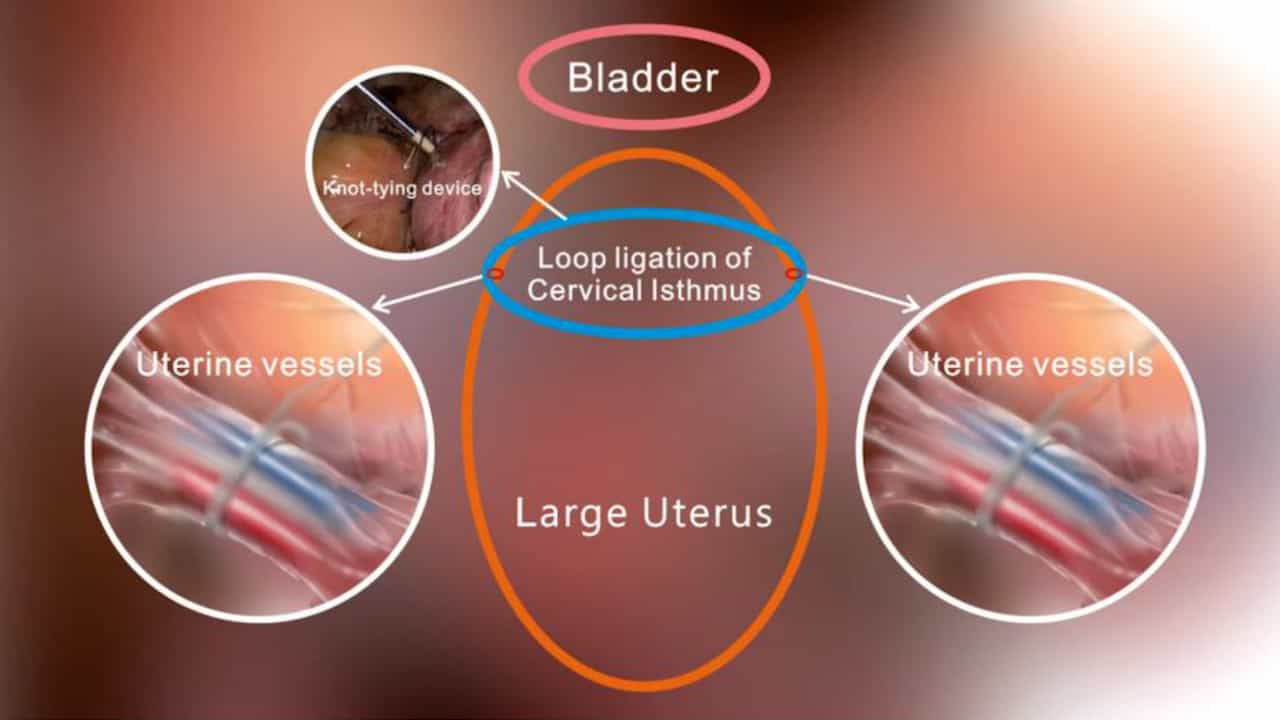
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Hysterectomy is associated with large artery stiffening in estrogen-deficient postmenopausal women
Kathleen M Gavin1, Catherine Jankowski, Wendy M Kohrt
1Division of Geriatric Medicine, Department of Medicine, University of Colorado Denver, Aurora, CO 80045, USA.

Insights
Hysterectomy, with or without bilateral oophorectomy (BLO), is linked to increased arterial stiffening in postmenopausal women. This arterial stiffening, a marker of vascular aging, occurs independently of traditional cardiovascular disease risk factors.
Area of Science:
- Cardiovascular Science
- Reproductive Health
- Vascular Aging
Background:
- Hysterectomy, with or without bilateral oophorectomy (BLO), is associated with increased cardiovascular disease (CVD) risk.
- Large artery stiffening, a biomarker of vascular aging, contributes to CVD risk.
- The impact of hysterectomy on arterial stiffening in postmenopausal women requires further investigation.
Purpose of the Study:
- To determine if hysterectomy, with or without BLO, is associated with arterial stiffening in estrogen-deficient postmenopausal women.
- To investigate the relationship between hysterectomy status and arterial stiffness markers.
- To explore potential mechanisms linking hysterectomy to increased CVD risk.
Main Methods:
- Cross-sectional study of estrogen-deficient postmenopausal women.
- Comparison of three groups: hysterectomy with ovarian preservation, hysterectomy with BLO, and no hysterectomy/no BLO.
- Measurement of arterial stiffness using carotid artery ultrasonography, assessing arterial compliance and β stiffness index.
Main Results:
- Women who underwent hysterectomy (alone or with BLO) exhibited lower carotid artery compliance compared to women without hysterectomy (P < 0.05).
- No significant differences in traditional CVD risk factors (e.g., adiposity, blood pressure, lipids, glucose) were observed between the groups.
- Hysterectomy status remained a significant predictor of arterial compliance after adjusting for multiple covariates.
Conclusions:
- Hysterectomy status (with or without BLO) is associated with increased arterial stiffening in estrogen-deficient postmenopausal women.
- The observed arterial stiffening is not attributable to an adverse CVD risk factor profile.
- Large artery stiffening may represent a key mechanism underlying the elevated CVD risk associated with hysterectomy in postmenopausal women.
Objective:
Hysterectomy, with or without oophorectomy, is associated with increased cardiovascular disease (CVD) risk due, in part, to an adverse CVD risk factor profile. Large artery stiffening, a biomarker of vascular aging, increases the risk for CVD. We determined whether hysterectomy with or without bilateral oophorectomy (BLO) is associated with arterial stiffening in healthy postmenopausal women.
Methods:
We conducted a cross-sectional study including estrogen-deficient postmenopausal women who had a hysterectomy with ovarian preservation (n = 24; mean ± SE age, 59 ± 1 y) or with BLO (n = 21; 58 ± 2 y) and had no hysterectomy/no BLO (n = 58; 58 ± 1 y). Arterial stiffness (arterial compliance and β stiffness index) was measured by ultrasonography of the carotid artery.
Results:
Carotid artery compliance was lower in women with hysterectomy alone and in women with hysterectomy with BLO compared with women with no hysterectomy (0.66 ± 0.03 and 0.71 ± 0.06 vs 0.89 ± 0.03 mm/mm Hg × 10, respectively, both P < 0.05). There were no differences in traditional CVD risk factors (ie, adiposity, blood pressure and fasted lipids and lipoproteins, glucose, and insulin) between the groups. After adjustment for age, menopause duration, previous menopausal hormone therapy duration, parity, waist-to-hip ratio, systolic blood pressure, and sex hormone-binding globulin, hysterectomy status remained a significant predictor of arterial compliance.
Conclusions:
These results indicate that hysterectomy status (with or without BLO) is associated with greater arterial stiffening in estrogen-deficient postmenopausal women. The greater arterial stiffening with hysterectomy was not related to an adverse CVD risk profile. Large artery stiffening may be an important mechanism by which hysterectomy increases the risk of CVD in postmenopausal women.

Related Concept Videos
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:28
Menopause
 01:24
Disorders of the Female Reproductive System
 01:30
Atherosclerosis I: Introduction
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 02:07
Oogenesis