Related Experiment Video
Updated: May 21, 2026


Modeling Ascending Vaginal Infection, Preterm Birth, and Neonatal Morbidity in Mice
Published on: October 10, 2025
Pyomyositis after vaginal delivery
Eve Gaughan1, Maeve Eogan, Mary Holohan
1Department of Obstetrics and Gynaecology, Rotunda Hospital, Dublin, Ireland. evegaughan@yahoo.co.uk

Pyomyositis is a purulent infection of skeletal muscle that arises from haematogenous spread, usually with abscess formation. It can develop after a transient bacteraemia of any cause. This type of infection has never been reported before in the literature after vaginal delivery. A 34-year-old woman had progressive severe pain in the left buttock and thigh and weakness in the left lower limb day 1 post spontaneous vaginal delivery. MRI showed severe oedema of the left gluteus, iliacus, piriformis and adductor muscles of the left thigh and a small fluid collection at the left hip joint. She was diagnosed with pyomyositis. She had fever of 37.9°C immediately postpartum and her risk factors for bacteraemia were a mild IV cannula-associated cellulitis and labour itself. She required prolonged treatment with antibiotics before significant clinical improvement was noted.
Pyomyositis is a purulent infection of skeletal muscle that arises from haematogenous spread, usually with abscess formation. It can develop after a transient bacteraemia of any cause. This type of infection has never been reported before in the literature after vaginal delivery. A 34-year-old woman had progressive severe pain in the left buttock and thigh and weakness in the left lower limb day 1 post spontaneous vaginal delivery. MRI showed severe oedema of the left gluteus, iliacus, piriformis and adductor muscles of the left thigh and a small fluid collection at the left hip joint. She was diagnosed with pyomyositis. She had fever of 37.9°C immediately postpartum and her risk factors for bacteraemia were a mild IV cannula-associated cellulitis and labour itself. She required prolonged treatment with antibiotics before significant clinical improvement was noted.

Related Concept Videos
 01:27
Acute Pyelonephritis I: Introduction
 01:11
Pyloric Obstruction
 01:21
Intrauterine Drug Delivery Systems
 01:26
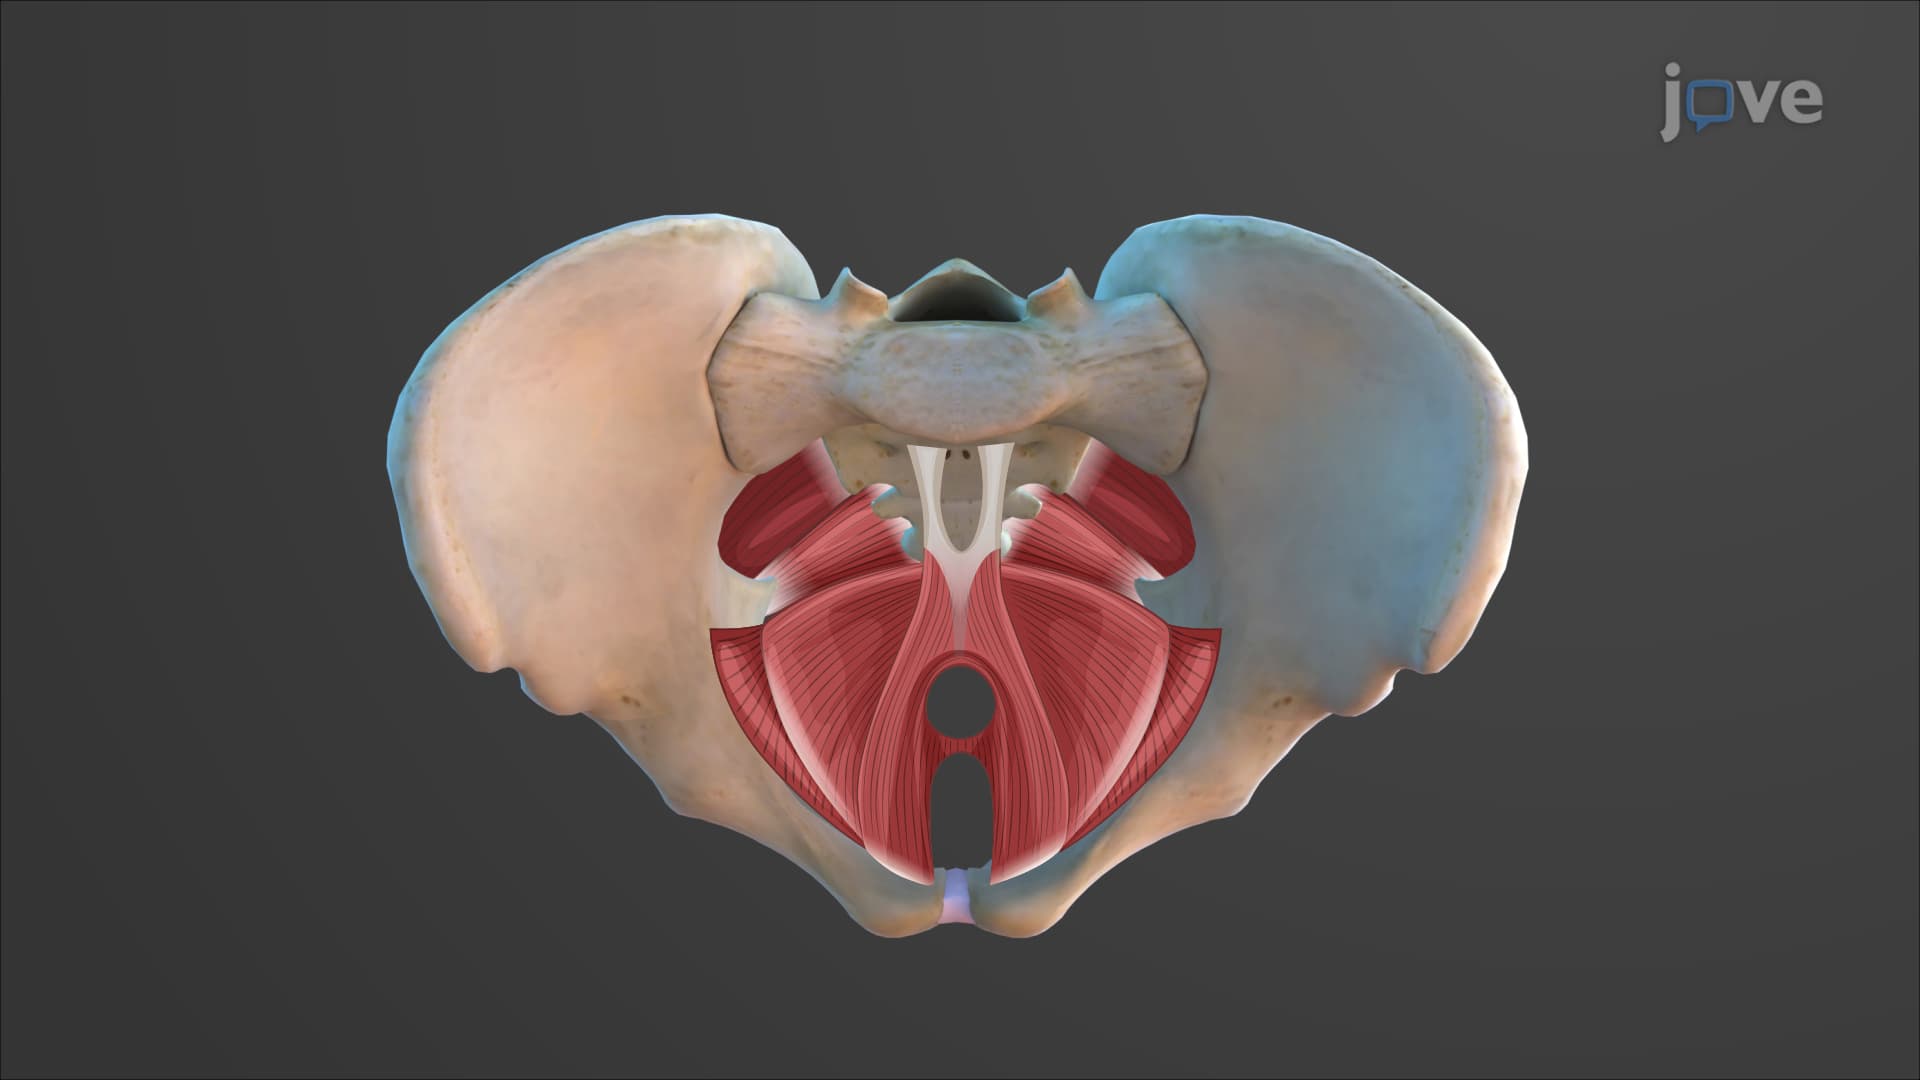
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:28
Development of the Oral Microbiota