Related Experiment Video
Updated: Jan 19, 2026
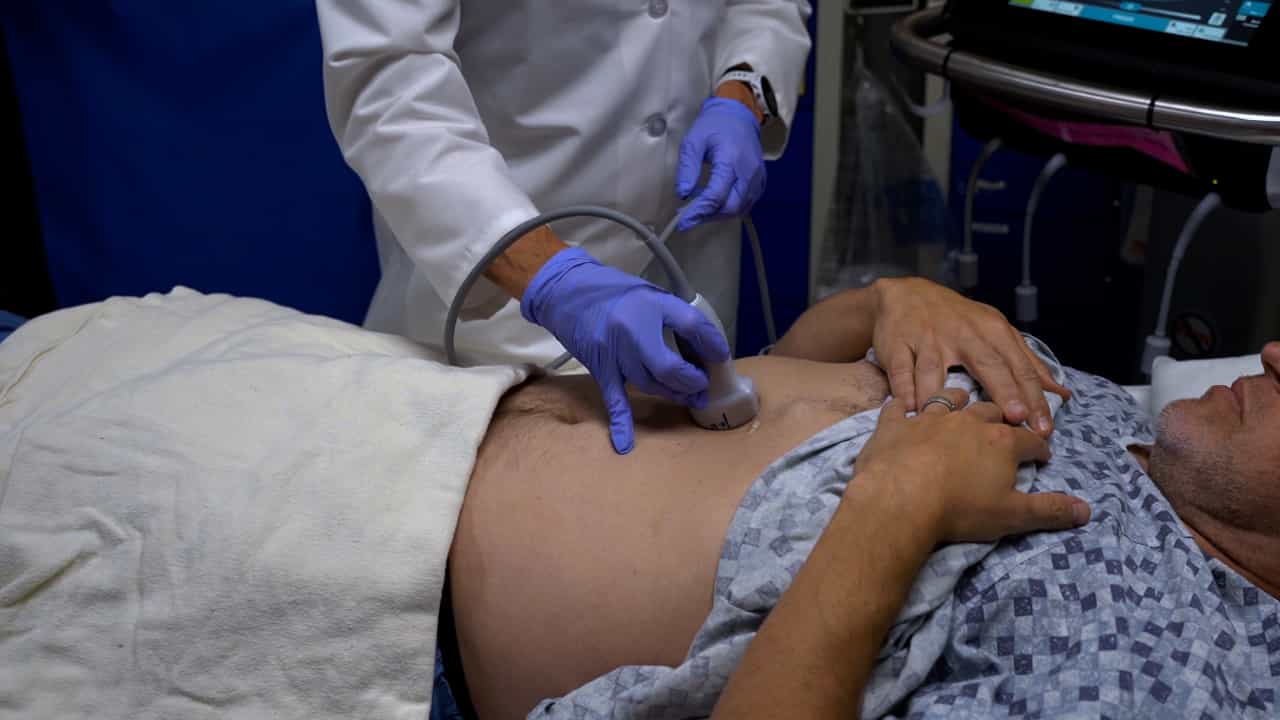

Author Spotlight: Point-of-Care Ultrasound for Gastric Content Assessment and Risk Stratification in Perioperative Care
Published on: September 22, 2023
Sitting and supine esophageal pressures in overweight and obese subjects
Robert L Owens1, Lisa M Campana, Lauren Hess
1Sleep Disorders Research Program, Division of Sleep Medicine, Brigham and Women's Hospital, Harvard Medical School, Boston, Massachusetts, USA. rowens@partners.org

Abstract:
Esophageal pressure (P(Es)) can be used to approximate pleural pressure (P(pl)) and might be clinically useful, particularly in the obese e.g., to guide mechanical ventilator settings in critical illness. However, mediastinal artifact (the difference between true P(pl) and P(Es)) may limit acceptance of the measurement, and reproducibility of P(Es) measurements remains unknown. Therefore, we aimed to assess the effect of body posture on P(Es) in a cohort of obese, but healthy subjects, some of whom had multiple measurements, to address the clinical robustness of esophageal manometry. Twenty-five overweight and obese subjects (BMI > 25 kg/m(2)) and 11 control lean subjects (BMI < 25 kg/m(2)) underwent esophageal manometry with pressures measured seated and supine. Twenty overweight and obese subjects had measurements repeated after ~1 to 2 weeks. Anthropometric data and sitting and supine spirometry were recorded. The average end-expiratory P(Es) sitting and supine were greater in the overweight and obese group than the lean group (sitting -0.1 ± 2.1 vs. -3.3 ± 1.2 cm H(2)O, supine 9.3 ± 3.3 vs. 6.9 ± 2.8 cm H(2)O, respectively). The mean differences between repeated measurements were small (-0.3 ± 1.7 cm H(2)O sitting and -0.1 ± 1.5 cm H(2)O supine). P(Es) correlated with a number of anthropometric and spirometric variables. In conclusion, P(Es) are slightly greater in overweight and obese subjects than lean subjects; but changes with position are similar in both groups. These data indicate that mediastinal weight and postural effects on P(Es) are within a clinically acceptable range, and suggest that esophageal manometry can be used to inform clinical decision making across wide range of body types.


Related Concept Videos
 01:21
Drug Dosing: Obese Patients
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:24
Upper GI Series: Barium Swallow
Purpose and Procedure
Patients undergoing this procedure ingest a liquid containing barium sulfate with a chalky...