Related Experiment Video
Updated: May 21, 2026
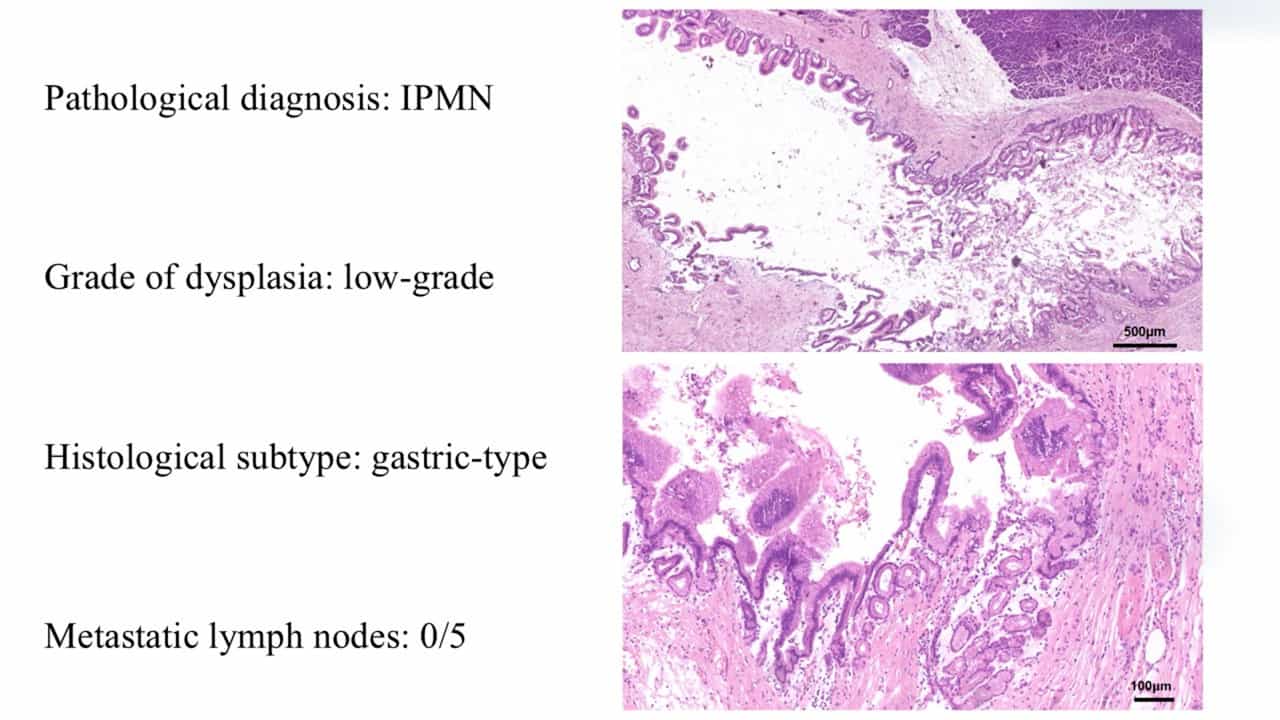

Robotic Duodenum-preserving Total Pancreatic Head Resection for Intraductal Papillary Mucinous Neoplasms
Published on: April 17, 2026
Familial adenomatous polyposis-related desmoids presenting with air-fluid level: a clinical review and management
Santosh Bhandari1, Pravin Ranchod, Ashish Sinha
11The Polyposis Registry, St Mark's Hospital, Harrow, United Kingdom.

Background:
Familial adenomatous polyposis-related desmoid tumors can present with a liquefied center containing gas, accompanied by abdominal pain and sepsis. To date the optimal management of such patients has not been documented.
Objective:
The aim of this study was to review our experience of managing these desmoids grouped together as "intra-abdominal desmoids with air-fluid level" and present a management algorithm.
Design:
This is a retrospective study of prospectively maintained polyposis registry database.
Setting:
This study was conducted at a tertiary referral center specializing in familial adenomatous polyposis and desmoid disease.
Patients:
Nine patients with intra-abdominal desmoid and air-fluid level were analyzed for the purpose of this study.
Results:
Two hundred and forty-six patients were identified with desmoid tumor. Of these, a total of 9 patients had an intra-abdominal desmoid with air-fluid level; 7 were women. Age range at diagnosis was 20 to 41 years. The median time from primary surgery to desmoid tumor development was 24 months (range, 0-48 months), and the median time for further progression to air-fluid level was 24 months (range, 0-226 months). Desmoid tumor size ranged from 10 cm to greater than 20 cm in diameter. Two patients were successfully managed with antibiotics alone, and 2 patients were managed with percutaneous drainage and antibiotics. The other 5 patients required surgical intervention involving either excision or drainage with or without proximal defunctioning/exclusion. There was a single 30-day mortality.
Limitation:
This study was limited by the small number of patients.
Conclusions:
The majority of intra-abdominal desmoids with an air-fluid level require surgical intervention. Antibiotics and percutaneous drainage are only successful in a limited number of patients. We present our current treatment algorithm based on this experience.

Related Concept Videos
 01:24
Cystic Fibrosis: Management
Sinus disease and chronic sinusitis...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: