Related Experiment Video
Updated: May 21, 2026
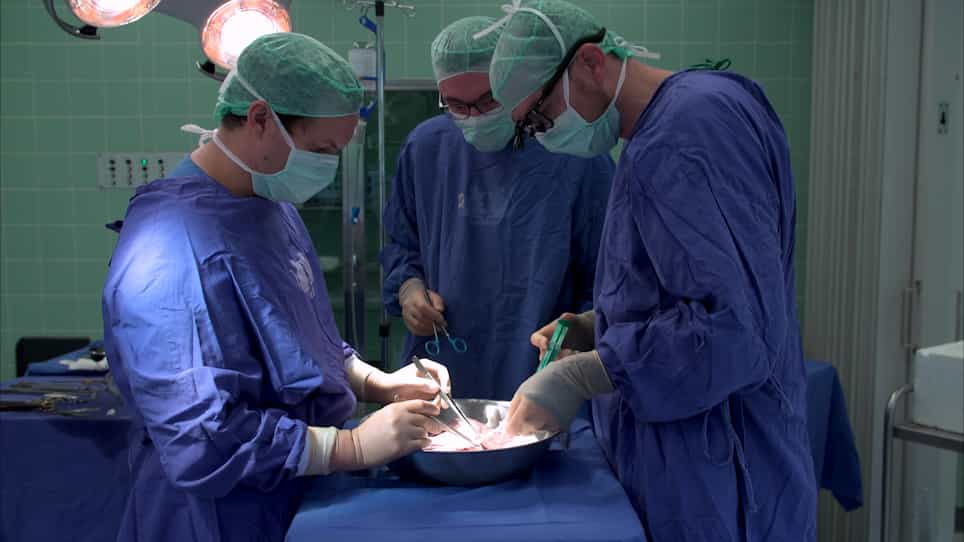

Porcine Liver Transplantation Without Veno-Venous Bypass As an Extended Criteria Donor Model
Published on: August 17, 2022
Use of higher thromboelastogram transfusion values is not associated with greater blood loss in liver transplant
Shen-Chih Wang1, Ho-Tien Lin, Kuang-Yi Chang
1Department of Anesthesiology, Taipei Veterans General Hospital, Taipei, Taiwan.

Plasma-containing products are given during the pre-anhepatic stage of liver transplant surgery to correct abnormal thromboelastogram (TEG) values and prevent blood loss due to coagulation defects. However, evidence suggests that abnormal TEG results do not always predict bleeding. We questioned what effect using higher TEG values to initiate treatment would have on blood loss. A single transfusion protocol was used for all patients who underwent liver transplantation between 2007 and 2010. Thirty-eight patients received coagulation products when standard TEG cutoff values were exceeded, whereas another 39 patients received coagulation products when the TEG values were 35% greater than normal. The results of postoperative coagulation tests for total blood loss and the use of blood products were compared for the 2 groups. When the critical TEG values for transfusion were higher, significantly fewer units of fresh frozen plasma (5.58 ± 6.49 versus 11.53 ± 6.66 U) and pheresis platelets (1.84 ± 1.33 versus 3.55 ± 1.43 U) were used. There were no differences in blood loss or postoperative blood product use. In conclusion, the use of higher critical TEG values to initiate the transfusion of plasma-containing products is not associated with increased blood loss. Further testing is necessary to identify what TEG value predicts bleeding due to a deficit in coagulation factors.
Plasma-containing products are given during the pre-anhepatic stage of liver transplant surgery to correct abnormal thromboelastogram (TEG) values and prevent blood loss due to coagulation defects. However, evidence suggests that abnormal TEG results do not always predict bleeding. We questioned what effect using higher TEG values to initiate treatment would have on blood loss. A single transfusion protocol was used for all patients who underwent liver transplantation between 2007 and 2010. Thirty-eight patients received coagulation products when standard TEG cutoff values were exceeded, whereas another 39 patients received coagulation products when the TEG values were 35% greater than normal. The results of postoperative coagulation tests for total blood loss and the use of blood products were compared for the 2 groups. When the critical TEG values for transfusion were higher, significantly fewer units of fresh frozen plasma (5.58 ± 6.49 versus 11.53 ± 6.66 U) and pheresis platelets (1.84 ± 1.33 versus 3.55 ± 1.43 U) were used. There were no differences in blood loss or postoperative blood product use. In conclusion, the use of higher critical TEG values to initiate the transfusion of plasma-containing products is not associated with increased blood loss. Further testing is necessary to identify what TEG value predicts bleeding due to a deficit in coagulation factors.

Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:28
Kidney Transplant I: Introduction
 01:15
Blood Transfusion
Blood Transfusion Overview
A blood transfusion is a medical procedure used to replace blood lost due to injury, surgery, or to treat conditions such as anemia or cancer. During a transfusion, donor blood is...