Acute water intoxication after intranasal desmopressin in a patient with primary polydispsia

J Ferrer1, I Halperin, J I Conget

  • 1Endocrinology and Nutrition Service, Hospital Clinic i Provincial, University of Barcelona, Spain.

Related Concept Videos

Prevention of Further Absorption of Poison01:14

Prevention of Further Absorption of Poison

In cases of acute poisoning, the primary objective is to prevent further absorption of the toxic substance into the body. Immediate interventions using various decontamination techniques targeting the gastrointestinal (GI) tract can achieve this. Decontamination is crucial to prevent poison from entering the systemic circulation, which involves washing affected areas with water and mild soap and removing contaminated clothing. Once external decontamination is done, attention must be turned to...
Antihypertensive Drugs: Action of Diuretics01:16

Antihypertensive Drugs: Action of Diuretics
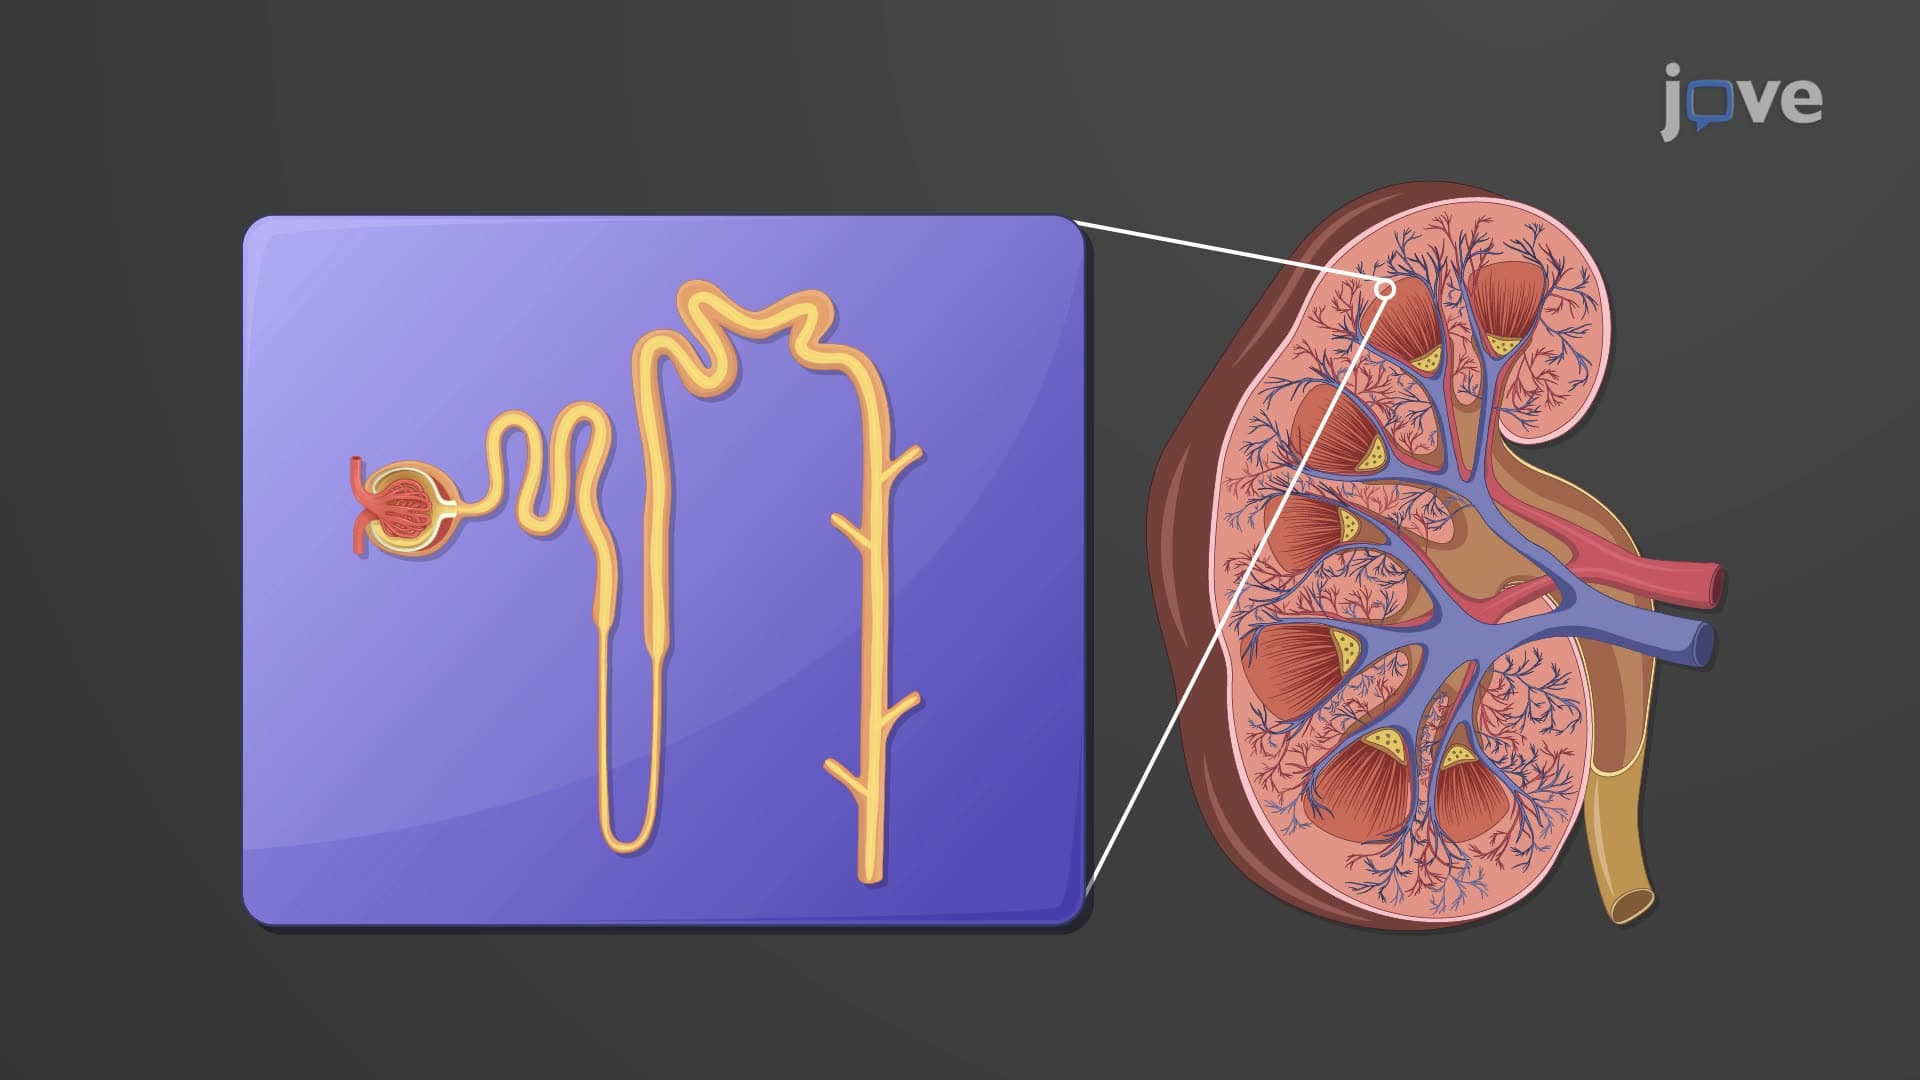
Diuretics are antihypertensive drugs used to treat hypertension resulting from sodium and water retention. Sodium, vital for fluid balance and nerve or muscle function, is regulated by the kidneys through millions of nephrons. Blood enters nephrons via afferent arterioles, which branch into capillaries called glomeruli. These filter blood plasma, allowing water and solutes, like sodium ions, to pass through capillary walls into Bowman's capsule. The filtrate then flows through various tubules...
Formation of Dilute Urine01:20

Formation of Dilute Urine

The formation of dilute urine is a critical renal adaptation that maintains fluid balance, particularly during periods of high fluid intake. This process primarily involves the juxtamedullary nephrons. By adjusting the permeability of water and ions in response to physiological conditions, the kidneys can either conserve or excrete water, resulting in concentrated or dilute urine.
Filtrate Osmolarity in the PCT
Initially, as the filtrate passes through the proximal convoluted tubule (PCT), its...

Type I Diabetes III: Clinical Manifestations01:19

Type I Diabetes III: Clinical Manifestations

Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the kidneys...
Hyperglycemia01:29

Hyperglycemia

Hyperglycemia is an abnormally high blood glucose level. It is diagnosed by fasting glucose ≥126 mg/dL, 2-hour oral glucose tolerance test (or OGTT) ≥200 mg/dL, random glucose ≥200 mg/dL with symptoms, or HbA1c ≥6.5%. However, HbA1c results may be unreliable in certain conditions, such as anemia or hemoglobinopathies, and the diagnosis should be confirmed unless classic symptoms are present. Postprandial hyperglycemia is typically considered significant when glucose levels exceed 180 mg/dL two...
Hyperosmolar Hyperglycemic State01:21

Hyperosmolar Hyperglycemic State

Hyperosmolar Hyperglycemic State, or HHS, is a serious and life-threatening complication of type 2 diabetes mellitus. It is characterized by three main features: severe hyperglycemia, profound dehydration, and elevated serum osmolality, all occurring without significant ketoacidosis.HHS typically develops in older adults or individuals with limited access to fluids. This may result from illness, cognitive impairment, or medications such as diuretics or corticosteroids. These factors reduce...



