Related Experiment Video
Updated: May 21, 2026


Non-Intubated Video-Assisted Thoracoscopic Surgery
Published on: May 26, 2023
Despite variation in volume, Veterans Affairs hospitals show consistent outcomes among patients with
Colin R Cooke1, Edward H Kennedy, Wyndy L Wiitala
1From the Division of Pulmonary & Critical Care Medicine, Department of Medicine, University of Michigan, Ann Arbor, MI, USA. cookecr@umich.edu

Objective:
To assess the relationship between volume of nonoperative mechanically ventilated patients receiving care in a specific Veterans Health Administration hospital and their mortality.
Design:
Retrospective cohort study.
Setting:
One-hundred nineteen Veterans Health Administration medical centers.
Patients:
We identified 5,131 hospitalizations involving mechanically ventilated patients in an intensive care unit during 2009, who did not receive surgery.
Interventions:
None.
Measurements And Main Results:
We extracted demographic and clinical data from the VA Inpatient Evaluation Center. For each hospital, we defined volume as the total number of nonsurgical admissions receiving mechanical ventilation in an intensive care unit during 2009. We examined the hospital contribution to 30-day mortality using multilevel logistic regression models with a random intercept for each hospital. We quantified the extent of interhospital variation in 30-day mortality using the intraclass correlation coefficient and median odds ratio. We used generalized estimating equations to examine the relationship between volume and 30-day mortality and risk-adjusted all models using a patient-level prognostic score derived from clinical data representing the risk of death conditional on treatment at a high-volume hospital. Mean age for the sample was 65 (SD 11) yrs, 97% were men, and 60% were white. The median VA hospital cared for 40 (interquartile range 19-62) mechanically ventilated patients in 2009. Crude 30-day mortality for these patients was 36.9%. After reliability and risk adjustment to the median patient, adjusted hospital-level mortality varied from 33.5% to 40.6%. The intraclass correlation coefficient for the hospital-level variation was 0.6% (95% confidence interval 0.1, 3.4%), with a median odds ratio of 1.15 (95% confidence interval 1.06, 1.38). The relationship between hospital volume of mechanically ventilated and 30-day mortality was not statistically significant: each 50-patient increase in volume was associated with a nonsignificant 2% decrease in the odds of death within 30 days (odds ratio 0.98, 95% confidence interval 0.87-1.10).
Conclusions:
Veterans Health Administration hospitals caring for lower volumes of mechanically ventilated patients do not have worse mortality. Mechanisms underlying this finding are unclear, but, if elucidated, may offer other integrated health systems ways to overcome the disadvantages of small-volume centers in achieving good outcomes.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:15
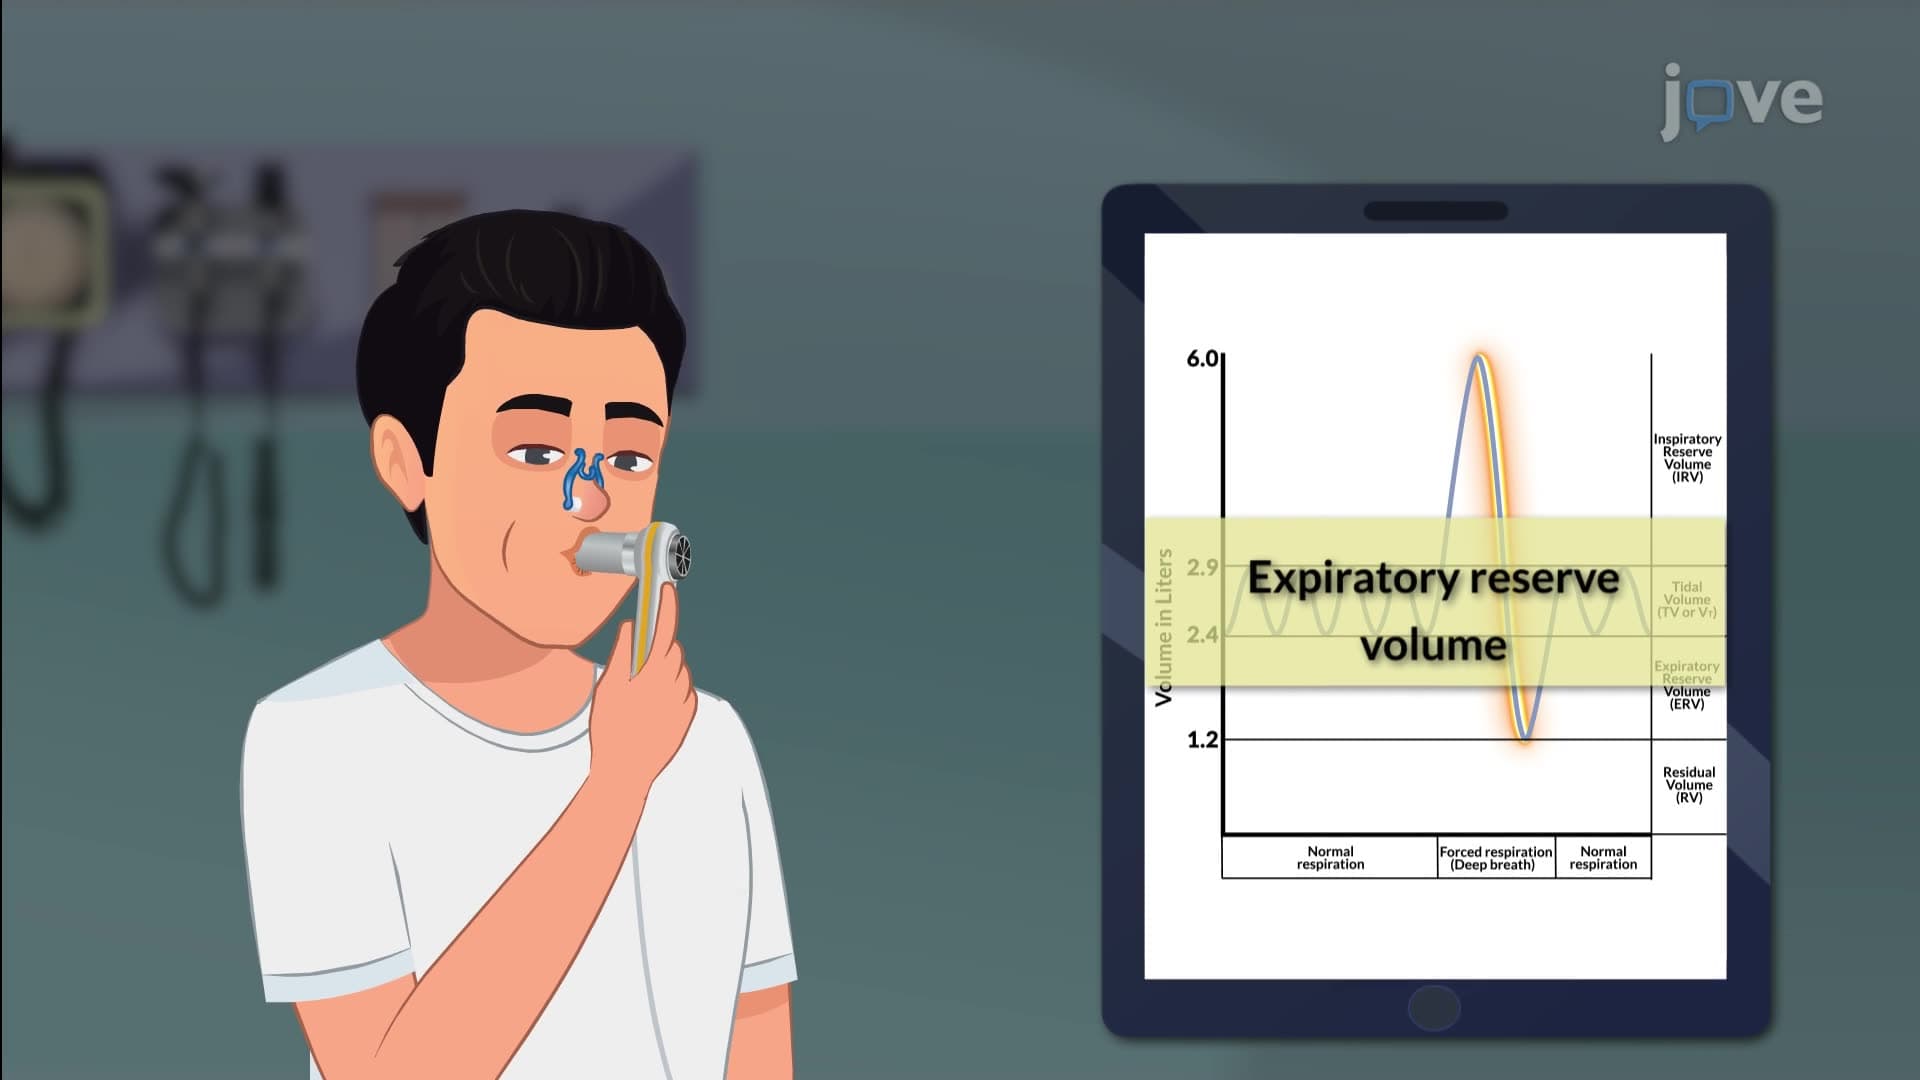
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: